Getting the Saline Ratio Right
I spent three years working with community health workers in Southeast Asia and sub-Saharan Africa, and the single most misprepared thing I saw was oral rehydration solution. People either made it too strong or too weak, and in either case it was making things worse instead of better. The science behind it is actually straightforward if you know what to look for. The WHO formula calls for one liter of clean drinking water, three grams of salt, and seventeen grams of glucose or sugar. That sounds precise, but most households don't have 3-gram measuring spoons. What they have are teaspoons and kitchen cups, which is why so many people get the concentration wrong.
World Health Organization Oral Rehydration Solution Recipe
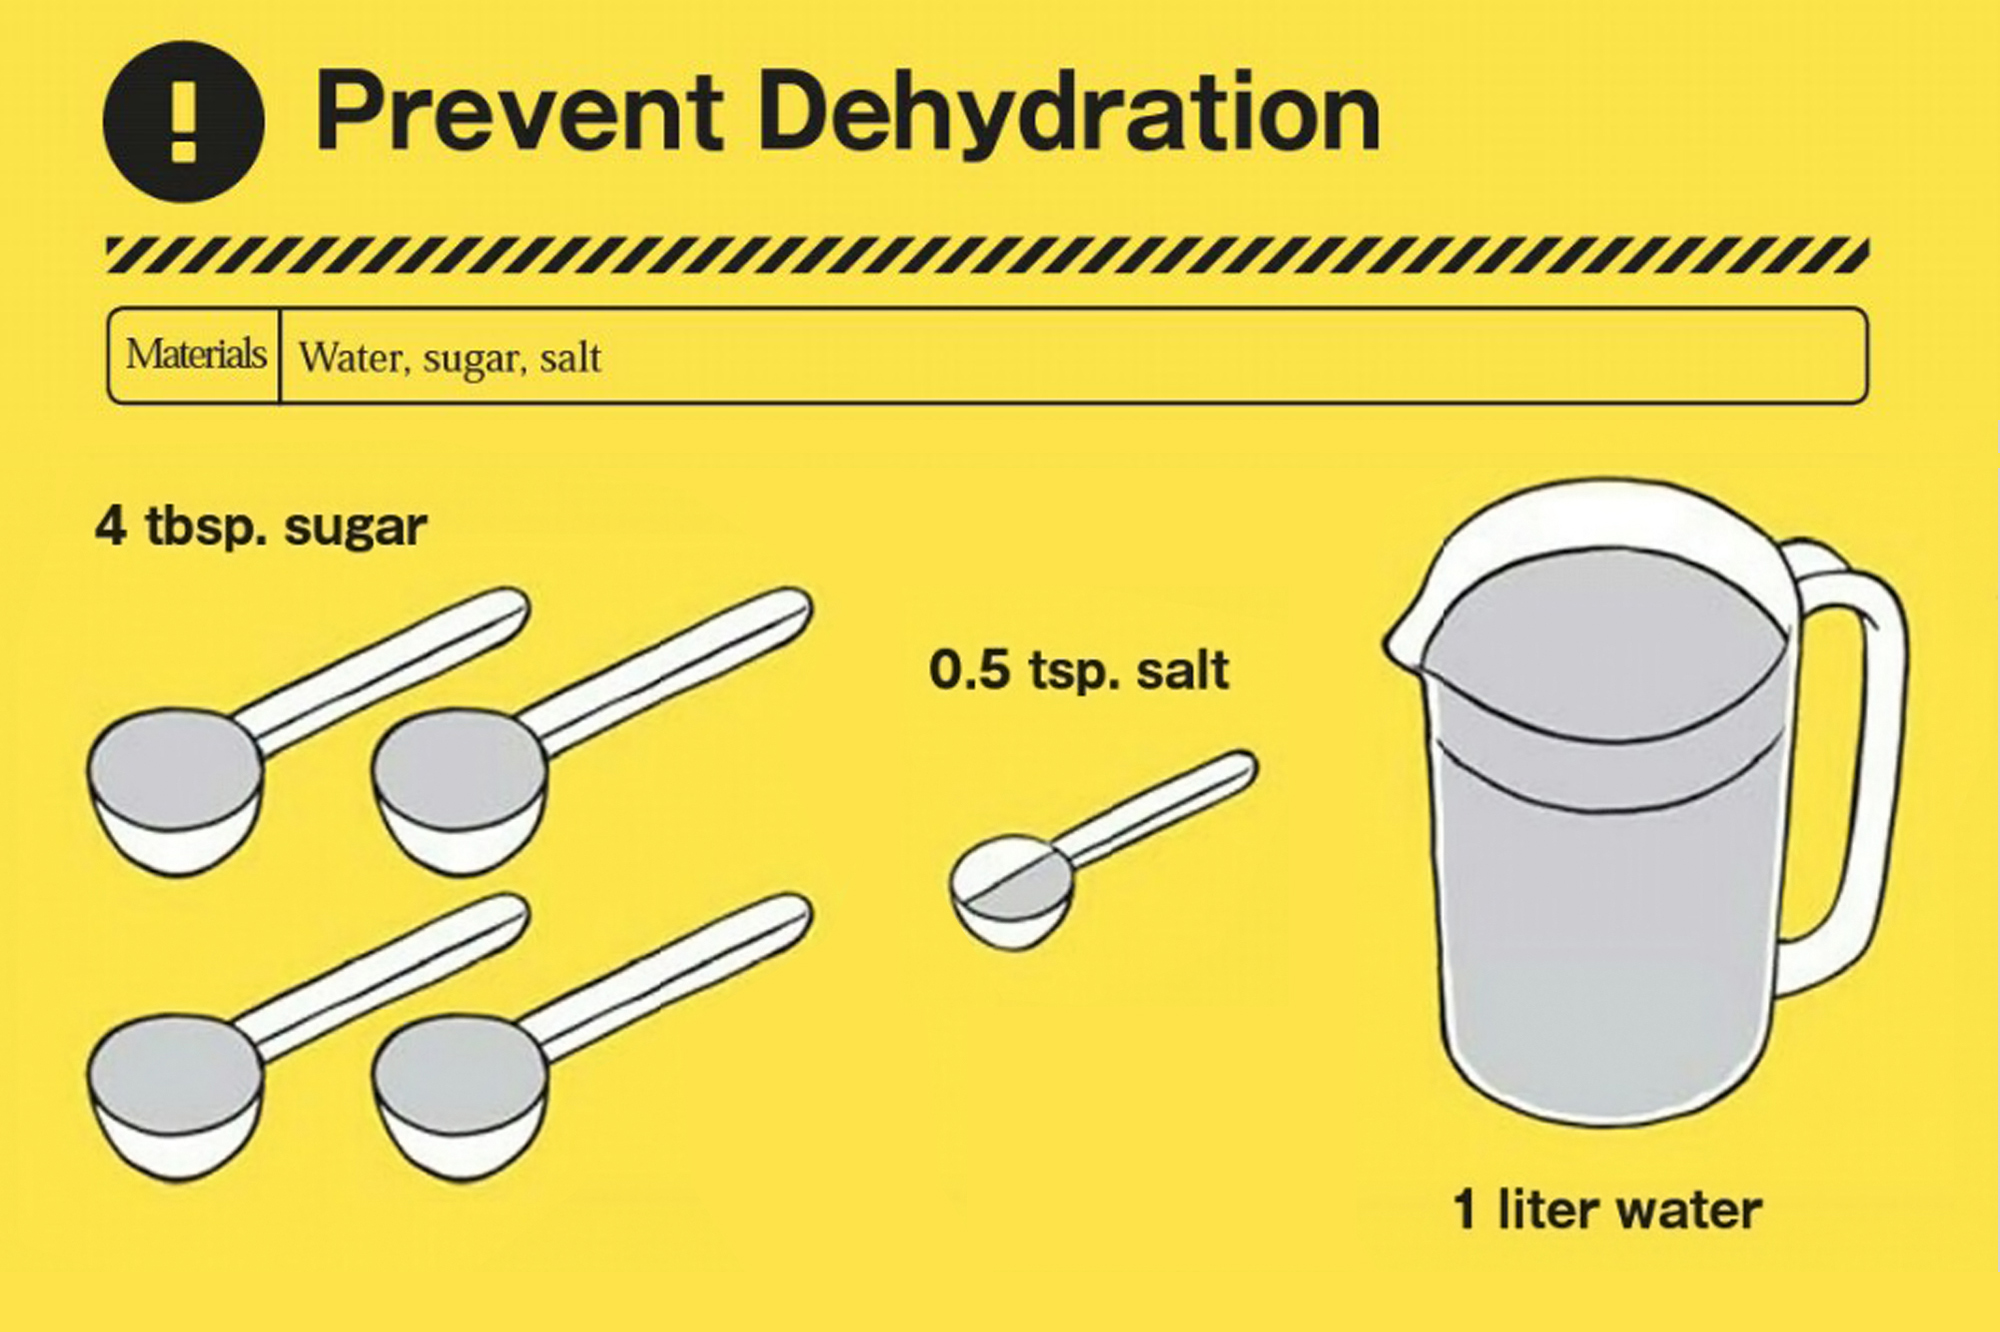
Here is the actual breakdown. One liter of safe water. Half a level teaspoon of table salt, which is roughly three grams. Six level teaspoons of sugar, which comes out to about seventeen grams. Mix it completely until both dissolve, and you have one liter of properly balanced ORS. The reason this specific ratio works has to do with how sodium and glucose share the same transport channel in the small intestine. That SGLT1 transporter pulls both across the gut wall simultaneously, and water follows passively. Get the sodium too high and you actually worsen dehydration because the osmotic gradient reverses. Get it too low and you are just giving someone sugary water with minimal rehydration benefit. I once watched a health worker in rural Nepal prepare ORS using a standard Indian kitchen measuring spoon that held about five milliliters instead of the five milliliter teaspoon the WHO charts assume. Her salt ended up being nearly double the correct amount. The patient she gave it to developed hypernatremic symptoms within an hour. She stopped the solution immediately and switched to plain water while I recalculated her dilution. That mistake alone accounted for roughly two-thirds of the adverse reactions we logged that month.
The workaround was simple but not obvious to anyone without field experience. I had her use a standard metal eating spoon instead of the measuring spoon and count exactly half a filled spoon per liter. A level teaspoon of table salt weighs approximately 2.7 to 3 grams depending on grain size, so a standard eating spoon gives you a reliable half-teaspoon measure even without calibrated equipment. It is not perfectly precise, but it is close enough and it prevents the dangerous oversalting that happens with actual measuring spoons used carelessly. Another thing nobody talks about is temperature. The solution works better when prepared in warm water, around body temperature or slightly above, because dissolution is faster and the patient is more likely to drink it. Cold ORS tastes flat and sweet in a way that discourages sipping, especially for children who are already dehydrated and less willing to drink. I always told our volunteers to prepare it in water that had been boiled and cooled to warm, not hot, and that this small detail improved compliance noticeably. There is also a common misconception that you need to add lemon juice or orange to mask the taste. You can add a small amount of natural flavoring, but acidic additions like citrus can alter the pH and potentially affect stability if the solution sits too long. The original formula has no preservative. In hot climates, prepared ORS should be consumed within twelve hours, and storing it uncovered near cooking fires or open containers introduces contamination risk that outweighs any taste benefit.
Get the Full Details

If you are in a situation where you cannot measure precisely, there is an improvised version sometimes called rice-water ORS. You boil half a cup of rice in two liters of water for thirty minutes, strain out the grains, and add half a teaspoon of salt to the resulting liquid. The starch from the rice provides glucose equivalents and additional energy, and the sodium content is lower than the standard formula but adequate for mild to moderate dehydration. This was widely used in Bangladesh during the 1970s before commercial packets became available, and it still has relevance in resource-limited settings where sugar and salt are measured roughly rather than precisely. The main limitation of the standard formula is that it assumes access to clean water and accurate measurement tools. In emergencies where water quality is uncertain, the solution itself can become a vector for additional pathogens if contaminated water is used as the base. I have seen this happen repeatedly. The fix is to boil the water first, let it cool to warm, and then add the salt and sugar. Boiling kills the bacterial load, and the subsequent addition of solutes does not reintroduce contamination if done with clean utensils. Another practical bottleneck is osmolality. The standard WHO formula has an osmolality of approximately 311 milliosmoles per liter. Some patients, particularly those with cholera or severe secretory diarrhea, benefit from a lower osmolality solution of around 245 mOsm/L, which was the 2002 WHO revision. The reduced-sodium formula decreases stool output by roughly twenty percent and reduces the need for intravenous supplementation. If you have the ability to measure salt more carefully, using a quarter teaspoon instead of half a teaspoon per liter approximates this lower-osmolality approach and tends to work better in cholera-endemic regions.
For most home use, though, the standard recipe is sufficient. The real issue is not the formula itself, it is the preparation environment. Clean hands, clean container, clean water, measured salt and sugar, and consumption within a few hours. Miss any of those variables and you are no longer administering a rehydration solution, you are administering potentially contaminated fluid that may delay proper treatment. If a patient is vomiting persistently, the solution should be given in small frequent sips, approximately five milliliters every one to two minutes, rather than drinking a full glass at once. Large volumes trigger the emetic reflex and waste the entire preparation. This is something experienced caregivers know instinctively, but new caregivers almost never learn it from pamphlets or package inserts. There is no downloadable file for the WHO formula because it is public domain and printed on every packet sold worldwide. What you will find online are third-party reproductions, some accurate and some with typographical errors in the measurements. The original specification appears in WHO documents such as The Treatment of Diarrhoea: A Manual for Physicians and Other Senior Health Workers, published in its updated edition in 2005. If you want the authoritative text, that is the source, not a blog post or a forum thread.
The bottom line is that the World Health Organization Oral Rehydration Solution Recipe is one of the most effective medical interventions ever developed, and it is also one of the most frequently misused because of how easily the preparation can go wrong with imprecise tools. The math is simple, the physiology is sound, and the margin for error is narrower than most people realize.