What Wound Dressing Documentation Actually Looks Like in Practice
The chart just went sideways again. I can see it from here - another wound, another set of measurements that nobody agrees on, another dressing change where someone wrote "packed with gauze" instead of anything remotely useful for the next clinician. This happens constantly. I've been doing this long enough to recognize the pattern before it even starts. Documentation for wound care isn't a formality you push through. It's the single most important thread connecting every handoff, every insurance review, every legal defense. When you document a dressing change correctly, the person reading it thirty minutes later or thirty days later understands exactly what was done, why it was done, and what should happen next. When you get it wrong, patients get worse and clinicians get sued. I'm going to walk through a practical Wound Dressing Documentation Sample approach that actually works in a busy clinical environment, not the sanitized version you see in textbooks.
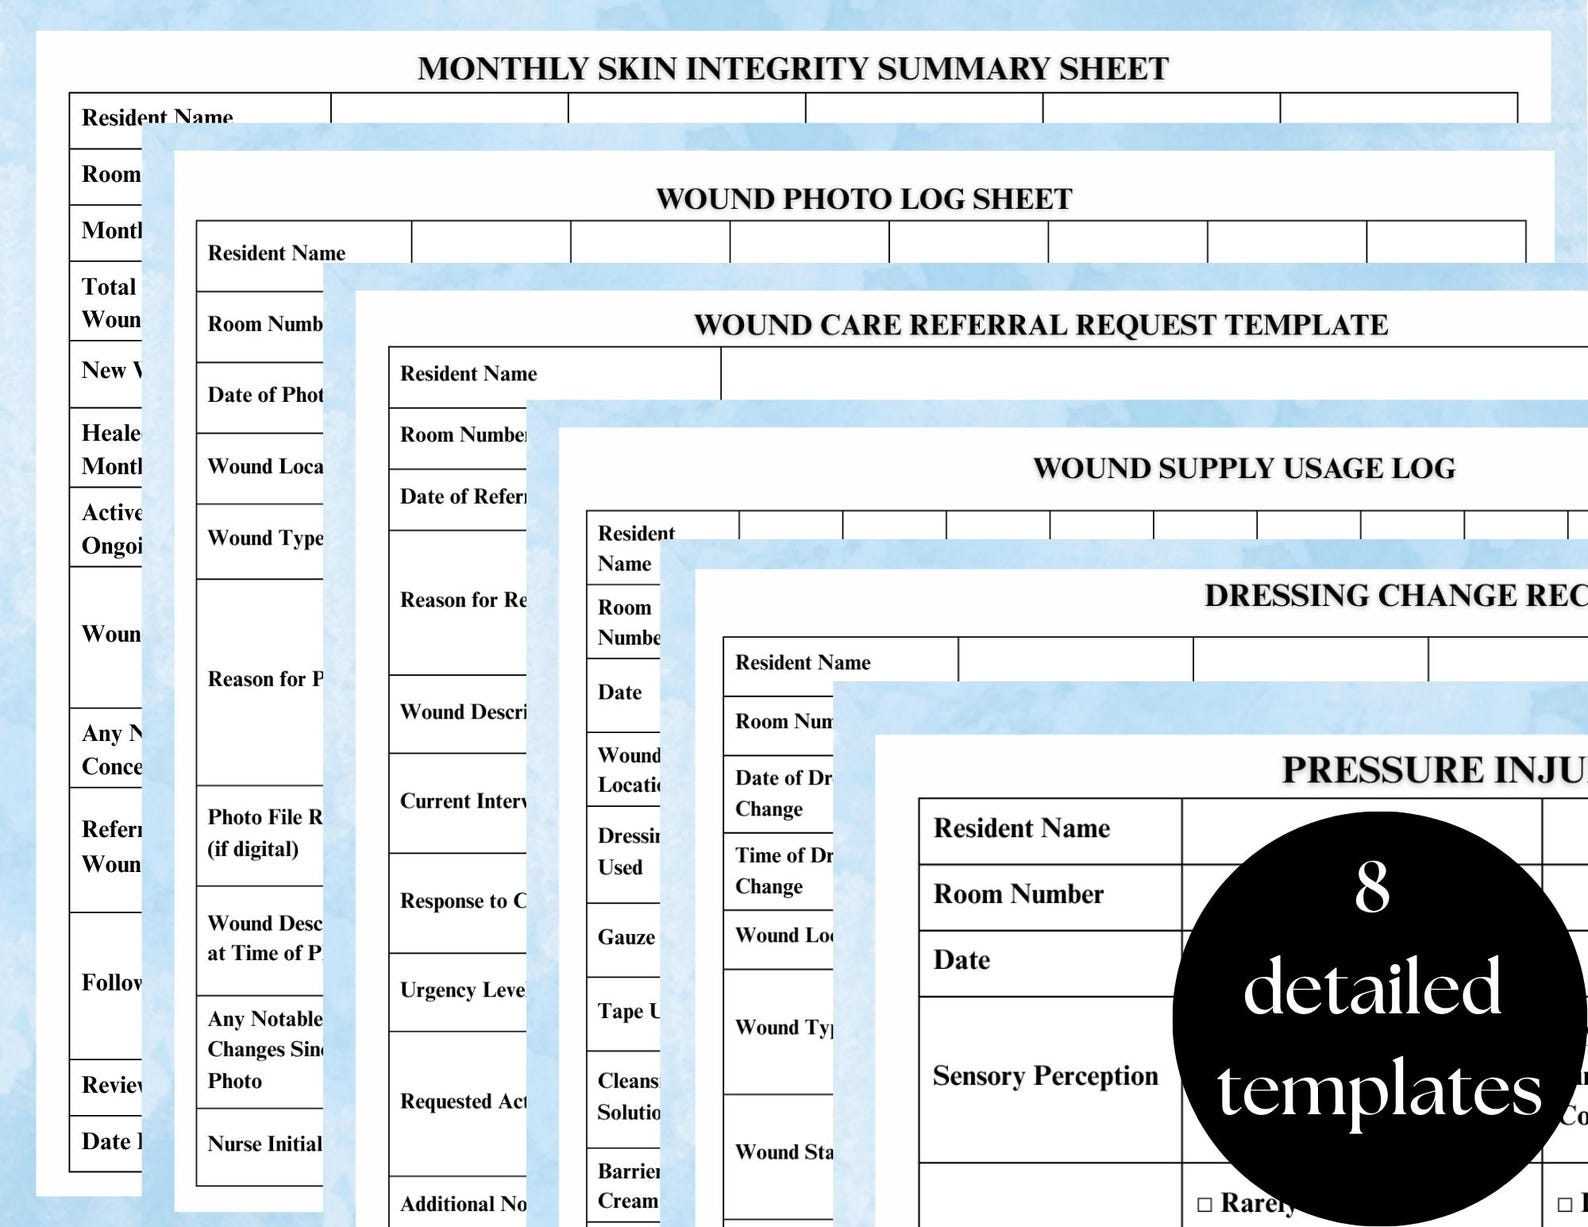
Wound Dressing Documentation Sample Template
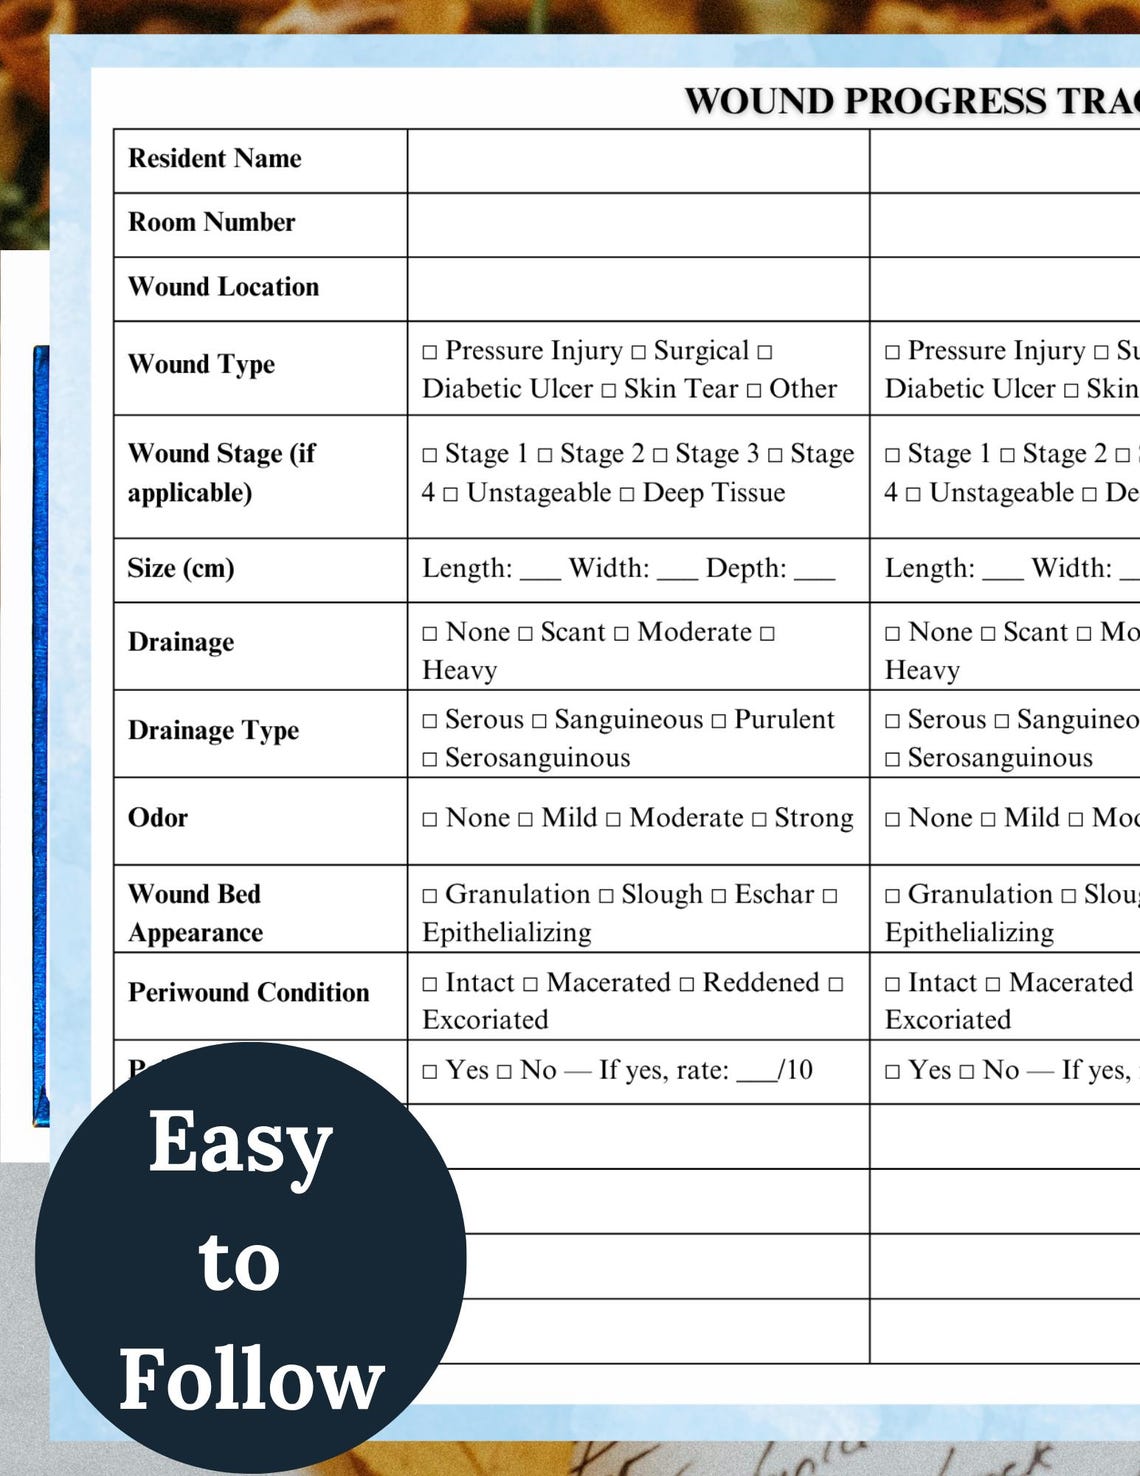
Here's what a solid wound dressing documentation entry should contain when you're doing it right: Date and time of assessment. Wound location using anatomical landmarks, not guesses. "Left medial malleolus" beats "left ankle area." Dimensions in centimeters using the head-to-toe and widest-to-widest method. Depth measured with a sterile cotton-tipped applicator, recorded in centimeters. Wound bed coverage percentages for granulation tissue, slough, and eschar as separate entries. Exudate amount and type - light, moderate, heavy, and serous, sanguinous, purulent, or serosanguinous. Odor noted if present. Periwound skin condition described specifically. Drainage amount if using a drain or collection device. Pain level before and after the procedure using the patient's own reported scale. Treatment plan for next dressing change. Photographs taken when appropriate and referenced by date. This is the standard, but standards don't account for the reality of working with a patient who can't stay still, or a wound that looks completely different than it did two hours ago, or a medical record system that forces you to use checkboxes instead of free text. I ran into exactly this problem last month documenting a Stage 3 pressure injury on a patient's sacrum. The EMR I was forced to use only had fields for "minimal," "moderate," or "heavy" exudate. The patient had moderate drainage on the dressing but minimal through the wound edges themselves. I literally spent twenty minutes filling out the required fields while the patient was sitting up eating breakfast, and by the time I was done, I'd missed documenting the periwound maceration that was clearly present. What I ended up doing was creating a quick shorthand notation in the comments section that mapped directly to the wound care protocol we'd agreed on with the physician. It wasn't ideal, but it was better than leaving the maceration undocumented because the dropdown menu couldn't capture nuance.
That shorthand approach is worth something on its own. Most wound care nurses I know develop their own consistent abbreviation system over time, and it works as long as everyone on the team knows what it means. I recommend adopting one early rather than trying to explain paragraphs of narrative every shift.
Get the Full Details
Why Most Wound Documentation Fails
The biggest issue I see repeatedly is that people document what they did rather than what they found. A dressing change without adequate assessment is just a dressing change. You might apply the right product, use the right technique, and choose the right secondary dressing, but if you didn't actually assess the wound bed accurately, you've got no baseline for progress or decline. Another common mistake involves the dressing selection rationale. Write down why you chose a specific product. Not just "hydrocolloid applied" but "hydrocolloid applied due to minimal exudate and need for autolytic debridement at wound edges." That single sentence tells the next clinician your clinical reasoning and gives them something to evaluate when they reassess. I also notice that people frequently skip documenting the wound measurement technique. Some wound care specialists still document wound dimensions using only the longest axis. This misses critical information about wound shape and growth patterns. Documenting both the longitudinal and transverse measurements, plus depth, gives you a much more complete picture. I've seen ulcers appear stable in length while actually growing deeper and wider underneath - a classic presentation of undermining that goes unnoticed without proper documentation methodology.
The timing of documentation matters too. Ideally you assess and document immediately after cleaning and debridement but before applying the final dressing. This gives you a clean view of the wound bed without blood, cleaning solutions, or old dressing material obscuring the assessment. I've had situations where I assessed a wound after dressing application and could barely see the edges through dried exudate and adhesive residue. That's not documentation, that's a guess.
Documentation Systems That Actually Work
Electronic health record systems for wound care vary enormously in quality. Some are essentially checkbox exercises that generate more work than they save. Others actually integrate wound photography, measurement tools, and automated progress tracking in ways that reduce the time you spend documenting while improving accuracy. I recommend a hybrid approach regardless of your system: use structured data wherever possible for measurable items like dimensions, depth, and exudate amount, but reserve free-text fields for clinical observations that don't fit in categories. The free-text should always reference the structured data you've already entered. This creates a trail that's both searchable and narrative-driven when someone needs the full context. Photography deserves special attention. Wound photographs are among the most powerful documentation tools available, but they're almost universally underutilized. The problem isn't usually the camera or the software - it's the protocol. Every wound photo should include a ruler in the frame, standardized lighting conditions, consistent angle and distance, and a patient identifier that matches the documentation system. Without these controls, photographs become anecdotal evidence rather than clinical data.

I had a case where a wound appeared to improve visually at first glance, but the photograph with measurement scale showed that while the surface area decreased, the depth had actually increased from three centimeters to four centimeters. The wound was progressing toward the bone rather than healing inward. This distinction would have been invisible without standardized photography, and it completely changed the treatment plan.
Pitfalls That Cost Credentials and Patients
Documentation gaps create liability. Not as a threat, but as a factual statement about how medical records function in review settings. An auditor or legal reviewer cannot infer clinical judgment from incomplete records. If you documented that you assessed a wound but didn't record the assessment findings, the record shows no assessment occurred. This applies equally to wound measurements, dressing changes, and any intervention. Another critical issue involves documentation of patient education. Many wound care protocols require documented patient or caregiver education about signs of infection, dressing change procedures, and activity modifications. This education must be dated and specific. "Education provided" is meaningless. "Patient educated on signs of infection including increased redness, warmth, swelling, and foul odor; demonstrated proper dressing removal technique with return demonstration confirmed" is defensible and useful. I should mention that some wound care documentation requirements vary by facility type, payer, and jurisdiction. Medicare has specific wound care documentation requirements for coverage. State nurse practice acts may impose additional requirements. Private insurers sometimes require specific documentation elements for authorization. The baseline documentation elements I've outlined here meet most requirements, but you need to verify what applies to your specific setting.
Finally, be honest about what you don't know. If you couldn't fully assess a wound due to pain, patient cooperation, or dressing integrity, document that limitation. This protects you clinically and legally while flagging the need for reassessment. It's better to document an incomplete assessment than to fabricate or estimate data you haven't verified.