What This Exam Actually Shows
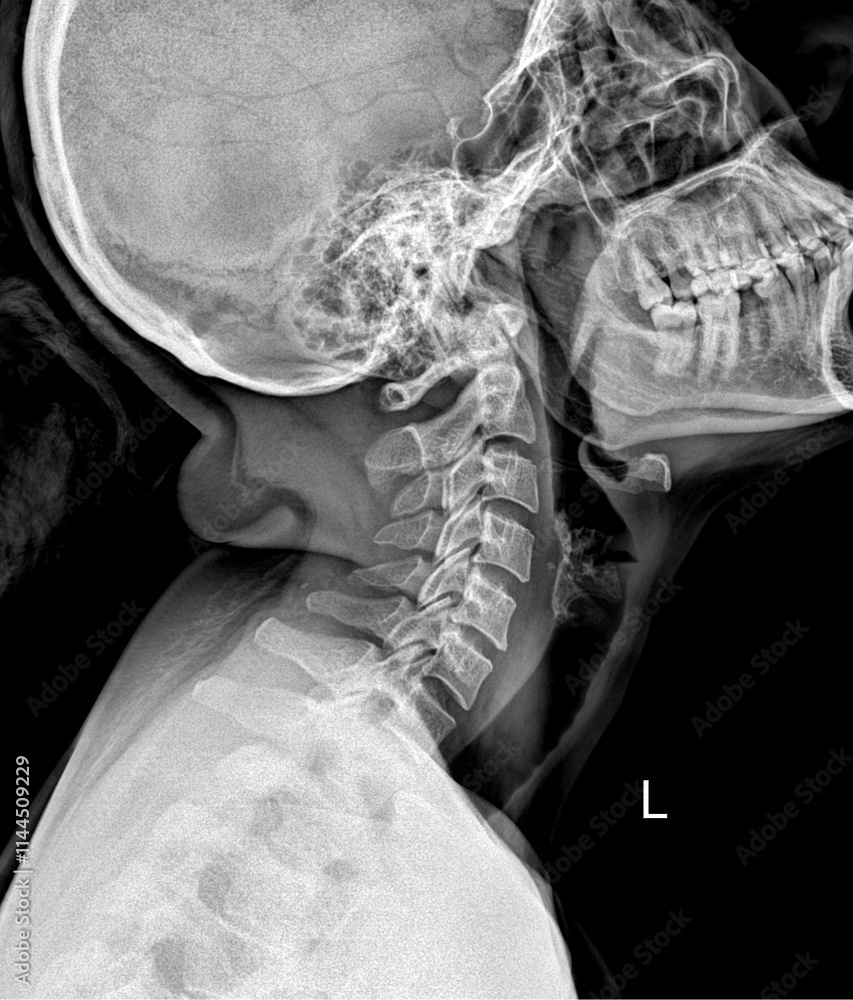
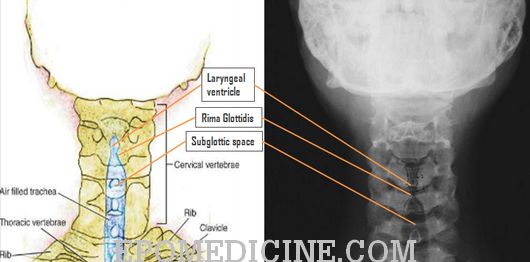
A soft tissue neck X ray is a plain radiograph of the lateral neck, usually done with the patient upright and taking a full inspiration. It is not a comprehensive study of the airway, but it still catches problems that would otherwise go unnoticed until they become emergencies. The exam visualizes the prevertebral soft tissues, the air column, and the bony structures in profile. It is fast, inexpensive, and quick to order, which is exactly why it remains useful despite the availability of CT. I have been performing and reading these studies for years, and the biggest problem I see is that people rely on it when they should be moving straight to CT, then they complain the film was unhelpful. The exam has a narrow lane of usefulness. It works well for kids who present with stridor, drooling, or neck pain after possible trauma, and it works well for adults with suspected retropharyngeal abscess or foreign body when CT is either unavailable or would require contrast that the patient cannot safely receive. Outside of those scenarios, the radiation is rarely justified because a CT will answer more questions in the same amount of time once the patient is on the table. The technical side is straightforward if you follow the same steps every time. Position the patient in a true lateral view with the side of the neck closest to the detector. Align the central ray at the level of the thyroid cartilage. Ask the patient to inhale deeply and hold their breath. If you are imaging a child and they will not cooperate, use a short exposure burst during quiet breathing, but flag the film so the reader knows the expiratory vs inspiratory phase is uncertain. Use a soft tissue technique chart with a grid only if the patient's neck diameter exceeds 15 cm, which is uncommon in the pediatric population but common in adults with obesity. An anteroposterior view is sometimes added to look for free air or displaced foreign bodies, but the lateral is the workhorse.
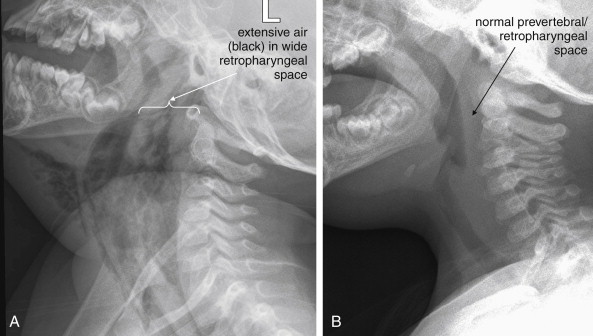
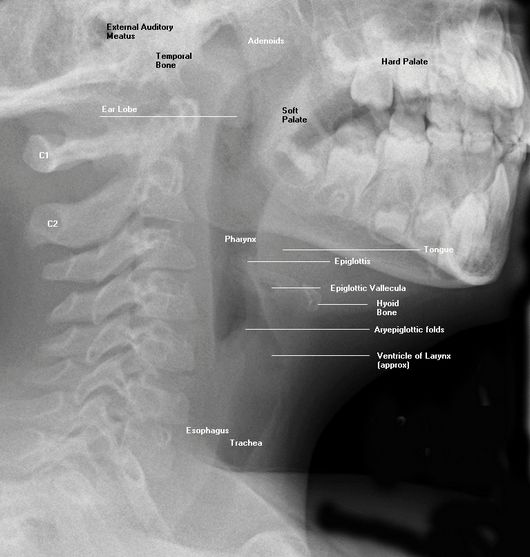
The prevertebral soft tissue measurements are where most readers make mistakes. On a properly inspired lateral film, the prevertebral soft tissue thickness at C2 should be less than 7 mm in adults and less than 22 mm at the level of the axis body in children, though pediatric values shift quickly with age. At C6, the measurement should be less than 22 mm in adults. These numbers are not hard laws. They are starting points. A swollen prevertebral space suggests pathology, but so does a poor inspiratory effort, head rotation, or an exaggerated cervical lordosis. I have seen films read as abnormal that were actually just expiratory views from a crying toddler. The workaround is simple: check the position of the clavicles and the first rib. If they are elevated and the lung apices are not fully visualized, the film is expiratory, and you should not rely on the prevertebral measurements. Reading the study requires a systematic pass through a few specific areas. Look at the air column first. Any narrowing, deviation, or irregularity here is significant. Starring is a normal finding in the vallecula and pyriform sinuses, so do not mistake it for pathology. Check the epiglottis. A swollen, rounded epiglottis that looks like a thumbprint is concerning for epiglottitis, though in practice most suspected cases move straight to direct visualization or CT because waiting for an X ray delays definitive care. Look at the prevertebral space along the entire cervical spine. A mass effect displacing the airway anteriorly is a red flag for retropharyngeal abscess, hematoma, or tumor. Examine the posterior pharyngeal wall for gas bubbles, which can indicate a perforation or gas-forming infection. Inspect the hyoid bone, thyroid cartilage, and cricoid for fractures or subluxation. Look at the cervical vertebrae for alignment and cortical breaks. Finally, scan the upper thorax for pneumomediastinum or subcutaneous emphysema. I remember a case a few years back where a patient came in after a blunt trauma to the neck with hoarseness but no obvious fracture on initial imaging. The lateral soft tissue neck film showed a subtle but clear step-off at the cricoid lamina and a small amount of prevertebral swelling that extended down into the superior mediastinum. That finding pushed me to get a CT angiogram immediately, which revealed a cartilaginous fracture with a surrounding hematoma compressing the airway. Had I skipped the plain film and gone straight to CT, I might have still seen it, but the plain film flagged the urgency and helped the team prioritize the airway before sedation. That is the kind of situation where this exam earns its keep.
There is a common misconception that a normal soft tissue neck X ray rules out a retropharyngeal abscess. It does not. Sensitivity is moderate at best, especially in adults where the prevertebral tissues are naturally thicker and harder to measure accurately. A normal film in a low-risk patient is reassuring, but a positive clinical picture with a normal film should never stop you from getting a contrast-enhanced CT. In my experience, adult retropharyngeal abscesses are frequently missed on plain films because the swelling is subtle and overlaps with normal anatomic variation. Pediatric cases are easier to spot because the prevertebral space is normally thin, so any increase stands out more clearly. Foreign bodies are another area where this exam is selectively useful. Metal objects are radiopaque and obvious. Bone fragments, fish bones, and plastic objects are often radiolucent or only faintly visible. A negative film does not mean there is no foreign body. CT is far superior for detecting radiolucent foreign bodies and determining their exact relationship to surrounding structures. I still use the lateral soft tissue neck film as a quick first look in patients presenting after swallowing a sharp object, mainly because it takes thirty seconds and sometimes provides enough information to avoid the CT entirely if the object is clearly visible and superficial. One nuance that beginners miss is the effect of positioning on the air column appearance. Slight rotation of the head can make the airway appear narrower than it actually is, particularly at the level of the vocal cords. If you see asymmetric prevertebral soft tissues or an apparently narrowed airway, look at the spinous processes. They should be equidistant from the lateral masses. If they are not, the patient was rotated, and the apparent asymmetry may be an artifact. Repositioning and retaking the film is worth the extra minutes rather than chasing a false positive.
Get the Full Details

The radiation dose is low, roughly 0.01 to 0.05 mSv per view, which is why it remains a reasonable first-line exam in children when clinically indicated. The downside is that dose is only part of the equation. The real cost is the chance of a missed diagnosis when the film is technically suboptimal. I have lost count of the number of times I have seen a film labeled normal that later proved to be expiratory, rotated, or motion-blurred. The workaround is to establish a quick quality assessment checklist at the time of acquisition: inspiration adequate, no rotation, all relevant anatomy included, and adequate penetration to see through the prevertebral tissues without overexposing the air column. There are scenarios where this exam is essentially useless. In patients with known malignancy undergoing radiation therapy, serial soft tissue films add little value compared to CT or MRI. In trauma patients with high-energy mechanisms and neurological deficits, the spine and vascular structures need CT regardless of what the plain film shows. In adults with chronic hoarseness and a suspected mass, direct laryngoscopy and contrast-enhanced cross-sectional imaging are the appropriate next steps. Use the X Ray Of Soft Tissue Neck when the clinical question is acute and focused, not as a screening tool for vague neck complaints. If you want reference material or protocol sheets, most hospital radiology departments publish their own technique guides internally. Publicly available versions exist on institutional websites and in radiology textbooks, but the exact parameters vary by equipment and patient population, so relying on a generic download without matching it to your department's protocols is risky. The principles remain constant: lateral view, full inspiration, proper positioning, and a clear understanding of what the study can and cannot tell you.