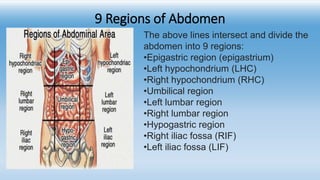
A Practical Guide to the Nine-Region Method
Most people learning clinical anatomy get hit with the surface markings immediately. Draw two vertical lines from the mid-inguinal points up to the costal margins. Draw a transumbilical plane and a subcostal plane. You now have nine boxes. The textbook calls them right and left hypochondriac, epigastric, right and left lumbar, umbilical, right and left inguinal, and hypogastric. It is clean on paper. It is annoying on a real patient. The9th Region Of Abdomen: The Left Iliac Fossa
That last box — the left iliac (or inguinal) region — is the ninth and final subdivision. On the surface, it sounds straightforward. The boundaries are the left mid-inguinal line, the left anterior superior iliac spine, and the approximate midpoint of the inguinal ligament. Underneath that flat surface lie the sigmoid colon, the left ureter crossing the pelvic brim, the descending colon transitioning toward the sigmoid, and in women, the left ovary and fallopian tube. In men, the spermatic cord traverses the inguinal canal near this zone. I used to mark these regions on living patients during clinical skills rotations and kept messing up the left iliac boundary. The problem was not the definition. It was that the anterior superior iliac spine sits at a slightly different level in people who are thin, people with significant adipose tissue, and people who have previously had lower abdominal surgery with altered tissue planes. One morning, a patient's exam was a mess. I had shifted the entire grid downward by roughly two centimeters because I was identifying the wrong bony landmark as my reference point. The fix was simple but easy to overlook: locate the ASIS first, then draw the vertical mid-inguinal line down from the point halfway between the ASIS and the pubic symphysis, not from the umbilicus. The umbilicus moves. The ASIS does not. From an anatomical perspective, the 9th region sits within the pelvic brim's peripheral edge and shares drainage and innervation patterns with structures that extend well beyond its textbook borders. The sigmoid colon receives blood from the sigmoid arteries branching off the inferior mesenteric artery. Lymphatic drainage follows the inferior mesenteric nodes, which track back to the para-aortic chain. This matters when you are tracing pathology. A sigmoid diverticulitis case does not always stay confined to the region you marked on the skin. Clinical examination of the left iliac fossa reveals several patterns that are worth understanding separately. Palpation here is almost never comfortable for the patient if there is active inflammation. The region sits over the sigmoid colon, and if that organ is distended or inflamed, light pressure alone can produce significant tenderness. Deep palpation may elicit a palpable mass in chronic cases of fecal loading or neoplastic processes. Percussion tends to be tympanic over gas-filled bowel loops, but dullness can indicate a solid mass or localized fluid collection. Referred pain is the part that catches people off guard. A left ureteral stone can present with pain localized to the left iliac fossa before it radiates toward the groin and testicle or labia. That migration pattern is consistent but not reliable enough to rule out other causes. I had a patient once who presented with isolated left iliac fossa tenderness that mimicked diverticulitis. CT showed a 4-millimeter stone sitting at the ureteropelvic junction on the left, with only mild secondary changes. The tenderness was almost entirely referred, and the initial exam findings pointed squarely at the colon. Diverticulitis is the diagnosis most residents and medical students associate with this region, and for good reason. In Western populations, left-sided diverticular disease is common after age fifty. The classic presentation involves localized tenderness, low-grade fever, and a change in bowel habits. White blood cell count may be elevated. A CT scan with contrast is the standard next step, and it usually confirms pericolic fat stranding, bowel wall thickening, or a small abscess. The tricky part is that early diverticulitis can present with relatively minimal tenderness, and advanced cases can perforate with surprisingly vague signs in elderly or immunocompromised patients. Ovarian pathology deserves specific attention because the left ovary occupies roughly the same superficial zone as the left iliac fossa. A ruptured ovarian cyst or ovarian torsion can present identically to sigmoid pathology on physical exam alone. Transvaginal ultrasound is the differentiating tool, but it requires the clinical suspicion to be high enough to order it early. I have seen cases where the working diagnosis stayed diverticulitis for too long because the imaging was delayed. Inguinal hernias also present in this region. Direct hernias push through Hesselbach's triangle, which is medial to the inferior epigastric vessels and lies within the general zone of the left iliac fossa. Indirect hernias travel through the deep inguinal ring, which is located lateral to those vessels at approximately the midpoint of the inguinal ligament. The anatomical distinction matters for surgical repair. When examining this area for a suspected hernia, have the patient stand and perform a Valsalva maneuver. Palpate the deep inguinal ring by inverting the scrotal skin on the left side and pressing upward through the external inguinal ring. If a bulge appears just lateral to the pubic tubercle on coughing, it is likely indirect. If it appears more medially, think direct. Imaging considerations for this region are not complicated but require correct sequencing. Ultrasound is appropriate for superficial assessment and can identify hernias, free fluid, and ovarian pathology. CT with intravenous contrast is the workhorse for deeper evaluation of the sigmoid colon, mesentery, and retroperitoneal structures. MRI is rarely first-line here but may be useful in select cases involving pregnant patients or young adults where radiation exposure should be minimized. Plain abdominal radiographs add very little unless you are looking for free air under the diaphragm, which is not specific to the left iliac fossa anyway. The biggest practical limitation of the nine-region system is that it is a surface landmark framework, not a physiological one. Organs do not respect the drawn lines. A massively distended bladder can push upward into the umbilical region and mimic pathology there. An enlarged spleen can extend downward into the left lumbar region and create false tenderness near the border of the left hypochondriac area. The nine-region model is useful for communication and systematic examination, but it is a rough map, not a surgical blueprint. When documenting findings, I recommend specifying both the named region and the underlying structure you are concerned about. Instead of writing tenderness in the left lower quadrant, note tenderness in the left iliac fossa suggestive of sigmoid involvement or possible ovarian pathology. Precision matters more when you are handing a patient off to another clinician who will interpret your notes without seeing them.Summary of Key Points
The 9th region corresponds to the left iliac fossa and contains the sigmoid colon, left ureter, left ovary or fallopian tube, and adjacent vascular and lymphatic structures. Surface marking errors usually come from using the umbilicus as a fixed reference point. Use the anterior superior iliac spine and pubic symphysis instead. Left iliac fossa pain has a narrow differential that includes diverticulitis, ureteral colic, ovarian pathology, and inguinal hernia. Imaging selection depends on the suspected etiology.
The nine-region system is a practical teaching and communication tool, but clinical correlation with imaging and laboratory data is essential because organs do not conform to grid lines.


