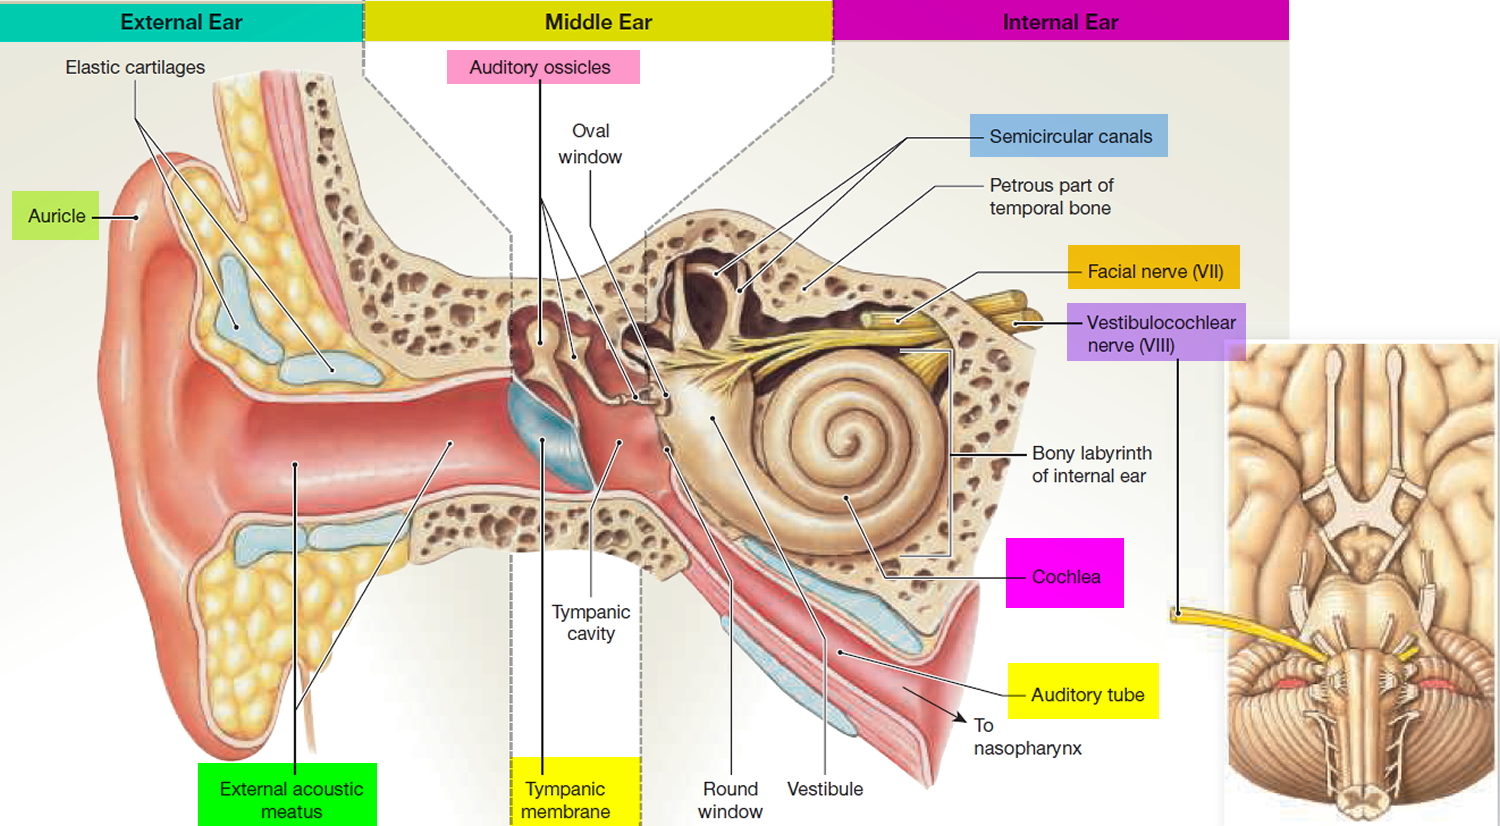
What You Actually Need When Working With Ear Anatomy Images
Most people searching for Anatomy Of Ear Images are looking for something simpler than what they end up finding. They want a clean diagram. They download a textbook illustration. Then they realize the resolution isn't good enough for their project, or the labels are in the wrong language, or the image shows the external ear when they needed the middle and inner structures. I've been through this cycle enough times that I stopped treating it like a surprise. The ear is one of the most structurally complex areas in the human body packed into a space smaller than a deck of cards. That complexity is exactly why generic stock images rarely work for anything beyond basic presentations. If you're doing medical education, patient counseling, or anatomical illustration work, the difference between a decent image and a good one is usually measured in whether the stapes footplate is visible or completely absent.
Where to Source Reliable Anatomy Of Ear Images
I don't recommend paid stock photo sites for serious anatomical work. The images there tend to be overly stylized or poorly labeled. Your best starting points are open-access medical databases and university publications. Figures from the Anatomical Sciences Education journal, OpenStax Anatomy, and the Visible Human Project from the National Library of Medicine are all solid sources. These materials are typically released under licenses that allow redistribution with attribution, which matters if you're building educational content. For three-dimensional reconstructions, the Visible Body and Complete Anatomy platforms produce technically accurate models, though their licensing restricts screenshot use in published material. I've used them extensively for personal reference and verification, but I always cross-check any image pulled from those tools against a peer-reviewed source before using it in anything public-facing. One thing I learned the hard way: images sourced directly from radiology textbooks often show pathological conditions disguised as normal anatomy. A CT scan labeled "normal temporal bone" from a case report may actually display otosclerosis or congenital stapes fixation. Always verify the caption and original context. This cost me about three weeks rewriting a patient education handout when a reviewer flagged the image I'd included.
Understanding What Makes These Images Useful
A good ear anatomy image does three things: it shows spatial relationships correctly, it uses consistent labeling conventions, and it matches the intended anatomical plane. Coronal sections, axial CT slices, and external otoscopic views each serve different purposes. Mixing them without understanding the plane mismatch is one of the most common errors I see in student and practitioner work. The tympanic membrane, for instance, sits at roughly a 55-degree angle to the horizontal canal in adults. Images that depict it as a vertical drum are technically incorrect, even if they look fine at a glance. This matters when you're explaining myringotomy procedures or cerumen impaction pathways to anyone who will actually be looking at the geometry. Another detail most people overlook: the ossicular chain isn't a rigid lever system. The incudostapedial joint allows micromovement, and the tensor tympani and stapedius muscles modulate tension dynamically. Static diagrams that show the ossicles locked in position give a misleading mechanical picture. If your work requires understanding sound transmission, you need images that either show musculature attachment points or come with a accompanying explanatory note about dynamic function.
Get the Full Details

I encountered a specific problem last year where a client needed high-resolution ear anatomy imagery for a surgical planning interface. The standard coronal MRI sequences available online had insufficient contrast resolution at the round and oval window boundaries. What worked was running a dedicated temporal bone CT protocol with 0.625mm slice thickness and applying a bone algorithm reconstruction. The resulting DICOM files were then converted to PNG exports at 1600 DPI using Horos on macOS. This gave us clear visualization of the facial nerve dehiscence points and the sinus tympani depth that the generic images simply couldn't provide. The whole workflow took about forty minutes once I had the protocol parameters memorized.
Common Pitfalls That Waste Time
The first trap is assuming more detail is always better. A fully labeled diagram showing every ligament, nerve branch, and vascular structure in the ear often becomes less useful than a cleaner image that highlights the relevant structures for your specific use case. I've found that for patient education materials, showing the ossicles with their basic connections is enough. Adding the chorda tympani path, while anatomically correct, usually confuses the audience rather than helping them. The second pitfall is color consistency across your image set. Medical illustration standards typically use blue for venous structures, red for arterial, and yellow for neural tissue. When you pull images from multiple sources, those conventions get mixed up. I once assembled a nine-image series from different textbooks and spent two hours re-coloring the vessel maps because half of them followed one convention and the other half followed none. A third issue is aspect ratio and resolution mismatch. If you're combining images for a publication or presentation, ensure they all share the same pixel dimensions and DPI setting. I use 300 DPI for print-bound work and 72 DPI for screen-only materials. Anything in between usually means you're carrying unnecessary file weight without gaining visible quality.
When Generic Images Simply Don't Work
There are scenarios where no pre-made image will suffice. Pediatric ear anatomy differs substantially from adult anatomy, particularly in the angle and length of the external auditory canal. Neonatal canals are shorter, more horizontal, and the tympanic membrane sits at a flatter angle. Most standard image libraries don't account for this variation, which is why I maintain a separate collection of pediatric-specific references drawn from Otolaryngology Head and Neck Surgery clinical atlases and peer-reviewed case compilations. Pathological variants present another limitation. Images of ears with cholesteatoma, tympanosclerosis, or congenital atresia are extremely difficult to source cleanly. Commercial image databases actively avoid publishing these due to patient privacy concerns and editorial policies. If your work requires showing disease states, you're generally looking at accessing clinical journals directly or collaborating with medical institutions that have de-identified imaging libraries available for research purposes. Another hard boundary: animated or interactive representations of ear anatomy require specialized software like Blender with anatomical addon packages, or dedicated medical visualization platforms. The learning curve for producing even basic animation is steep. I spent roughly six weeks learning the basics of mesh topology in Blender before I could produce a simple stapes vibration animation that was anatomically defensible. If you need motion graphics, budget that time accordingly rather than assuming a tutorial will get you there in a weekend.
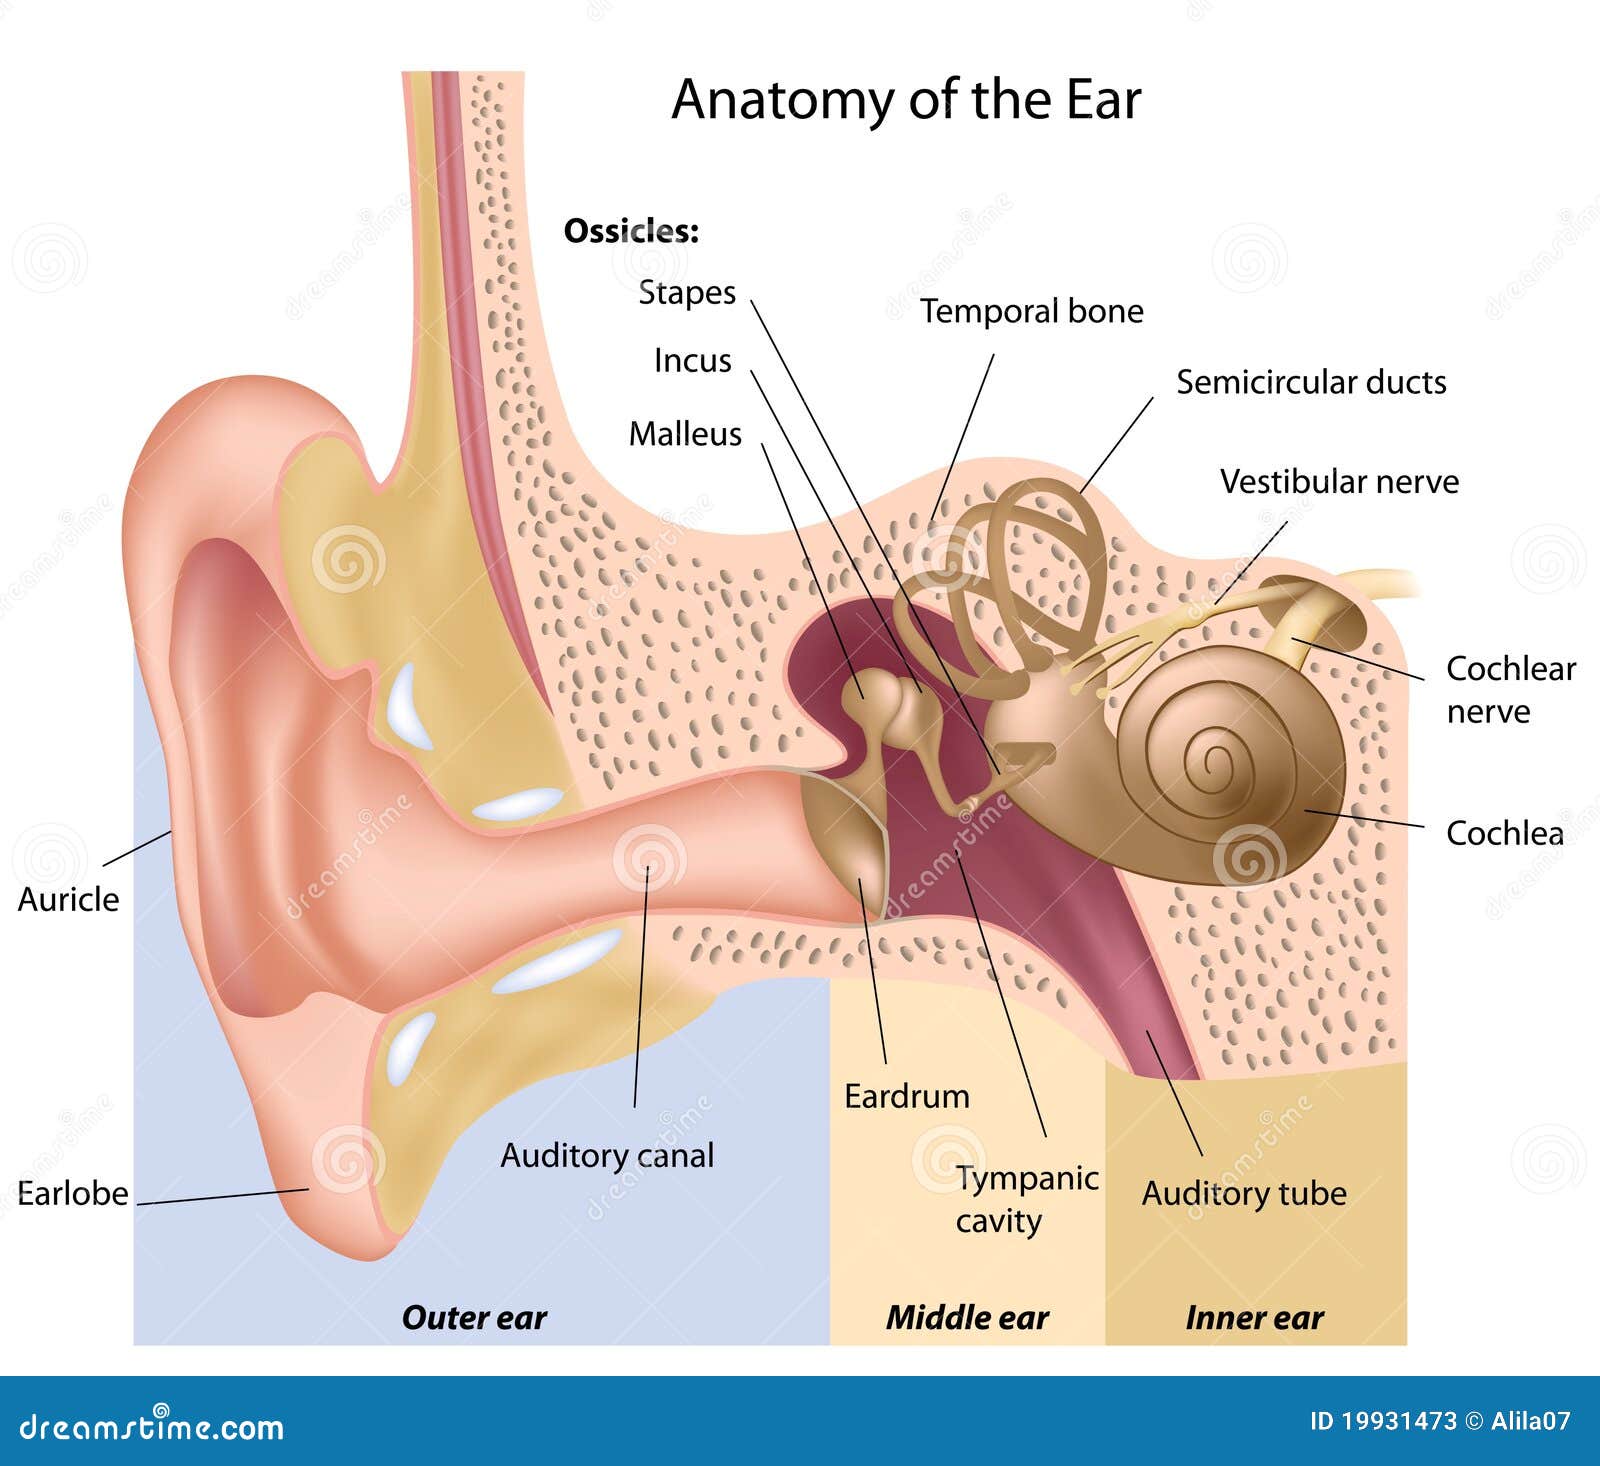
My Practical Workflow for Anatomy Of Ear Images
Here's what my actual process looks like when I need a set of reliable ear images for a project. I start by pulling primary sources from the Visible Human Project and any relevant OpenStax figures. I verify each image against a second source before committing to it. I then standardize the resolution by upscaling only when necessary using AI-assisted tools like Upscayl or topaz gigapixel, though I avoid AI upscaling for images that contain fine text labels since the algorithms tend to distort letterforms. For any image I plan to modify or annotate, I convert it to SVG format using vectorization tools, which lets me adjust colors and line weights without degrading the source material. I keep a running folder organized by anatomical region: external ear, middle ear, inner ear, and neurovascular structures. Each image gets tagged with its source, license type, and resolution in a simple spreadsheet. This system takes about fifteen minutes to set up initially but saves me approximately twenty minutes per project on source verification and metadata lookup. That might sound minor, but it adds up over the course of a year if you're working with these images regularly. The main limitation of this approach is that it depends entirely on the quality and licensing of the source material. If a source image is low resolution to begin with, upscaling won't recover detail that was never captured. No amount of post-processing will turn a 200 DPI web image into something suitable for print at 300 DPI without visible artifacting. Always check the original resolution before investing time in enhancement workflows.