Understanding Body Planes And Sections In Practice
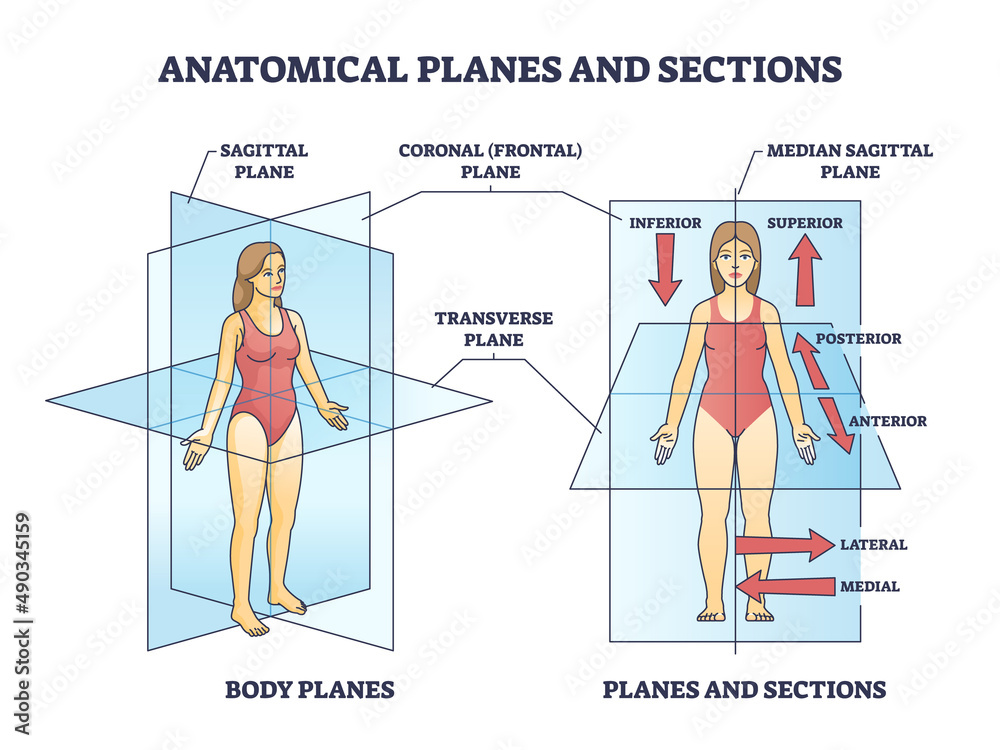
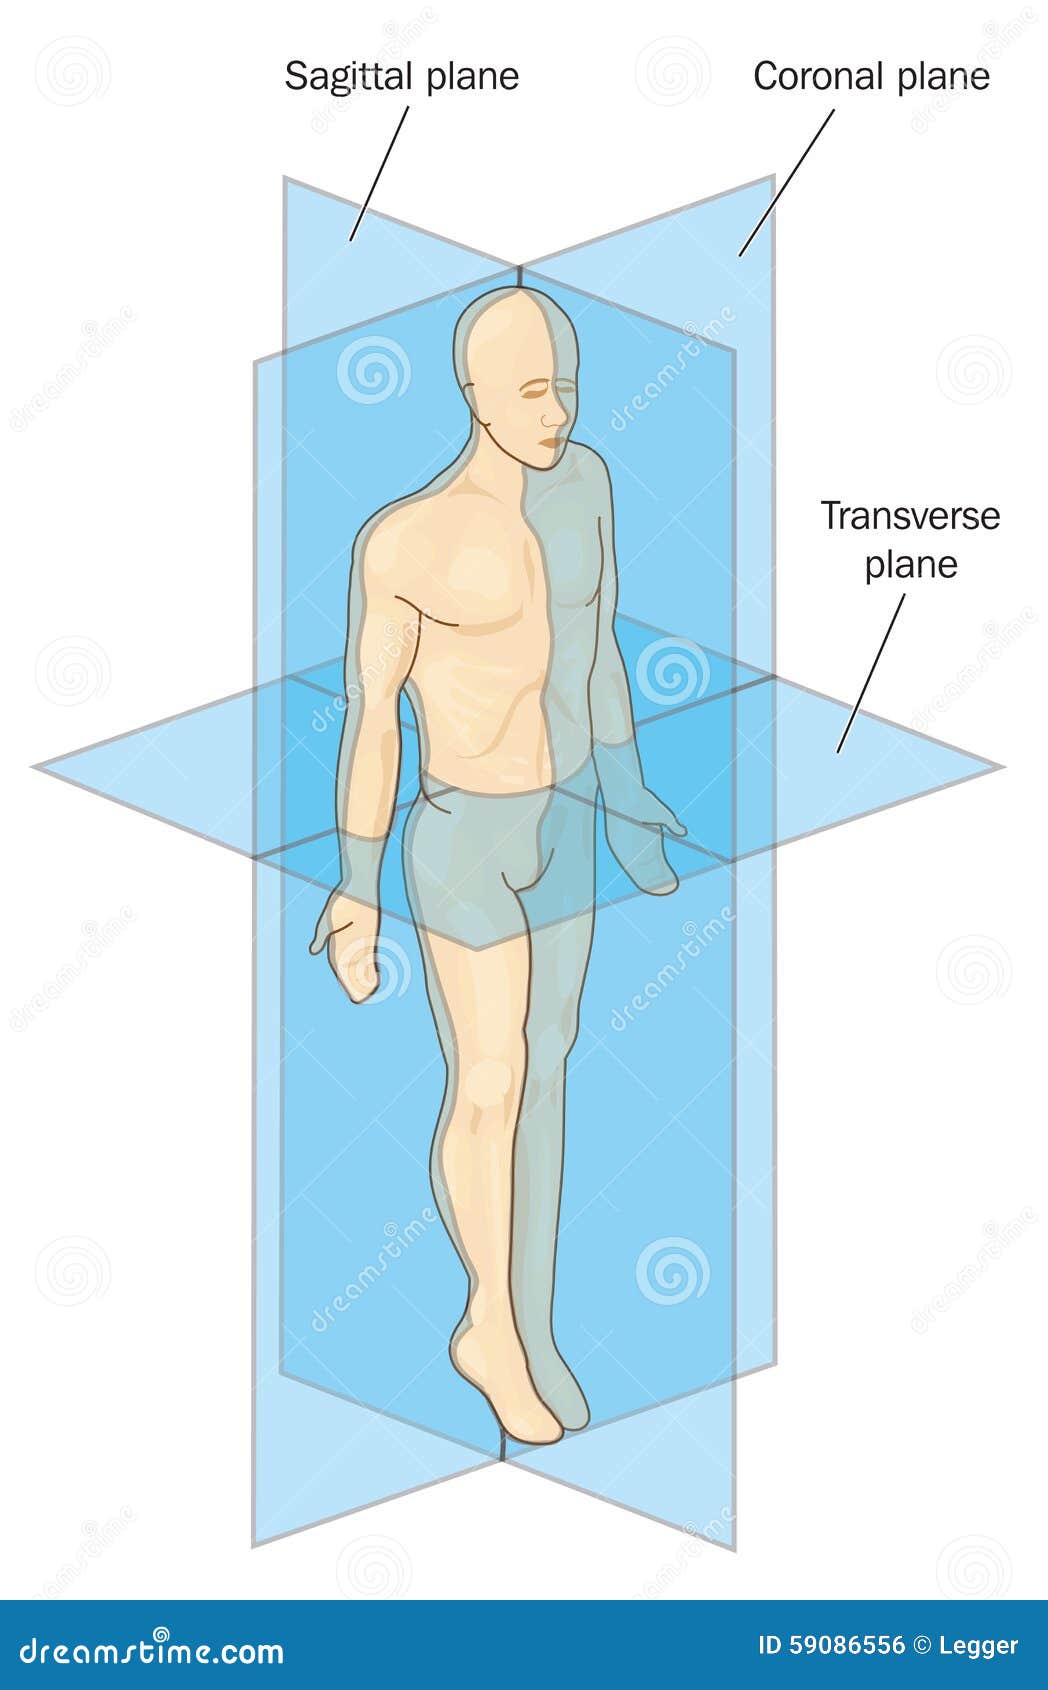
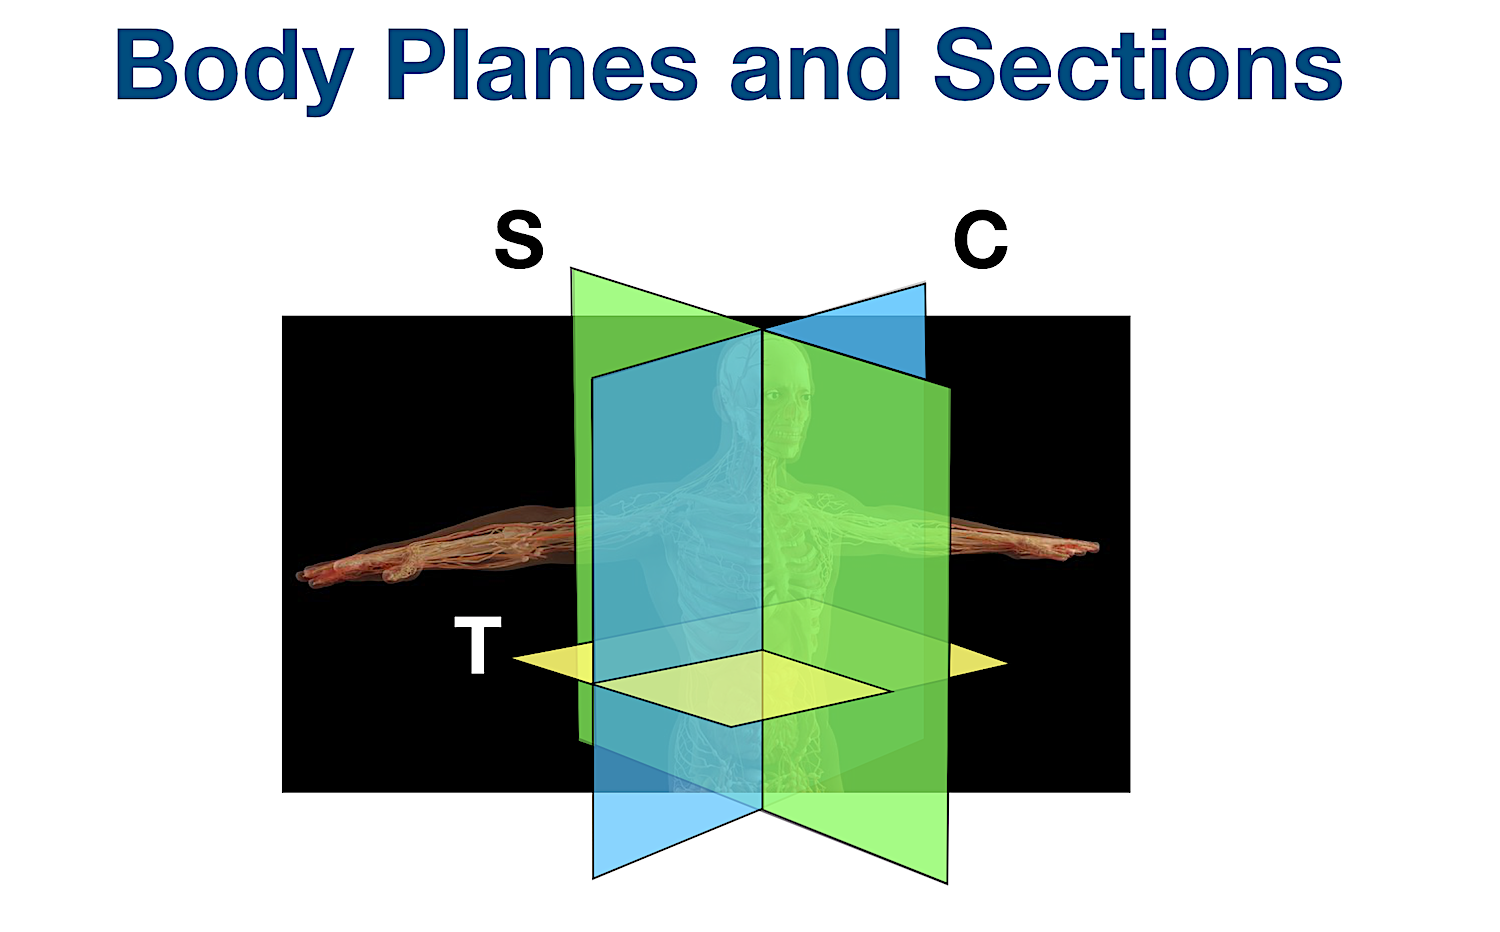
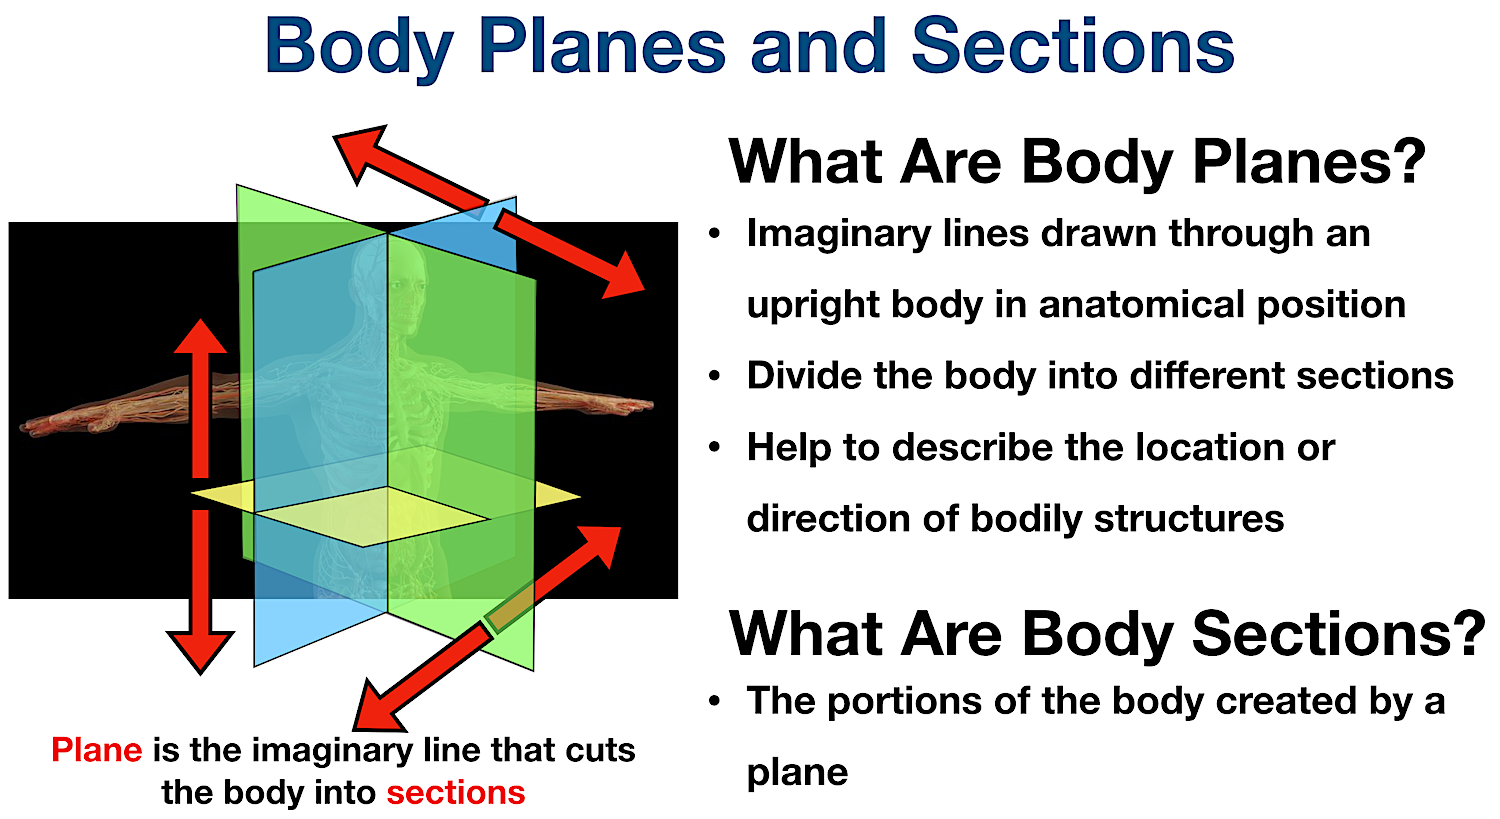
The whole concept gets taught as if everyone just visualizes these orientations naturally, but the first time I tried to correlate a CT scan with an anatomical diagram, I spent twenty minutes rotating the image in my head before it clicked. That's normal. Let me walk through how this actually works. A plane is an imaginary flat surface that slices through the body. A section is what you see when you cut along one of those planes. There are three standard planes everyone uses, and the names come from old anatomical Latin, which makes them harder to remember than they need to be. Sagittal plane runs vertically from front to back. When it splits the body into left and right portions, that's the mid-sagittal plane, and it passes right through the nose, spine, and navel. Any sagittal plane parallel to that one just shifts left or right. The problem with sagittal cuts is that radiologists often lose orientation when looking at spine imaging because the vertebrae create repeating patterns that make it easy to confuse superior with inferior.
Coronal plane also runs vertically but splits the body into front and back sections. Think of a face mask plane. When I first started reading abdominal CTs, I kept mixing up coronal and sagittal views, especially with the liver and spleen on opposite sides. The workaround I settled on is to always check for the heart first. The heart's apex points left, so if the heart appears on the left side of your image, you're looking at a standard coronal view. Transverse plane, sometimes called axial or horizontal, cuts the body into top and bottom portions. This is the plane most CT and MRI scanners are acquired in, which means it's the default view for modern imaging. The tricky part here is that transverse sections through the abdomen can look deceptively similar between adjacent slices. I usually scroll through five to ten slices at a time rather than studying one in isolation, which helps me spot structures like the aorta, IVC, and kidneys before getting bogged down in details.
Practical Applications And Common Mistakes
The real value of understanding these planes shows up when you need to localize pathology or plan surgical approaches. Surgeons use coronal and sagittal reconstructions from CT data to map out tumor boundaries before operations. If you're learning this for ultrasound, you'll immediately notice that transducers can be rotated to match any of these planes depending on where you place them on the body surface. One specific problem I ran into: When reading knee MRIs, the cruciate ligaments appear at slightly different angles depending on whether the slice is truly sagittal or just tilted. I used to miss anterior cruciate ligament tears because I assumed the slice was perfectly aligned. The exact workaround I adopted is to verify the tibial plateau shape on adjacent slices. If the plateau appears roughly rectangular, you're probably in sagittal orientation. If it looks more circular or oval, the slice has likely drifted into oblique territory. Counter-intuitive insight: Most beginners memorize the planes as static concepts, but in clinical practice, these planes rarely align perfectly with standard anatomical position. The patient might be supine, prone, or rotated during scanning. I always check the position marker on the image first before assuming the planes are standard. Some older scanners display rotation angle metadata that tells you exactly how far the acquisition deviated from true anatomical planes.
Get the Full Details
Another common pitfall: When correlating surface anatomy with internal structures, people assume the planes are symmetrical. They're not. The liver sits mostly on the right, the stomach on the left, and the heart is off-center toward the left chest. If you expect perfect symmetry when using transverse sections through the upper abdomen, you'll misidentify organs within about thirty seconds.
Limitations And When This Approach Fails
These three planes work well for most diagnostic situations, but they completely break down when dealing with complex trauma or congenital anomalies where organ positioning is abnormal. In those cases, I switch to multi-planar reformation software that generates custom planes through the region of interest, though that usually adds twenty to forty minutes to the reading time depending on your workstation speed. When to use alternative approaches: For cardiovascular imaging, especially cardiac CT, the standard planes don't capture the heart's complex 3D geometry well. I usually request short-axis and long-axis views generated specifically through the left ventricle, which cuts ejection fraction measurement time from about fifteen minutes down to roughly three minutes once you're comfortable with the orientation. A blunt observation: Many textbooks present body planes as clean, theoretical concepts with perfect examples. Real clinical images are noisy, patients move, and slice thickness varies between five and ten millimeters depending on the protocol. If you're studying from idealized diagrams alone, you'll struggle to recognize these planes in actual patient scans for at least two to three weeks until your brain adapts to the messiness of real imaging.
The takeaway is practical: memorize the three standard planes, but spend more time correlating them with actual CT, MRI, and ultrasound images. I usually review fifty to one hundred cases across all three planes before feeling confident, and even then I reference anatomy atlases regularly. This isn't something you master once and never think about again.