Explaining OCD to Other People
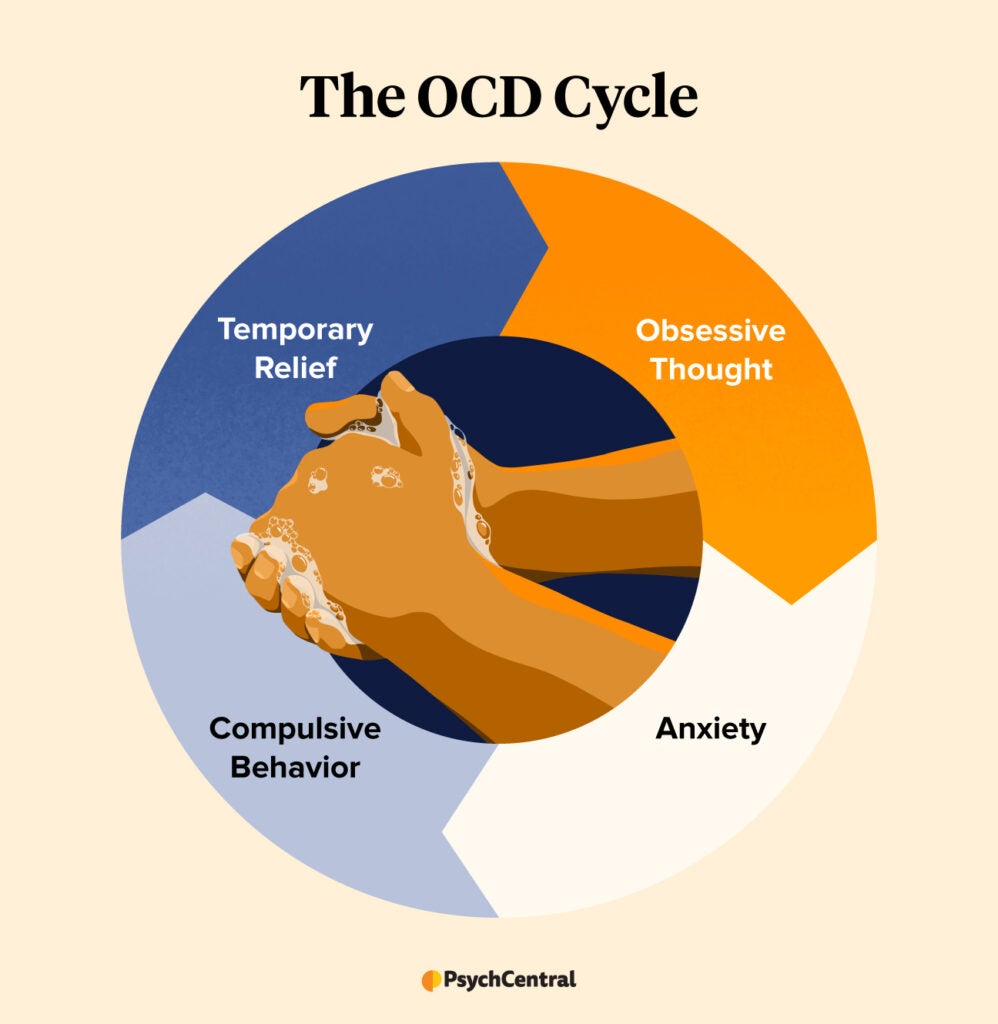
I get asked this constantly, both online and in my work, so here is the straightforward version of how I handle talking about obsessive-compulsive disorder with people who aren't in the mental health space. Start by separating the two halves. Obsessions are intrusive thoughts, images, or urges that show up without warning and stick around. Compulsions are the behaviors or mental acts people do to neutralize the anxiety those thoughts create. Most folks think OCD is just liking things organized or washing hands a lot. That stereotype gets in the way of understanding what it actually is, and it makes people dismiss real suffering. When I explain it, I lead with the function, not the surface behavior. The organizing, the checking, the counting, the mental reviewing — these aren't preferences. They are attempts to prevent something terrible from happening or to make an unbearable feeling go away. That distinction matters because it changes how someone listens.
I remember working with a client whose obsessions centered on causing harm to their family through negligence. They'd check the stove seven times before leaving the house. People hearing that story for the first time often assume it's just a habit. It's not. The compulsion only works temporarily. The anxiety comes back worse within minutes, which is why the cycle is so exhausting and why willpower alone doesn't break it. Exposure and Response Prevention, commonly called ERP, is the gold standard treatment and it directly targets this mechanism. You expose yourself to the trigger and deliberately don't perform the compulsion until the anxiety drops on its own. That process takes weeks and a trained therapist, usually starting with a hierarchy of triggers ranked from least distressing to most. Here is a practical script I use when someone asks how to explain OCD to their partner or coworker: Say what the obsession is — the actual fear driving the behavior. Then name the compulsion. Then explain the cycle. Keep it short. Adding clinical jargon confuses more people than it helps. "I have intrusive thoughts about contamination and I wash my hands until my skin cracks" is more useful than reciting DSM criteria.
There are some things that don't work and I should mention them bluntly. Reassurance is one of them. When someone with OCD asks "Are you sure the door is locked?" and you say yes for the third time that hour, you aren't helping. You're feeding the cycle. Short, neutral answers are better. You can say "I know that feels uncertain right now" without confirming or denying the specific fear. It sounds harsh at first but it's the only direction that actually reduces symptoms over time. Another common mistake is treating OCD like a personality quirk. Humor-based descriptions like "I'm so OCD about my desk" trivialize a condition where people can spend hours on rituals and still feel nothing is ever secure. I've had people tell me this is just being neat, and it isn't. The difference is distress level and functional impairment. If your ordering ritual isn't causing you significant anxiety or eating into your day, you probably just like order. For people who want to learn more on their own, there are several solid resources. The International OCD Foundation maintains a directory of therapists who specialize in ERP. The Mind Over OCD podcast has practical interviews with people in treatment. Books like Freedom from OCD by Jonathan Grayson and Loving Q I'm Sorry by Paul Fyer offer detailed self-help frameworks, though they work best alongside professional guidance rather than replacing it.
Get the Full Details

The hard part nobody tells you about explaining OCD is that even after you explain it well, people will still misunderstand. They'll say things like "just stop doing it" or "it's all in your head." That's frustrating. I've sat through family therapy sessions where parents accused their adult child of making the disorder up because they couldn't see visible evidence. The most useful thing I've found is pointing people toward lived-experience content. A ten-minute video of someone describing their actual internal experience often does more than any clinical explanation I could give. If you're dealing with this yourself and looking for a way in, start by mapping your own cycle. Write down one obsession, the compulsion that follows, and how long the relief lasts. This gives you a concrete starting point for therapy instead of walking into a session and saying "I have OCD" without context. Therapists need specifics to build an effective ERP plan. A simple log over two weeks is usually enough to identify patterns. OCD is treatable. That's not a platitude. ERP has response rates in the 70 to 80 percent range for people who stick with it. The bottleneck isn't the treatment, it's access and persistence. Good ERP therapists are hard to find in some regions, and the work is uncomfortable. You will feel worse before you feel better because you're intentionally facing fears without the safety behaviors you've relied on. That discomfort is temporary and it's the mechanism of change, not a sign the treatment is failing.
If you're talking to someone who has OCD, the single most helpful thing you can do is stop being their reinforcement engine. Don't participate in rituals. Don't offer reassurance. Be kind but firm about boundaries. That's it. It feels cold at first. It isn't cruel. It's how you actually help them get better.