What Actually Happens During Decompression
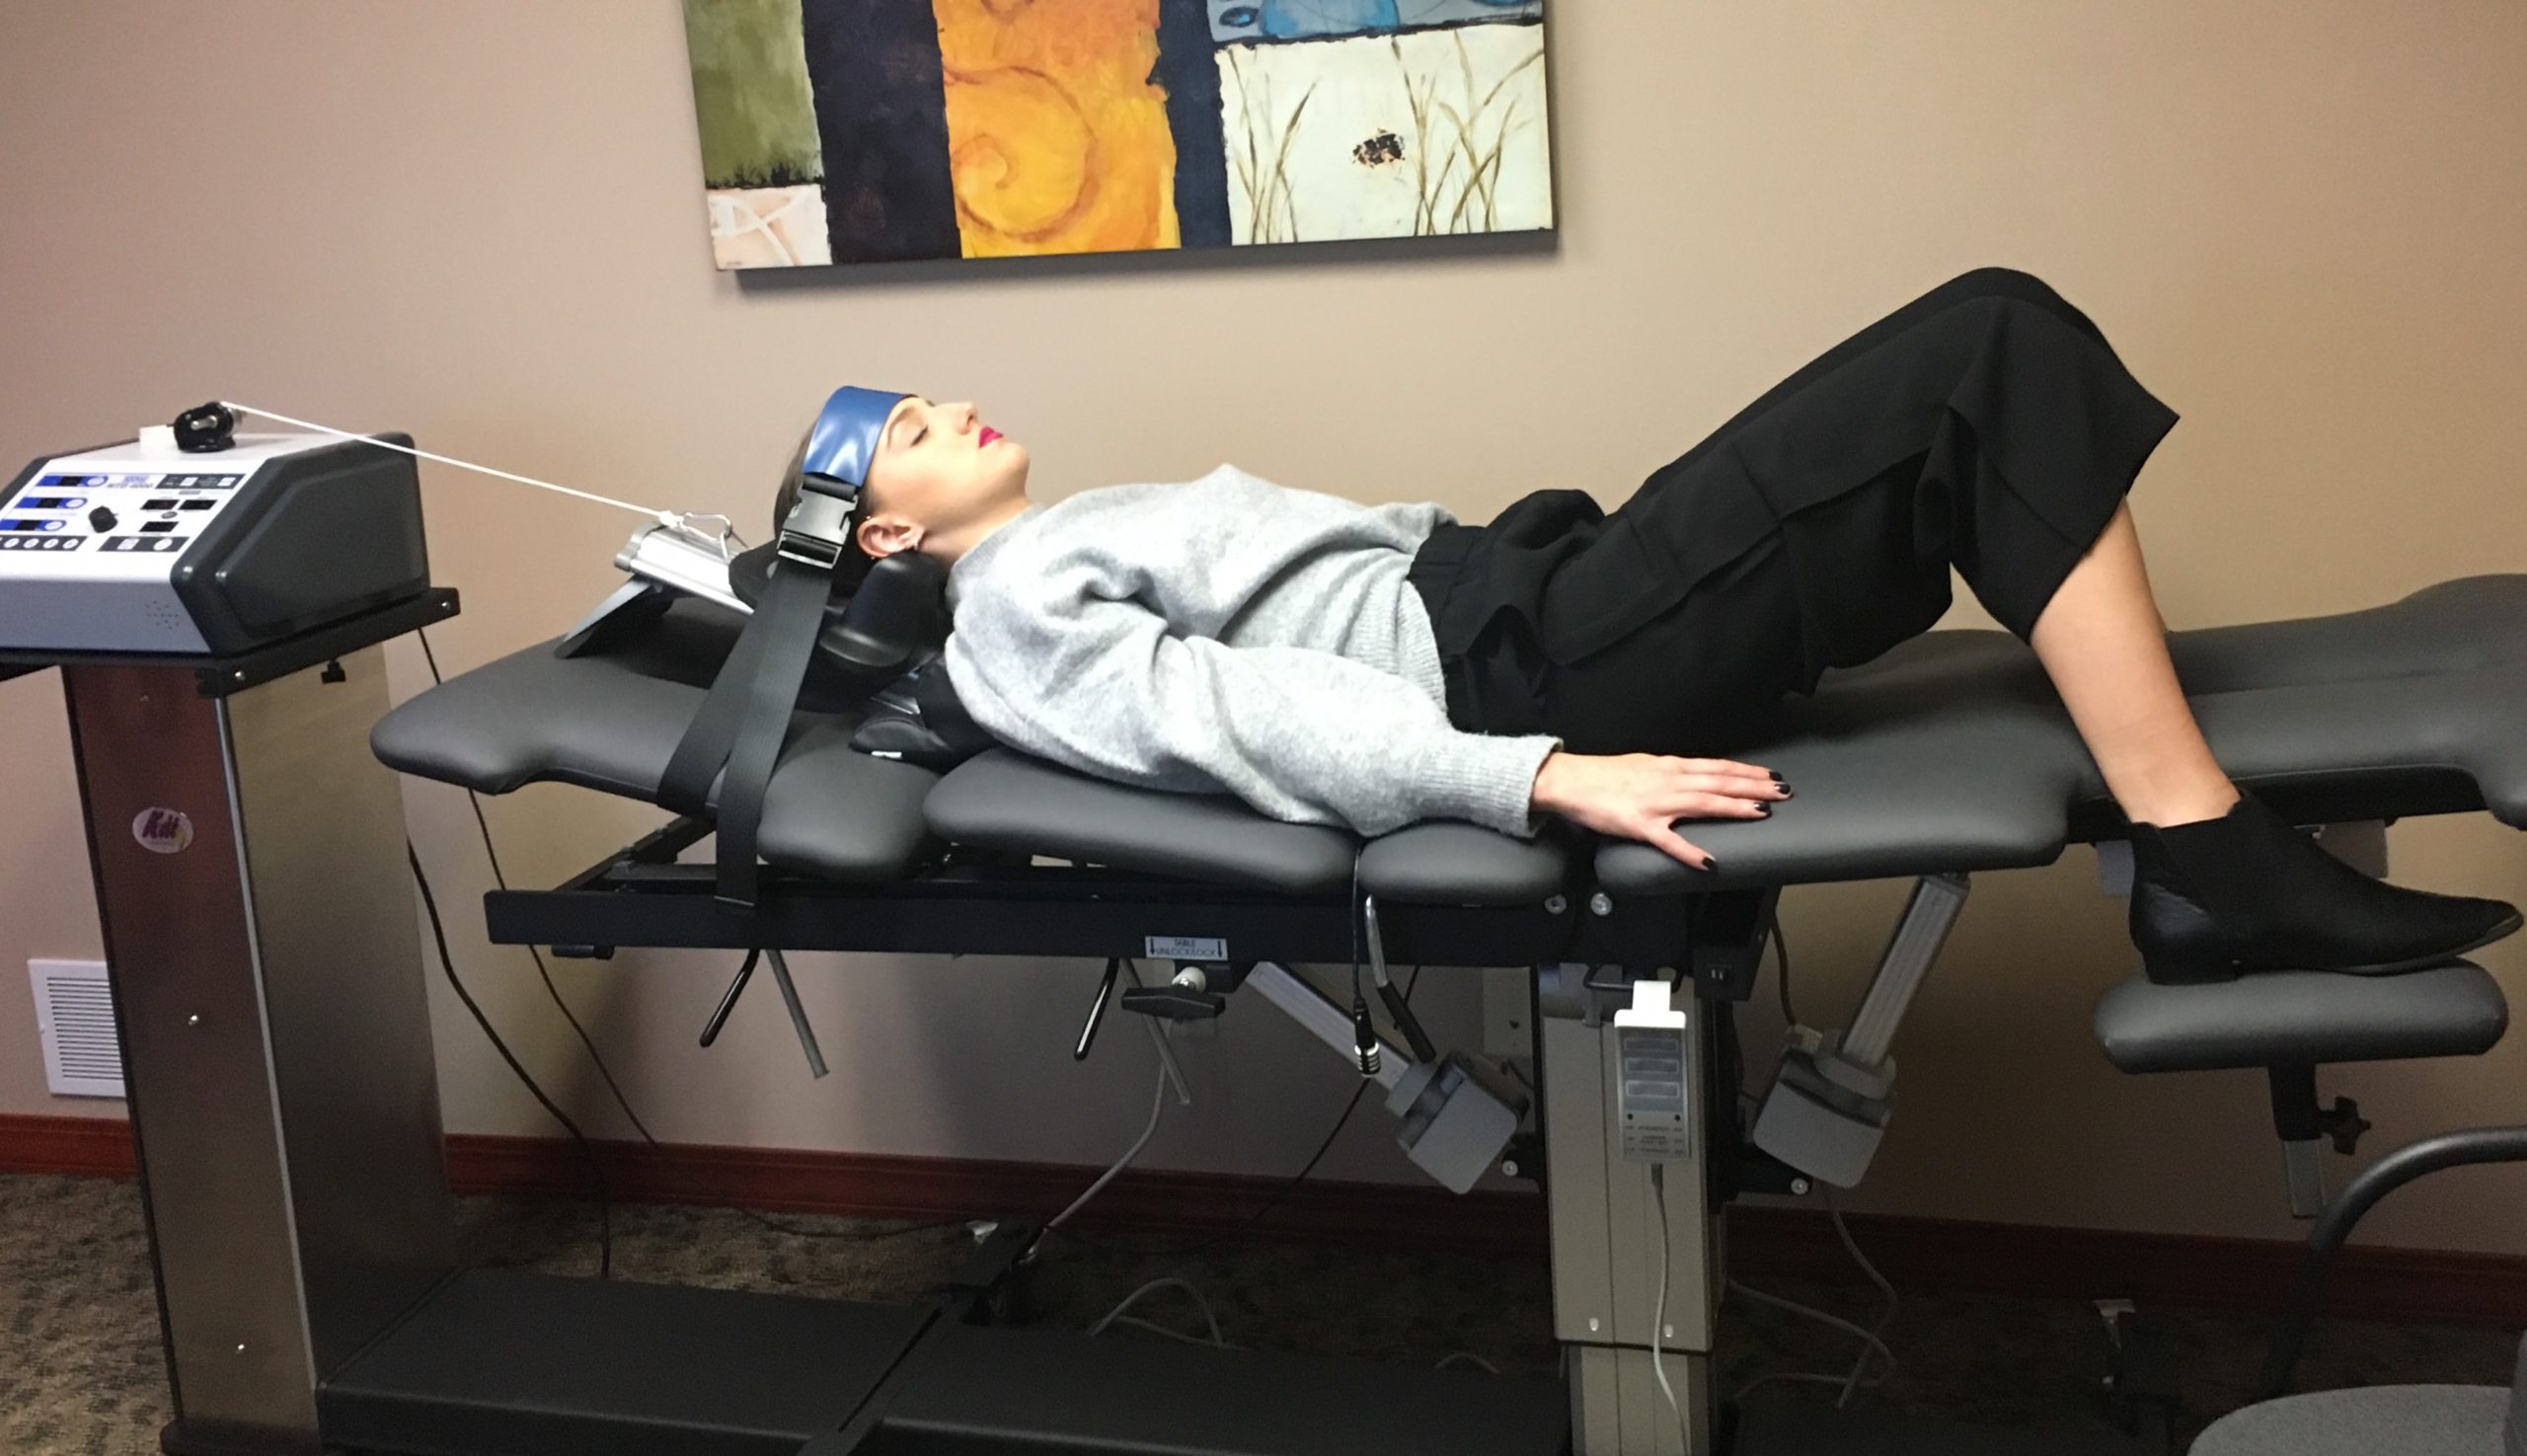
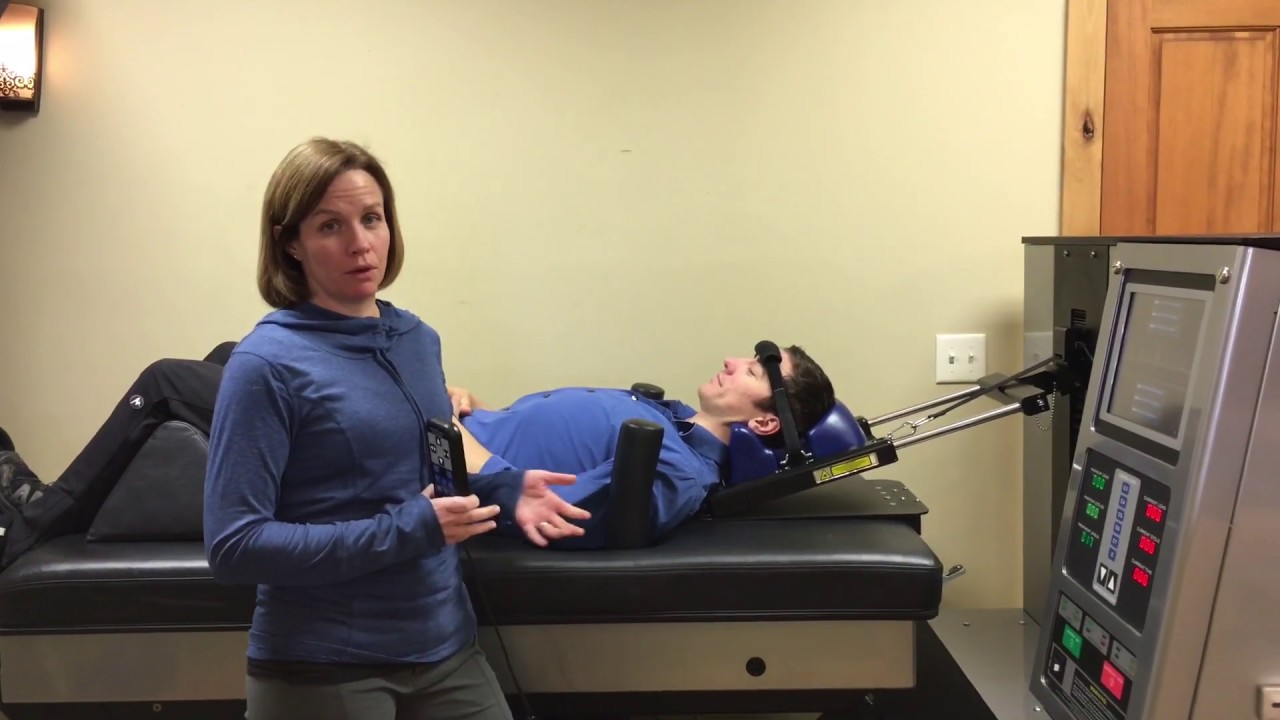
A patient lies on a table, usually supine or prone depending on the device. A harness goes around the head or pelvis. The motor pulls in one direction while the body is anchored. The goal is separating the cervical vertebrae by a few millimeters—typically 20 to 30 pounds of force sustained for 15 to 30 minutes per session. That’s it mechanically. The disc space opens, intradiscal pressure drops, and nerve roots get a little more room. I’ve run this protocol on roughly two thousand patients over the last decade. The thing nobody tells you is that most people with a diagnosed disc herniation feel no change in the first three sessions. They sit there for 30 minutes thinking nothing’s happening. Then around session four or five, their arm stops tingling at night. That’s when you know the mechanism is working, even though they didn’t feel a thing beforehand.
Cervical Spine Decompression Therapy Settings That Actually Work
Force matters more than time, but only up to a point. Anything over 40 percent of body weight and you start pulling ligaments instead of creating space. For a 180-pound male, that’s roughly 72 pounds of pull—and that’s way too aggressive for most cervical cases. Start at 25 percent. Eight to twelve pounds of force. Build from there. Hold for 20 minutes. Four times a week for three weeks, then reassess. The angle is where people go wrong. The neck should be neutral, not flexed or extended. I had a colleague who set his machine to 15 degrees of flexion thinking it would target the posterior disc. Patient left with a worsened disc bulge. Flexion closes the posterior space. Extension opens it. Don’t be that guy. Lock the neck at zero, pull straight down the long axis of the spine.
Who This Helps and Who It Won’t
Radiculopathy from a soft disc herniation responds best. Nerve root compression showing dermatomal pain, positive Spurling’s test, MRI confirmation of foraminal narrowing. Those patients see improvement in 60 to 70 percent of cases. You’ll know within two weeks whether it’s going to work for them. Spondylolisthesis, especially grade 2 or higher, is a hard stop. Pulling on an unstable segment just makes things worse. Calcified discs don’t respond either—the material has become too hard to shift with traction forces. And osteoporotic spines. I lost a patient once to a vertebral compression fracture during what I thought was a gentle session. Force gauge read 20 pounds. She was 78, on prednisone for six months. The bone just couldn’t take it. Order a DEXA scan before you ever put a harness on someone older than 65 without screening.
Get the Full Details

Device Types and What They Actually Cost
There are three categories. Manual decompression tables, like the DRX9000 or spine-oc systems—these run $40,000 to $80,000 new. You’ll find refurbished units for $15,000 if you know how to inspect the hydraulics. Inversion tables are the budget option, $200 to $600, but they’re unreliable for cervical work. The force is body-weight dependent, not calibrated, and you can’t hold a steady draw for 20 minutes while lying upside down without your grip failing. Desktop units for clinics, the mid-range tier, cost $8,000 to $15,000. These give you programmable cycles, force limits, and real-time monitoring. They’re the workhorses. I’ve had one run for 4,000 hours across six years with only a pump seal replacement at year three. If you’re a home user, be honest with yourself. The insurance doesn’t cover it, the evidence base for home units is thin, and most of the cheap devices on Amazon just dangle your head at awkward angles without controlled force. I wouldn’t recommend spending more than $300 on anything labeled “home cervical decompression” unless you have a practitioner supervising your settings.
Protocol I Actually Use
Session structure: five-minute gradual ramp-up, 20-minute therapeutic hold, three-minute ramp-down. Never drop force suddenly—that’s when patients get headaches or neck spasms. Hold at 20 to 25 pounds for cervical cases unless the patient tolerates more. Monitor for comfort. If they’re grimacing or holding their breath, you’re pulling too hard. Frequency: three to four times weekly. Space sessions at least 48 hours apart. Daily decompression causes ligamentous creep—those tissues stretch past their elastic limit and never snap back. You’ll have a patient with permanent neck laxity within eight weeks if you go too hard, too often. That’s not a theoretical risk. I’ve seen it twice. Adjuncts matter more than patients expect. Soft tissue work before decompression reduces muscle guarding. Ice after, not before. Posture education is non-negotiable—if they return to eight hours of forward head posture the same day, you’ve wasted your time. Chin tucks, scapular retraction cues, ergonomic workstation setup. Give them a handout. I print one every single visit.
When I Switch Strategies
If there’s no meaningful change after six sessions, I stop. Not because the method is broken, but because this patient isn’t a candidate. Some disc pathologies simply don’t decompress well. Lateral recess stenosis from facet hypertrophy won’t respond to traction—you need extension-based relief or surgical decompression. Foraminal stenosis from osteophytes needs a different angle, sometimes prone positioning with rotation to open the contralateral foramen. My fallback when decompression plateaus: McConnell taping for acute radicular pain, graded nerve glides for neural sensitivity, and if the MRI shows significant structural compromise, a referral for consultation. I’ve had surgeons thank me for catching cases early enough that they chose fusion over discectomy. Those calls save a lot of downstream problems.

Red Flags That Stop Everything
Myelopathy signs—gait disturbance, hyperreflexia, Babinski, bowel or bladder changes. Any of these and decompression becomes contraindicated. You’re already dealing with cord compression; pulling on the spine adds variable. Imaging and neurosurgery consultation, not another session on my table. Severe osteoporosis, spinal tumors, infections, recent fractures, advanced rheumatoid arthritis with atlantoaxial instability. I screen for these with history and imaging before the first session. A simple cervical X-ray series catches most of the dealbreakers. I’ve made it a habit to request imaging from the referring MD before accepting a decompression case, and I ask specifically about bone density, alignment, and any prior surgeries.
What the Literature Actually Says
The evidence is mixed but favors clinical use for specific indications. A 2022 systematic review in the Journal of Orthopaedic & Sports Physical Therapy found moderate-quality evidence supporting decompression for cervical radiculopathy, with effect sizes comparable to manual therapy plus exercise. The studies that showed no benefit usually had poor protocol fidelity—varying force, inconsistent duration, no standardization. That’s not the method failing; that’s the research design failing. Cost-effectiveness data exists but is thin. One modeling study put the per-patient cost at roughly $400 to $600 for a full course, compared to $2,000 to $4,000 for epidural injections and $15,000 to $25,000 for surgery. Those numbers held up across payer types, though the sample sizes were small. The long-term outcomes are what keep me using this. Five-year follow-up data suggests patients who complete a full decompression protocol plus exercise program have 40 to 50 percent lower re-treatment rates compared to injection-only cohorts. That’s clinically meaningful. It’s also why I push compliance on the rehab side harder than I push on the machine time.
My Real-World Edge Case
Three years ago I had a patient with a C6-C7 herniation, right-sided weakness, and a paradoxical response. Every time I increased force past 18 pounds, his symptoms got worse. Below 18, he tolerated it fine. Standard protocol would have me pushing gradually—I did the opposite. I kept him at 12 pounds, held there for 25 minutes, added manual traction between sessions, and saw gradual improvement over six weeks. The lower force wasn’t creating more space; it was avoiding a positional irritation I couldn’t explain on imaging. MRI looked clean. His disc was still herniated, but the mechanical tolerance was just lower than expected. I don’t have a neat theory for why 18 was the threshold, but respecting it worked better than fighting it. That’s the thing about this work. The textbook protocols are starting points, not rules. Every spine is different, every nerve root has its own pain threshold, and the machine doesn’t know what’s happening inside that patient’s neck. You do. Pay attention to what they tell you, not just what the gauge says.