What Most CBT Training Programs Get Wrong
Most Cognitive Behavioral Therapy Curriculum packages I've seen skip straight from theory to role-play without properly covering the structural elements that make sessions actually work. I spent three years building a curriculum from scratch after watching too many trainees freeze mid-session because they knew the model but couldn't map a client's narrative onto it in real time. Here is how I ended up organizing it.
Building a Cognitive Behavioral Therapy Curriculum That Actually Works
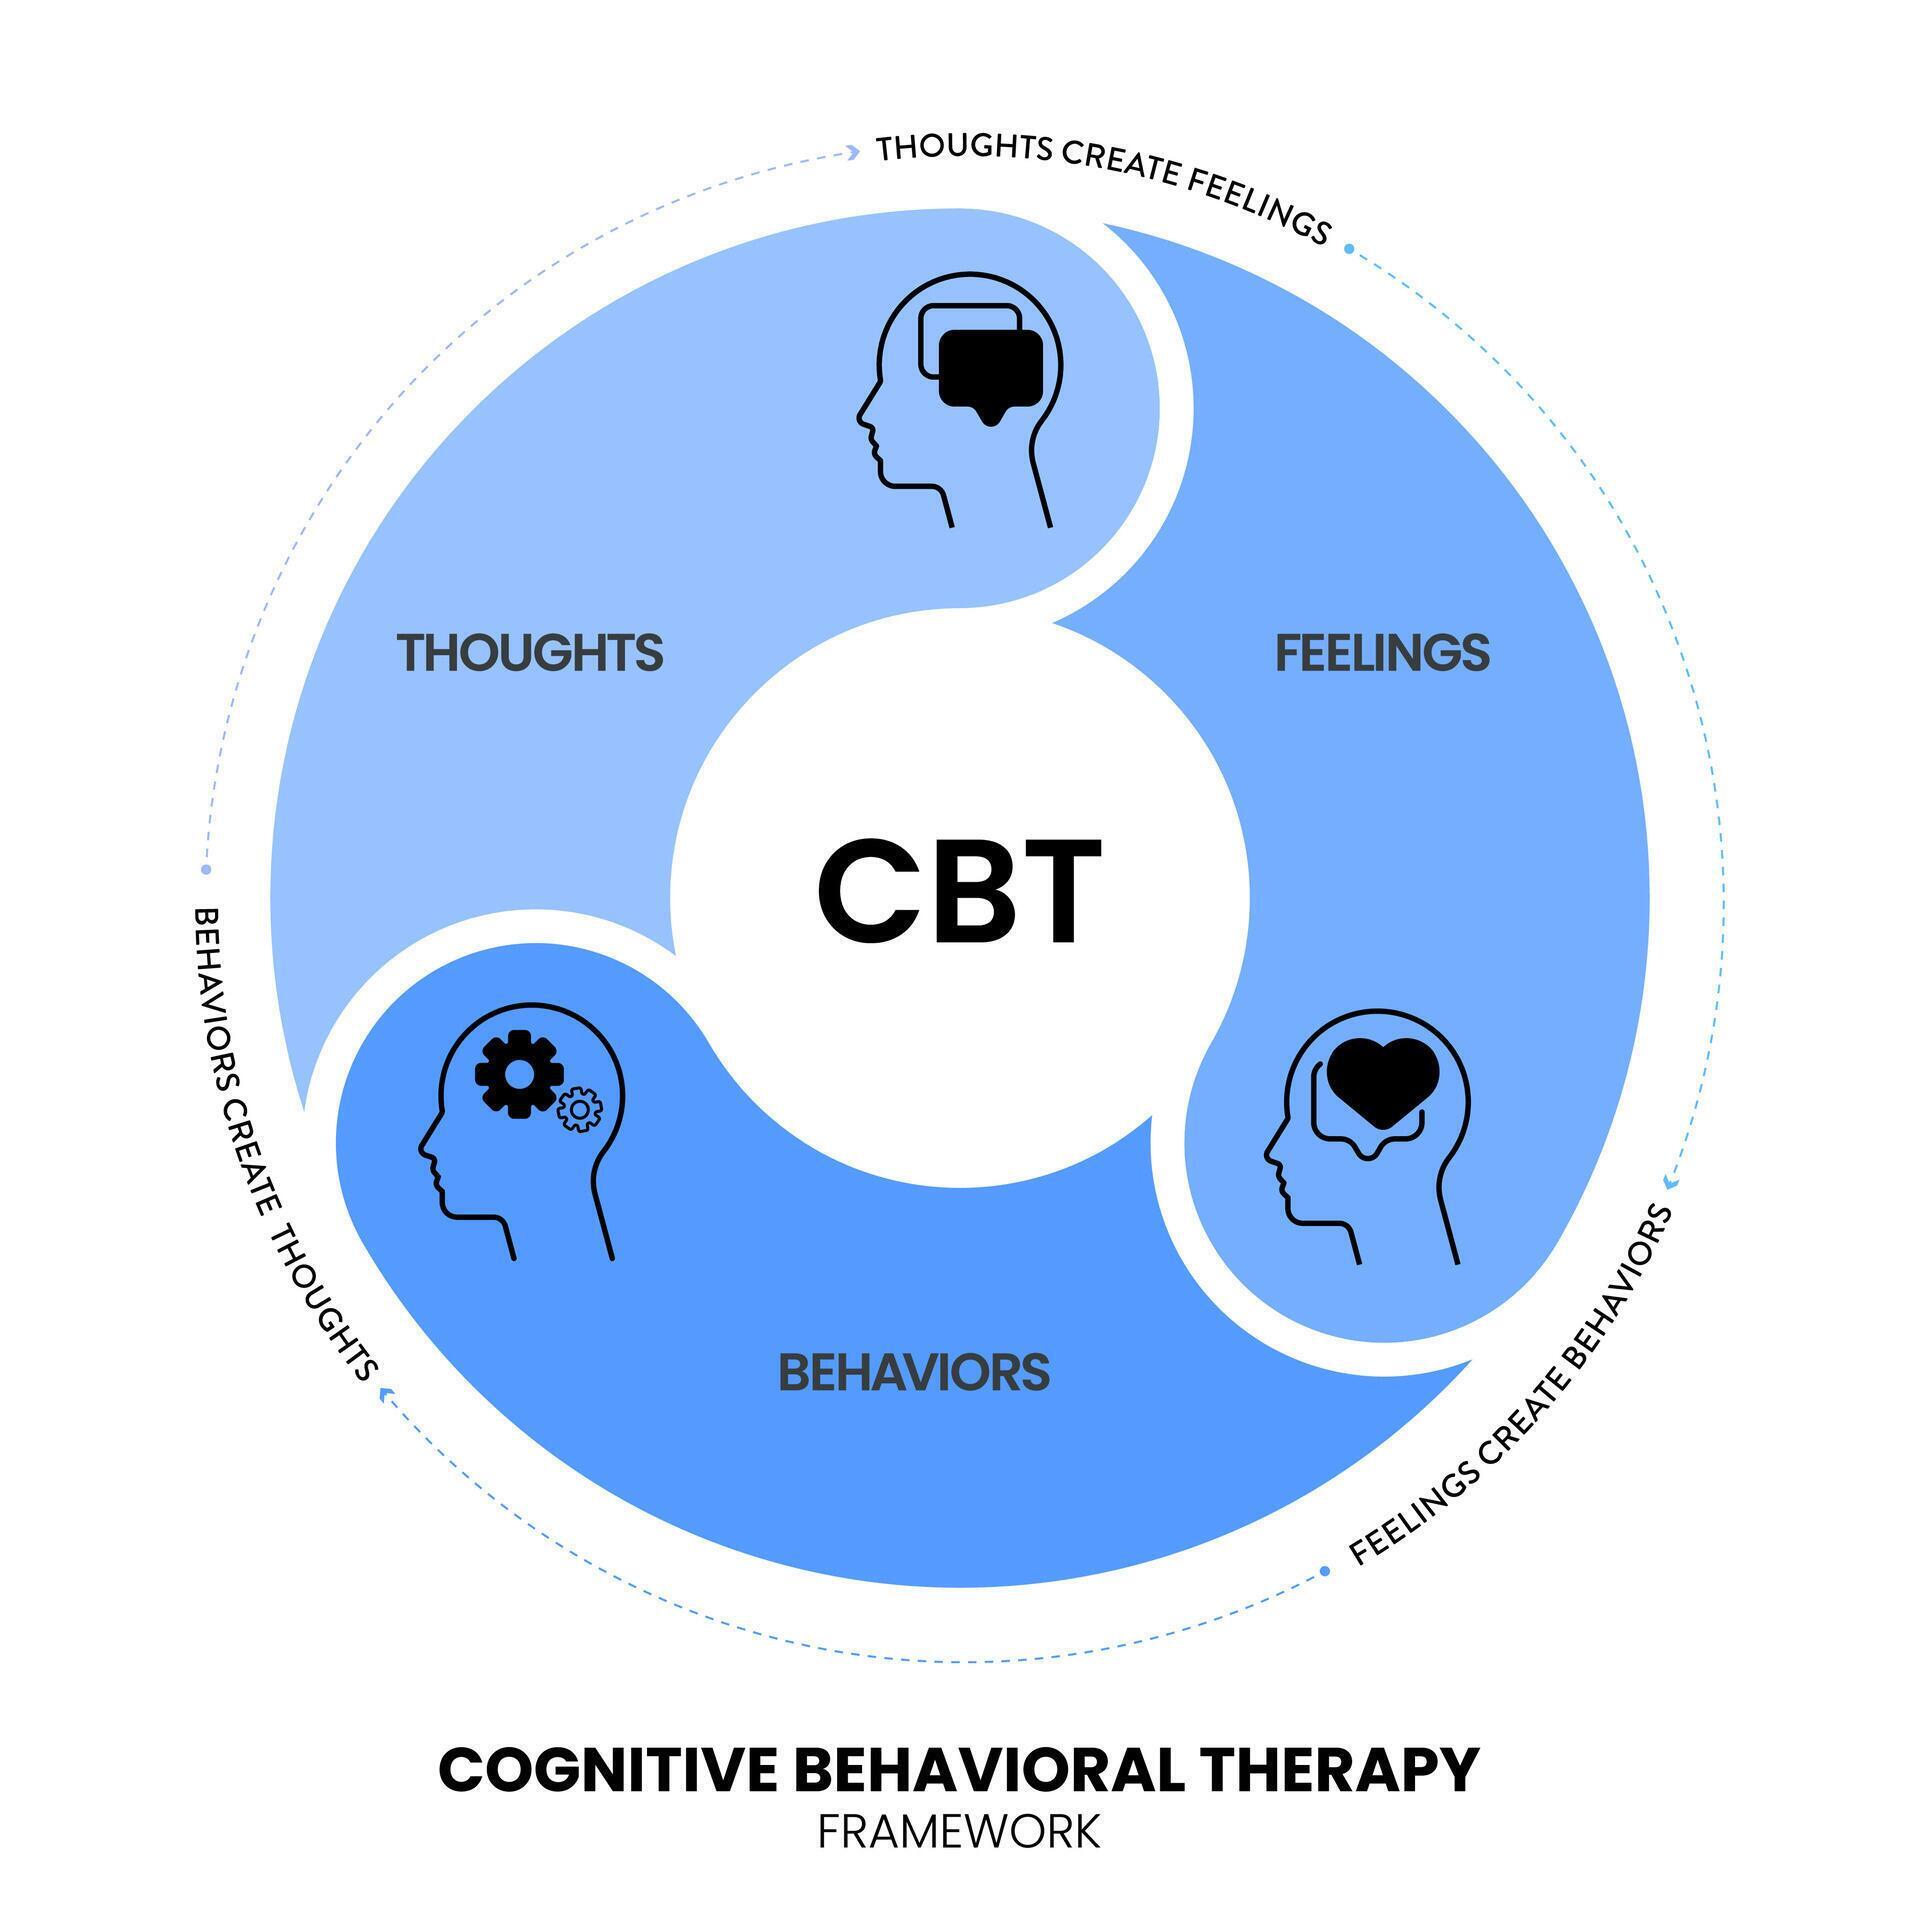
The foundation starts with the conceptualization model. Trainees need to understand how to take a client's reported experience and translate it into a CBT case formulation before they touch a single technique. I see programs teach thought records and behavioral activation as standalone tools, which creates therapists who can administer worksheets but cannot hold a coherent formulation when a client goes off-script. My approach starts with the cognitive model itself — the connection between events, automatic thoughts, emotions, physiological responses, and behaviors. You spend the first six sessions just on case formulation. Six sessions before any intervention. That is not negotiable if you want competent clinicians at the end of your program. From there, the curriculum branches into two tracks that run concurrently rather than sequentially. The cognitive track covers cognitive restructuring, Socratic dialogue, and identifying cognitive distortions. The behavioral track covers behavioral activation, exposure hierarchies, and skills training. Splitting them sequentially like most programs do creates therapists who are either all cognition or all behavior, and both camps are incomplete.
One specific problem I ran into during development was the handling of resistance. Every textbook describes resistance as something the therapist overcomes, but in practice, resistance is usually a signal that the formulation is wrong or the therapeutic alliance needs repair. I redesigned the supervision module around that exact premise. Instead of teaching override techniques, trainees now practice reading resistance as diagnostic data. I learned this the hard way during a live demo session where a volunteer client shut down during a cognitive restructuring exercise. The trainer in the room immediately pushed harder with Socratic questions, which made things worse. What actually worked was stopping, naming the process out loud, and asking the client what was happening in that moment. The client then revealed they felt the questions were being used to challenge their thinking rather than understand it. That session became a required case study in the curriculum. The advanced modules cover comorbidity and complexity. This is where most programs fail. Depression with anxiety, PTSD with substance use, personality disorder features alongside eating disorders — these are the cases real therapists face, not the pure GAD or MDD vignettes you see in training materials. My curriculum dedicates an entire unit to comorbid presentations and how to adjust the case formulation when multiple diagnoses interact. A common mistake is treating each diagnosis separately, which doubles the homework load and confuses the client. Session structure is another area that gets glossed over. A standard CBT session has a predictable rhythm: check-in on mood and homework, agenda setting, review of previous homework, focus on the agenda item, assignment of new homework, and feedback. Trainees need to practice this structure until it is automatic. I built in recording and transcription exercises where students submit actual sessions (anonymized) and we go through them line by line. This is uncomfortable but effective. You learn to notice when you forgot to assign homework or when you spent twenty minutes on history taking instead of the present problem.
Get the Full Details
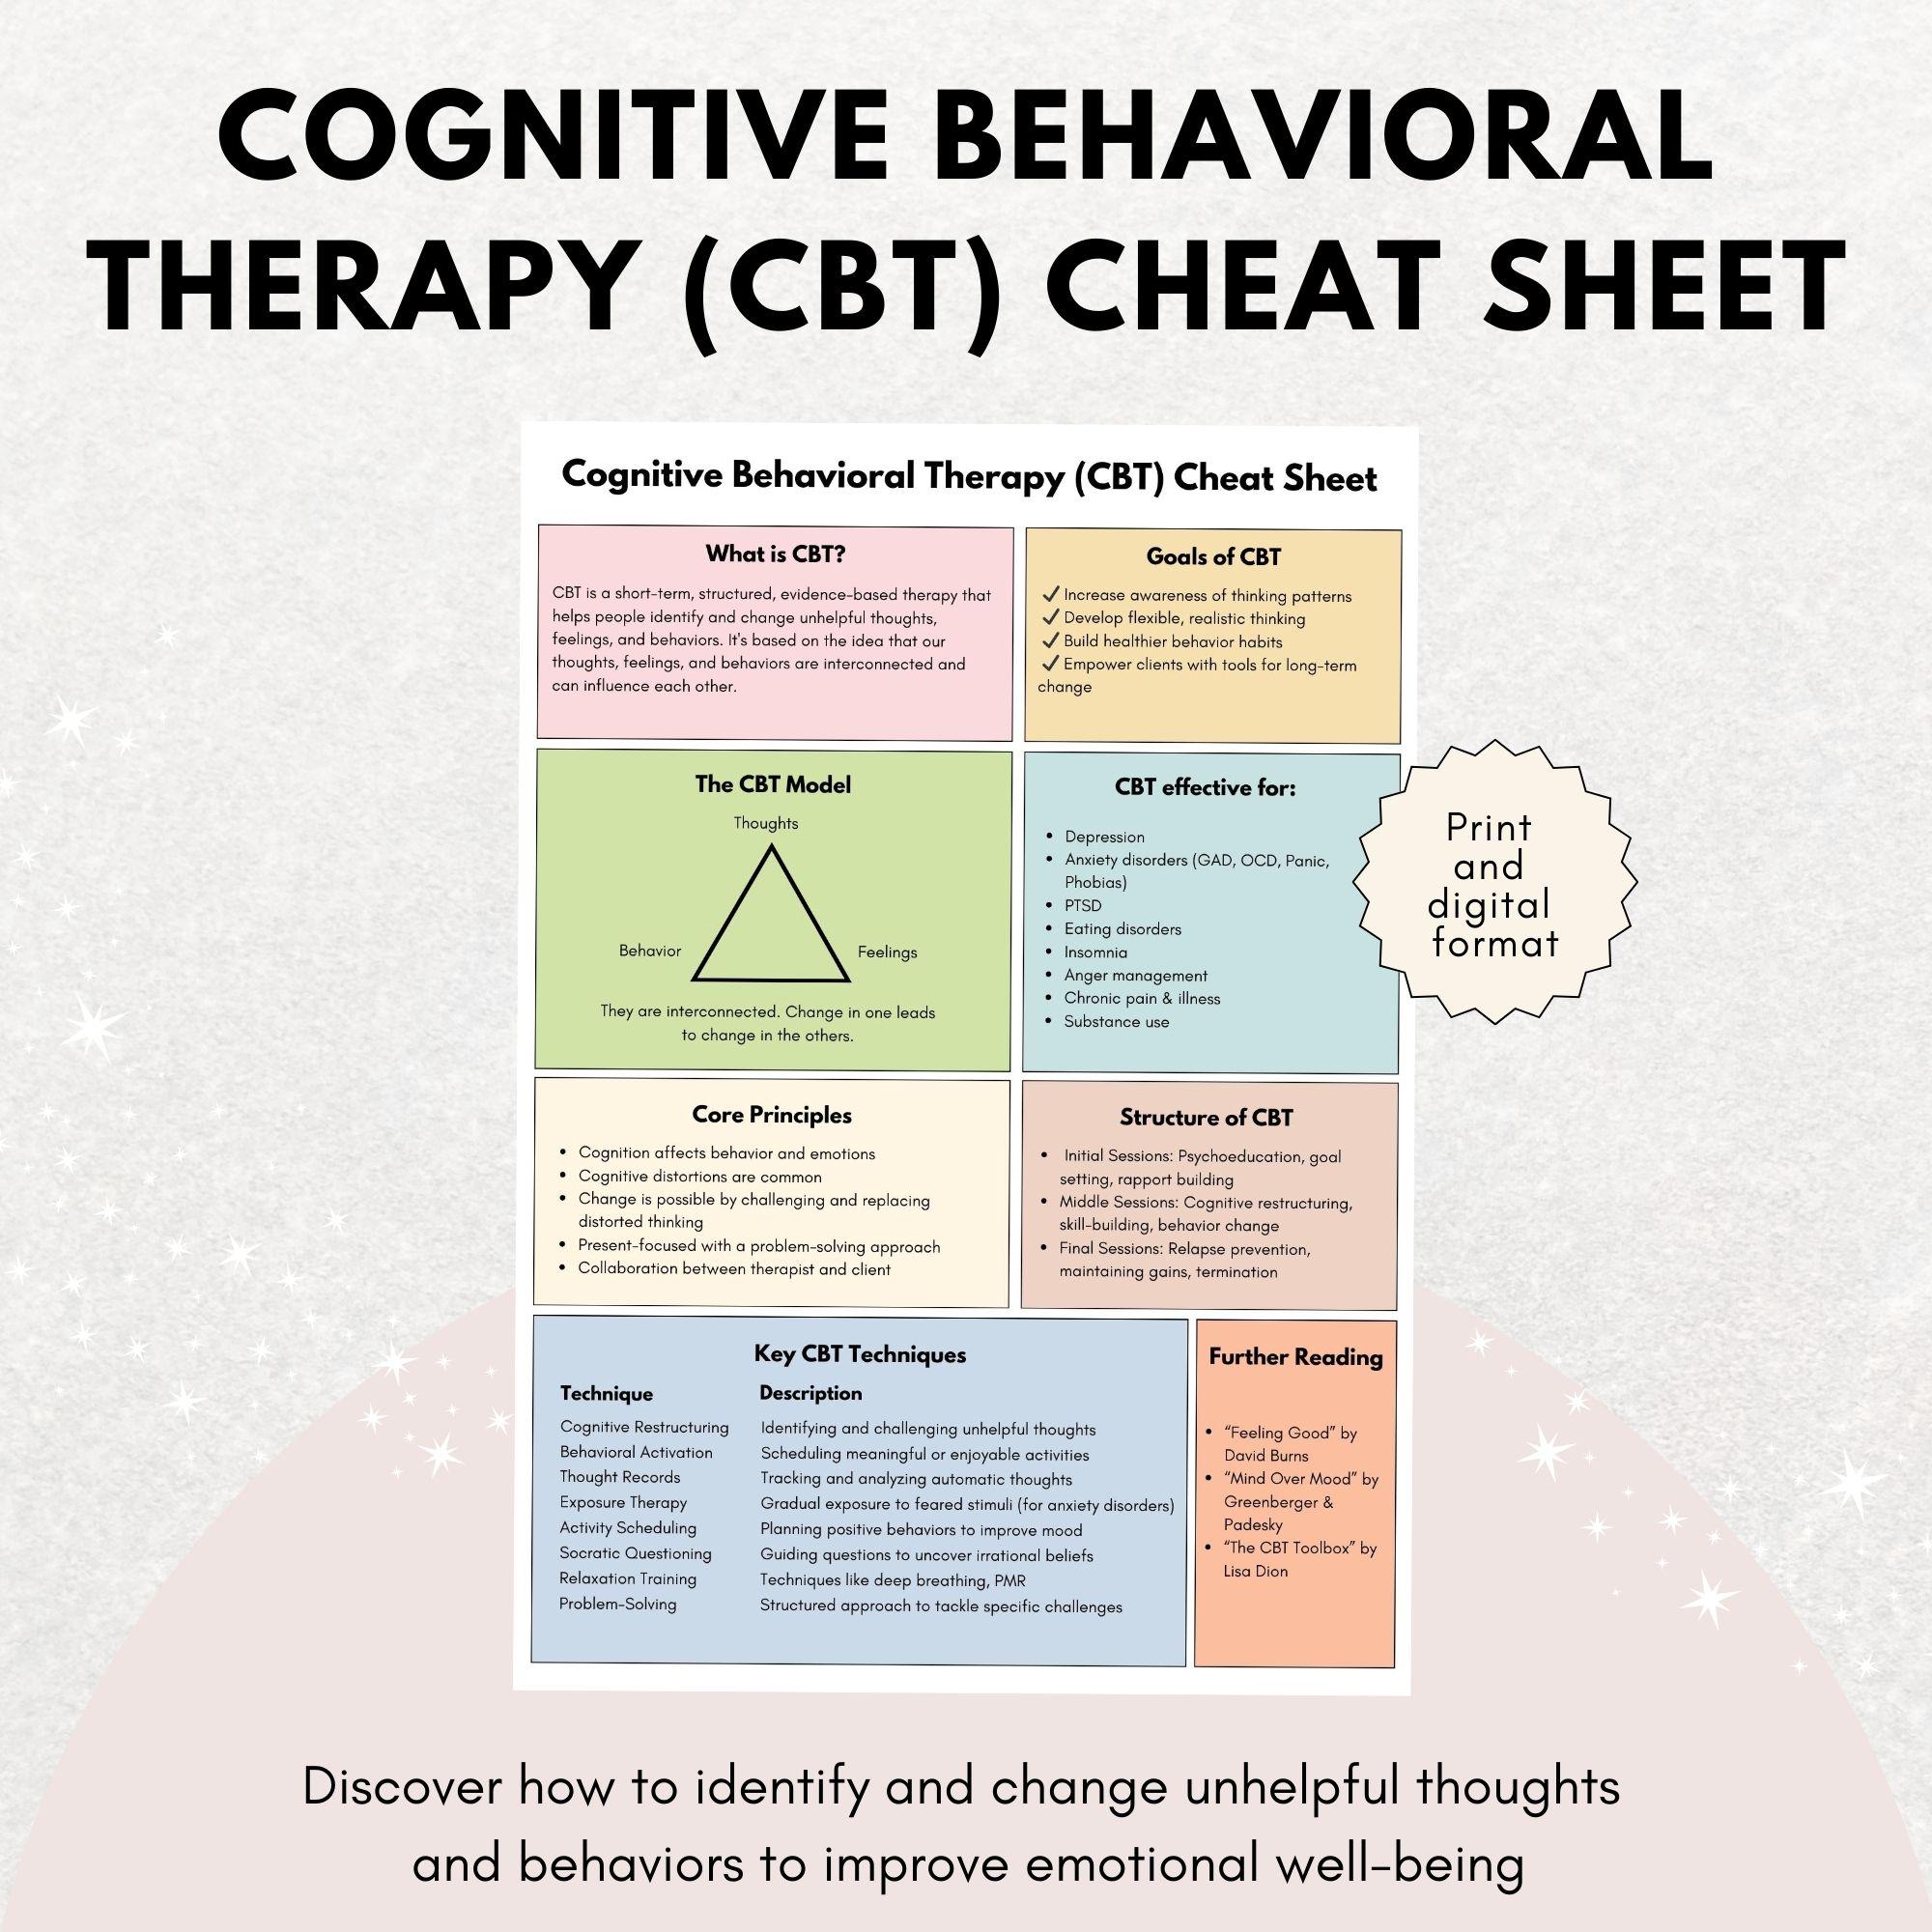
The homework component deserves its own emphasis. Homework compliance in CBT is one of the strongest predictors of outcome. If your curriculum does not include a dedicated module on how to design, negotiate, and troubleshoot homework, you are leaving effectiveness on the table. I cover specific strategies like behavioral experiments that double as homework, using implementation intentions ("If X happens, then I will do Y"), and troubleshooting barriers before they become non-compliance. There are limitations to this model that the literature acknowledges but training programs rarely emphasize enough. CBT requires a certain level of cognitive functioning and verbal ability. Clients with significant intellectual disabilities, acute psychosis, or severe personality disorganization often do not benefit from standard CBT formats. The curriculum should address this honestly rather than pretending the model is universal. For those populations, structured supportive therapy or dialectical behavior therapy modules are more appropriate first-line approaches. Another honest bottleneck is the time commitment. A thorough CBT training curriculum, the way I structured it, takes approximately forty to fifty contact hours plus supervised practicum. Anything shorter produces technicians, not clinicians. I have seen condensed versions marketed as complete programs, and the difference in graduate competence is measurable.
For organizations looking to adopt or adapt this curriculum, the core materials I developed include session-by-session lesson plans, case formulation templates, homework handouts organized by disorder, supervision guidelines, and competency assessment rubrics. These are available through the Association for Behavioral and Cognitive Therapies member portal and through the National Institute for Healthcare Management education catalog. The full package costs roughly eight hundred dollars for institutional licensing. If you are building your own curriculum from scratch, start with the case formulation module and build outward. Everything else depends on that skill. Without it, your trainees will be applying techniques to the wrong problems, which is worse than not applying any techniques at all.



