Understanding What Actually Goes Wrong With IV Therapy
IV therapy is one of the most common procedures in any clinical setting, and it's also one of the most casually performed. That's partly why complications happen so frequently. Most people think about IVs as simple sticks and drips. The reality is that anything introducing fluid or medication directly into the venous system carries a non-trivial risk profile, and the spectrum of Complications Of Iv Therapy ranges from mild nuisance issues to life-threatening emergencies. I've spent years watching this process go smoothly and watching it go badly, sometimes within the same shift. The difference usually isn't dramatic negligence. It's a series of small, invisible compromises that add up. Here's what you need to know, not from a textbook summary, but from what actually happens on the floor.
Complications Of Iv Therapy
Phlebitis And Infiltration: The Everyday Problems
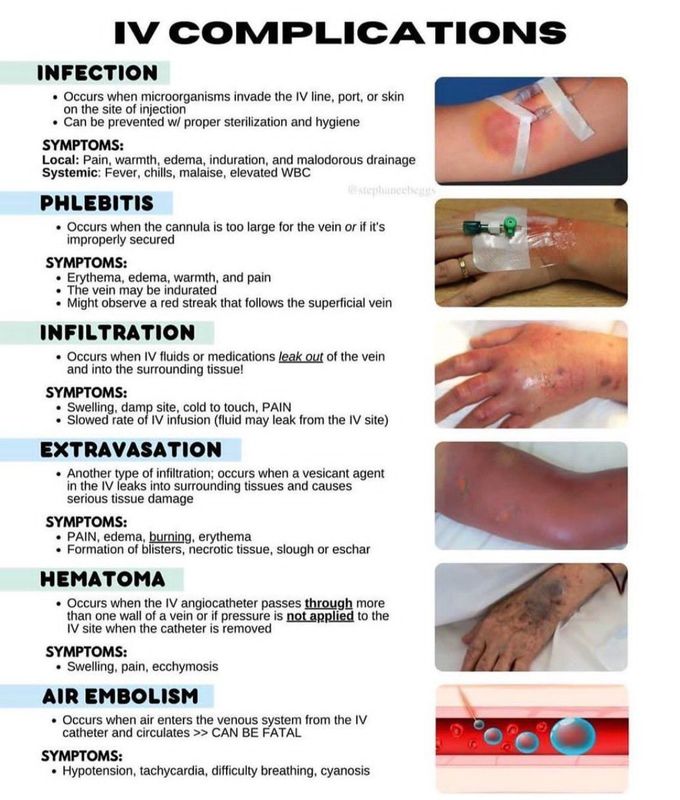
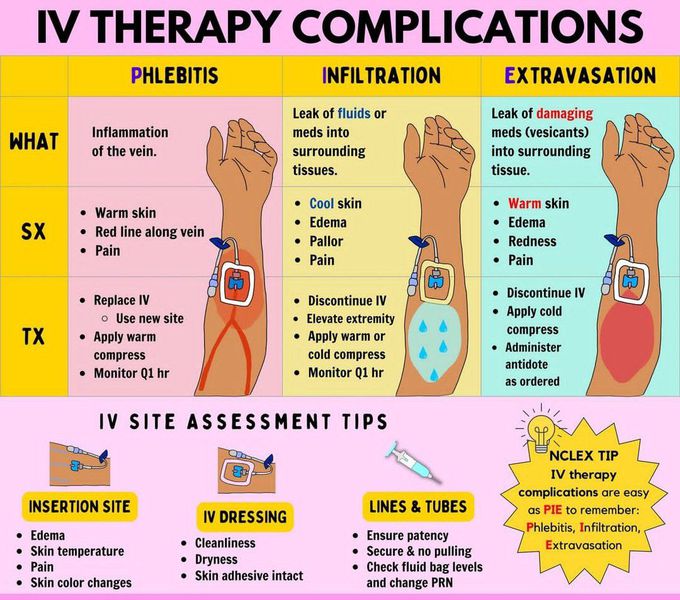
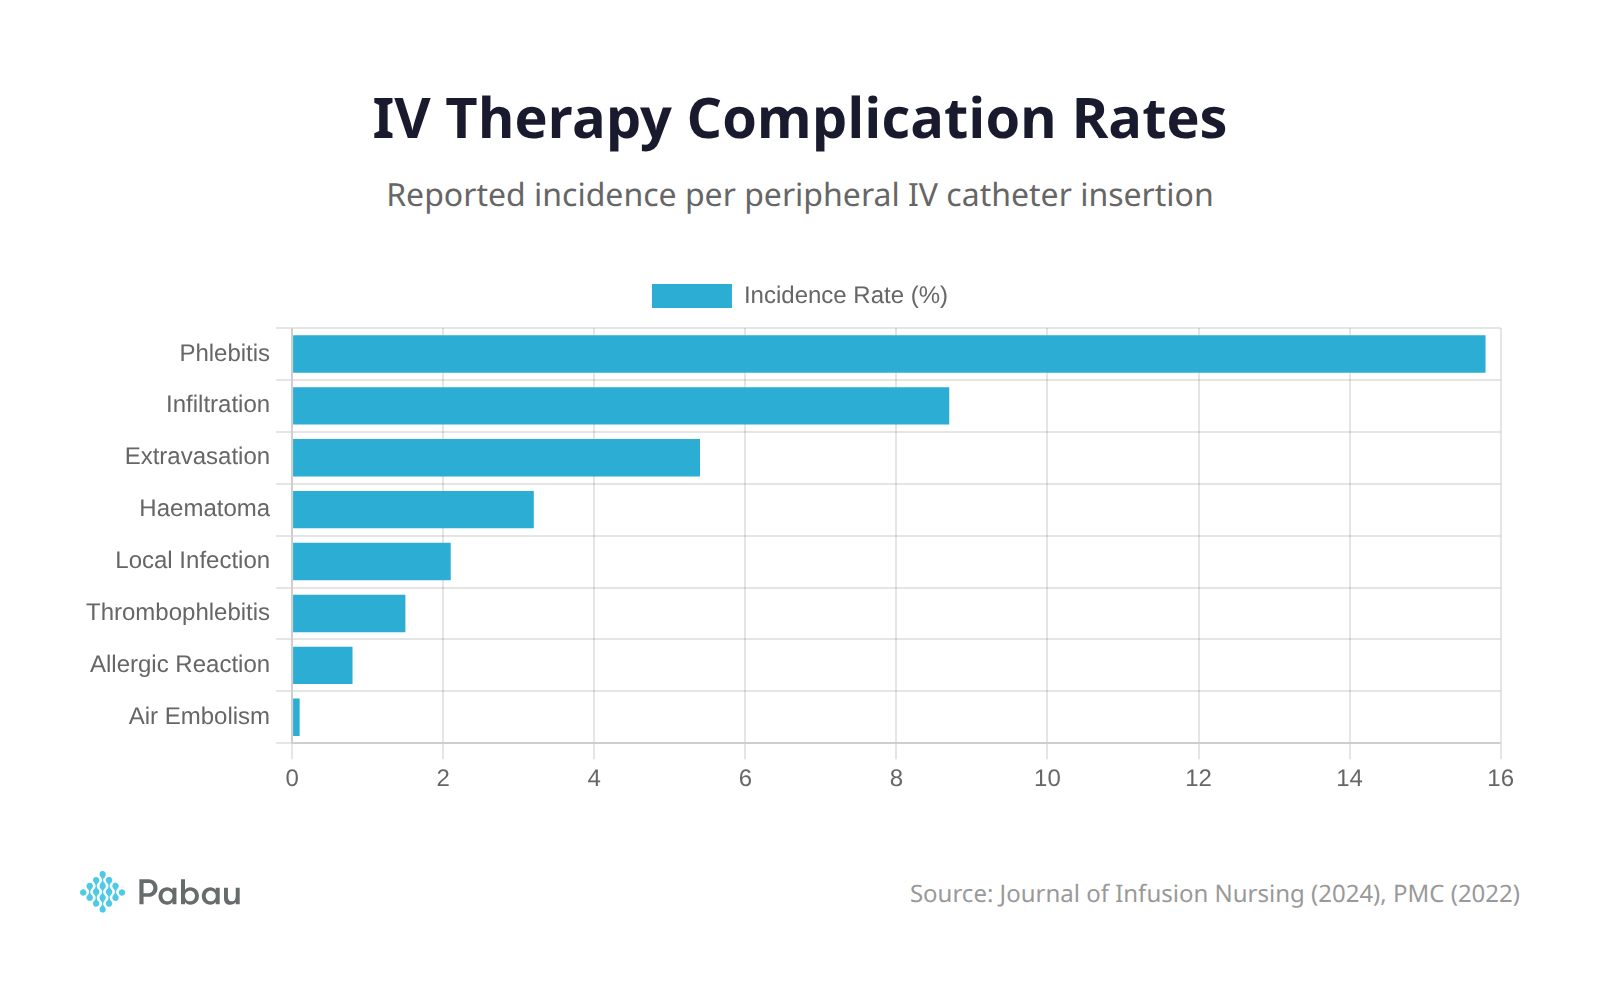
Phlebitis and infiltration are the most common complications by far, and they're often dismissed because they rarely make headlines. Phlebitis is inflammation of the vein wall. It presents as pain, warmth, redness, and sometimes a palpable cord along the vein tract. Infiltration is when the catheter migrates out of the vein or the vein wall is compromised, and infusate flows into the surrounding tissue instead. The counter-intuitive part most people miss: infiltration isn't always obvious. A patient can have significant tissue swelling and minimal complaints if the infusate is isotonic and low-volume. I once missed a Grade 2 infiltration on an older patient receiving normal saline at 100 mL/hr for six hours because the IV site looked fine and the patient said it felt okay. The arm was actually significantly swollen when I finally assessed it properly. The workaround I use now is a routine perivenous skin assessment at least every two hours, comparing circumference and temperature bilaterally rather than just looking at the insertion site. Phlebitis incidence varies dramatically depending on catheter gauge, insertion site, and infusion solution pH. A study in the Journal of Infusion Nursing showed phlebitis rates climbing from under 5 percent with a 22-gauge peripheral catheter in the forearm to over 20 percent with a 20-gauge in the antecubital fossa, especially when irritating medications are involved. Solution pH matters more than most clinicians account for. A pH below 5 or above 9 creates osmotic and chemical irritation that damages the endothelial lining directly. This is why vesicant drugs like vancomycin and certain chemotherapy agents require central venous access even for short courses.
Extravasation: Where Things Get Serious Fast
Extravasation occurs when a vesicant or irritant solution leaks into surrounding tissue outside the vein. This is the complication that keeps nurses and physicians up at night. Tissue damage can progress from mild erythema to full-thickness necrosis within hours depending on the agent involved. Doxorubicin is the classic example. Even a small extravasation of this drug can cause severe tissue necrosis requiring surgical debridement. The initial presentation might seem minor — slight burning, minimal swelling. But the tissue damage is already underway at the cellular level. I've seen cases where the extravasation site appeared manageable on admission and progressed to require grafting within 48 hours because the initial assessment underestimated the volume that had leaked. The practical approach involves immediate cessation of infusion, leaving the catheter in place to attempt aspiration of residual drug, and applying the appropriate antidote protocol. For anthracyclines, hyaluronidase injection into the extravasation site can help disperse the drug. For vinca alkaloids, cold compresses are indicated rather than heat, which would increase drug absorption into surrounding tissue. The wrong first response to an extravasation event can worsen outcomes significantly.
Get the Full Details

Air Embolism And Septic Complications
Air embolism is rare but catastrophic. It typically occurs during catheter insertion, removal, or connection/disconnection when air enters the venous system. The risk is highest with central venous catheters, particularly when the patient is in a sitting or semi-upright position. Air volumes as small as 0.5 mL/kg body weight can cause hemodynamic compromise. The signs are variable and can appear delayed. Patients may report sudden dyspnea, chest pain, coughing, or anxiety. A mill wheel murmur on cardiac auscultation is the classic finding but is actually uncommon. More typical presentations include tachycardia, hypotension, and decreased oxygen saturation. The immediate intervention is placing the patient in the left lateral decubitus position with Trendelenburg tilt, which traps air in the right atrium and prevents it from entering the pulmonary outflow tract. Administering 100 percent oxygen supports gas exchange while the body gradually resorbs the air embolus. Septic complications from IV therapy fall into two categories: bloodstream infections and local site infections. Central line-associated bloodstream infections (CLABSIs) are a major concern in hospital settings. The CDC estimates that CLABSIs occur in approximately 7 to 12 percent of patients with central venous catheters, with mortality rates approaching 25 percent in some studies. Peripheral IV site infections are more common but far less dangerous, usually presenting as localized cellulitis rather than systemic sepsis.
What most people don't consider is that the hub connection point is often more contaminated than the insertion site. Every time you needleless connector is accessed, there's a risk of introducing pathogens. I implemented a strict alcohol scrubbing protocol with 70 percent isopropyl alcohol for a minimum of five seconds before every access, and my unit saw a measurable drop in bloodstream infection rates over six months. It's a small habit that makes a real difference.
Fluid Overload And Electrolyte Disturbances
Complications aren't always about the catheter itself. Sometimes the problem is the fluid or medication being delivered. Fluid overload is a particular risk in patients with compromised cardiac or renal function. Even relatively modest volumes — one to two liters over 24 hours — can precipitate acute heart failure in susceptible patients. The insidious nature of fluid overload is that early signs like mild edema or slight weight gain are often overlooked in busy clinical environments. I remember managing a patient who received 3 liters of normal saline over 48 hours for hydration. On paper, this was a reasonable order. The patient developed overt pulmonary edema by hour 44 with oxygen saturation dropping to 88 percent on room air. The lesson wasn't that the fluids were wrong in isolation. The lesson was that the order didn't account for the patient's underlying renal impairment and baseline cardiac dysfunction. Rate limitation and frequent reassessment are non-negotiable in this scenario. Electrolyte disturbances from IV therapy are another area where mistakes are easy to make. Rapid correction of hyponatremia can cause osmotic demyelination syndrome, a condition with devastating neurological consequences. The safe correction rate for chronic hyponatremia is generally no more than 8 to 10 mEq/L in any 24-hour period. Potassium replacement through peripheral veins requires careful attention to concentration and rate. Solutions above 10 mEq/L in a peripheral line cause significant pain and can damage the vein. I've seen nurses try to run potassium at 20 mEq/hr through a 22-gauge forearm IV and then express surprise when the patient complained about burning and the site became phlebitic.

Thrombosis And Deep Vein Thrombosis Risk
IV catheters, particularly central lines and PICC lines, increase the risk of venous thrombosis. The catheter acts as a foreign body within the vessel, triggering the coagulation cascade and potentially leading to deep vein thrombosis. Upper extremity DVTs associated with PICC lines occur in approximately 5 to 15 percent of long-term users. The symptoms can be subtle: arm swelling, heaviness, discoloration, and dilated superficial veins on the affected side. What surprised me early in my career was how often these thromboses go undiagnosed because clinicians don't think to look for them. A patient with a PICC line complaining of arm discomfort is routinely told it's just the IV. A Doppler ultrasound in that situation would have revealed a significant thrombus much earlier. I now maintain a higher index of suspicion for any upper extremity swelling or discoloration in patients with indwelling catheters, regardless of how minor the complaint seems.
Prevention Strategies That Actually Work
Prevention is where most of the actual work happens in IV therapy. The evidence-based strategies with the strongest support include using the smallest gauge catheter appropriate for the therapy, selecting the optimal insertion site, employing maximal sterile barrier precautions for central line insertion, and implementing standardized insertion and maintenance protocols. Site selection matters more than most protocols emphasize. The antecubital fossa, while easy to access, has higher complication rates due to joint movement and larger vein size that doesn't always match the catheter diameter well. The forearm is increasingly recommended as the preferred peripheral site, with studies showing significantly lower phlebitis and infiltration rates. I switched my unit's preferred peripheral site from the antecubital to the forearm and saw our phlebitis rates drop by approximately 40 percent within three months. Securement and dressing technique are areas where practice varies wildly and where small improvements can have outsized effects. I've seen dressings fail because the skin wasn't properly prepped with alcohol and allowed to dry completely before application. Moisture under the dressing creates a bridge for bacterial migration and compromises adhesion. Another common failure point is inadequate tape or securement device application around the catheter hub, which allows catheter movement and track contamination.
Regular site assessment should follow a structured protocol rather than relying on impression. The Infusion Nurses Society phlebitis scale provides a standardized framework: Grade 1 is minimal symptoms, Grade 2 is pain with erythema and warmth, Grade 3 is pain with streak formation and palpable cord, and Grade 4 is pain with streak formation, palpable cord longer than one inch, and purulent drainage. Using this scale consistently across a unit improves communication and decision-making about when to remove and relocate a catheter.
When To Remove And When To Stay the Course
One of the harder decisions in IV therapy management is knowing when to abandon a difficult site versus when to give it more time. A catheter that's functioning adequately but has mild surrounding erythema might be salvageable with close monitoring. But if there's any sign of progressing phlebitis, infection, or infiltration, prompt removal is the correct action. The risk of leaving a compromised catheter in place far outweighs the inconvenience of re-establishing venous access elsewhere. I've encountered situations where removing a perfectly functional IV in a difficult stick patient felt wasteful. The alternative was attempting peripheral access in a patient with no visible veins, which would have required ultrasound guidance and likely multiple attempts. In those cases, consulting for a midline or PICC placement is more appropriate than leaving a marginal peripheral IV in place for days. The temporary convenience of using an existing site doesn't justify extending the dwell time of a compromised catheter.
Special Populations And Edge Cases
Certain populations present unique challenges. Pediatric patients often require specialized catheters and techniques, and their smaller blood volume means fluid overload can develop rapidly with relatively small excess volumes. Geriatric patients have more fragile veins that are prone to blowing or rolling during insertion, and their often-reduced oncotic pressure makes them more susceptible to infiltration complications. Obese patients present technical difficulties with site visibility and palpation, sometimes making ultrasound-guided insertion the standard approach rather than an exception. Patients receiving long-term parenteral nutrition through peripheral access are at particularly high risk for phlebitis and thrombosis due to the hypertonicity of the solution. Dextrose concentrations above 10 percent and osmolarities above 900 mOsm/L are generally considered unsuitable for peripheral administration. I worked with a patient who was maintained on peripheral TPN for several weeks and developed sequential phlebitis in multiple sites over that period. The eventual switch to a central line resolved the issue entirely and allowed for more concentrated nutrition delivery.
The Reality Of IV Therapy Complications
The Complications Of Iv Therapy are rarely the result of a single catastrophic error. They're usually the product of accumulated small risks: a catheter left in slightly too long, a site that was assessed inconsistently, an infusion rate that was slightly too aggressive for the patient's condition. The best practitioners I've worked with share a common trait: they treat every IV with the respect it deserves, not because they're paranoid, but because they understand the mechanics of what's happening inside the vein. The practical takeaway is that vigilance, proper technique, and timely intervention are the three pillars of complication management. Documentation matters too, because tracking site assessments and any changes over time creates a record that can prevent future problems with the same patient and helps communicate concerns to the broader care team. Most complications are preventable with consistent attention to detail, and the ones that do occur are far less severe when they're caught early and managed appropriately.