What EFT Actually Looks Like When You Are Doing It
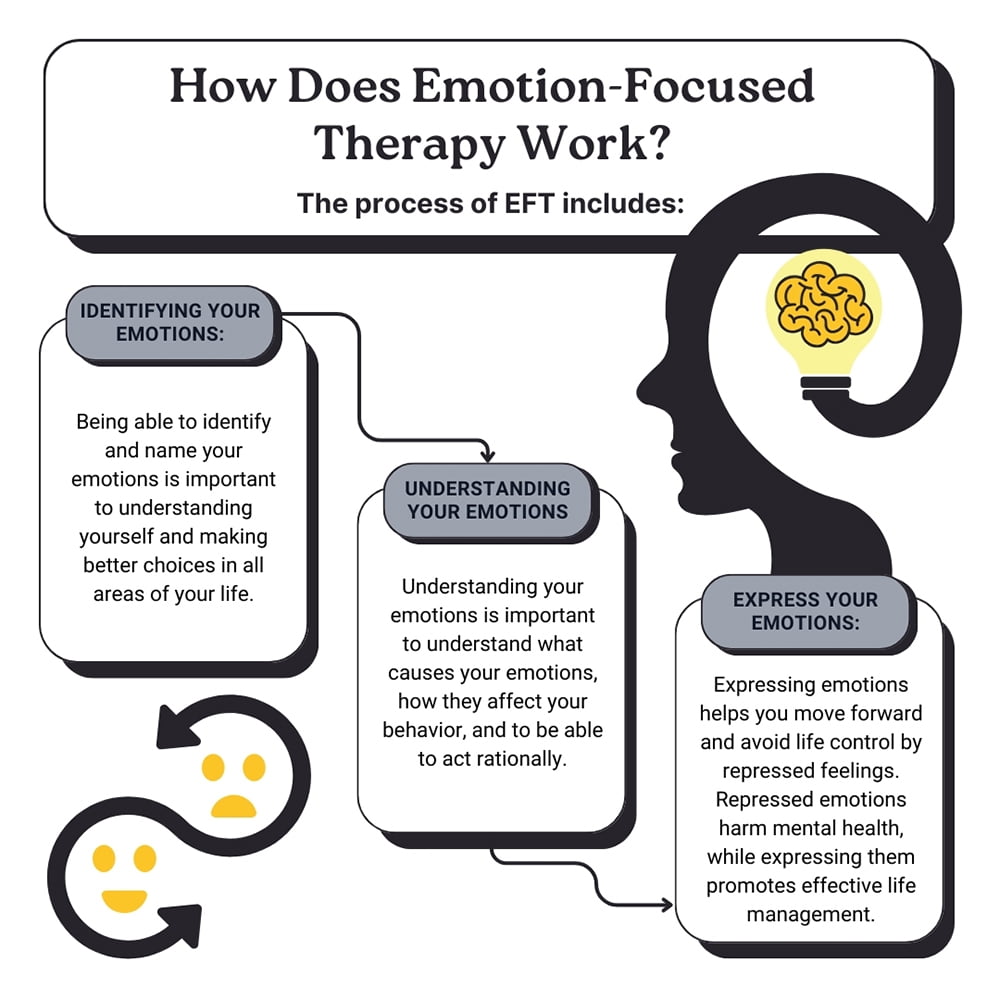
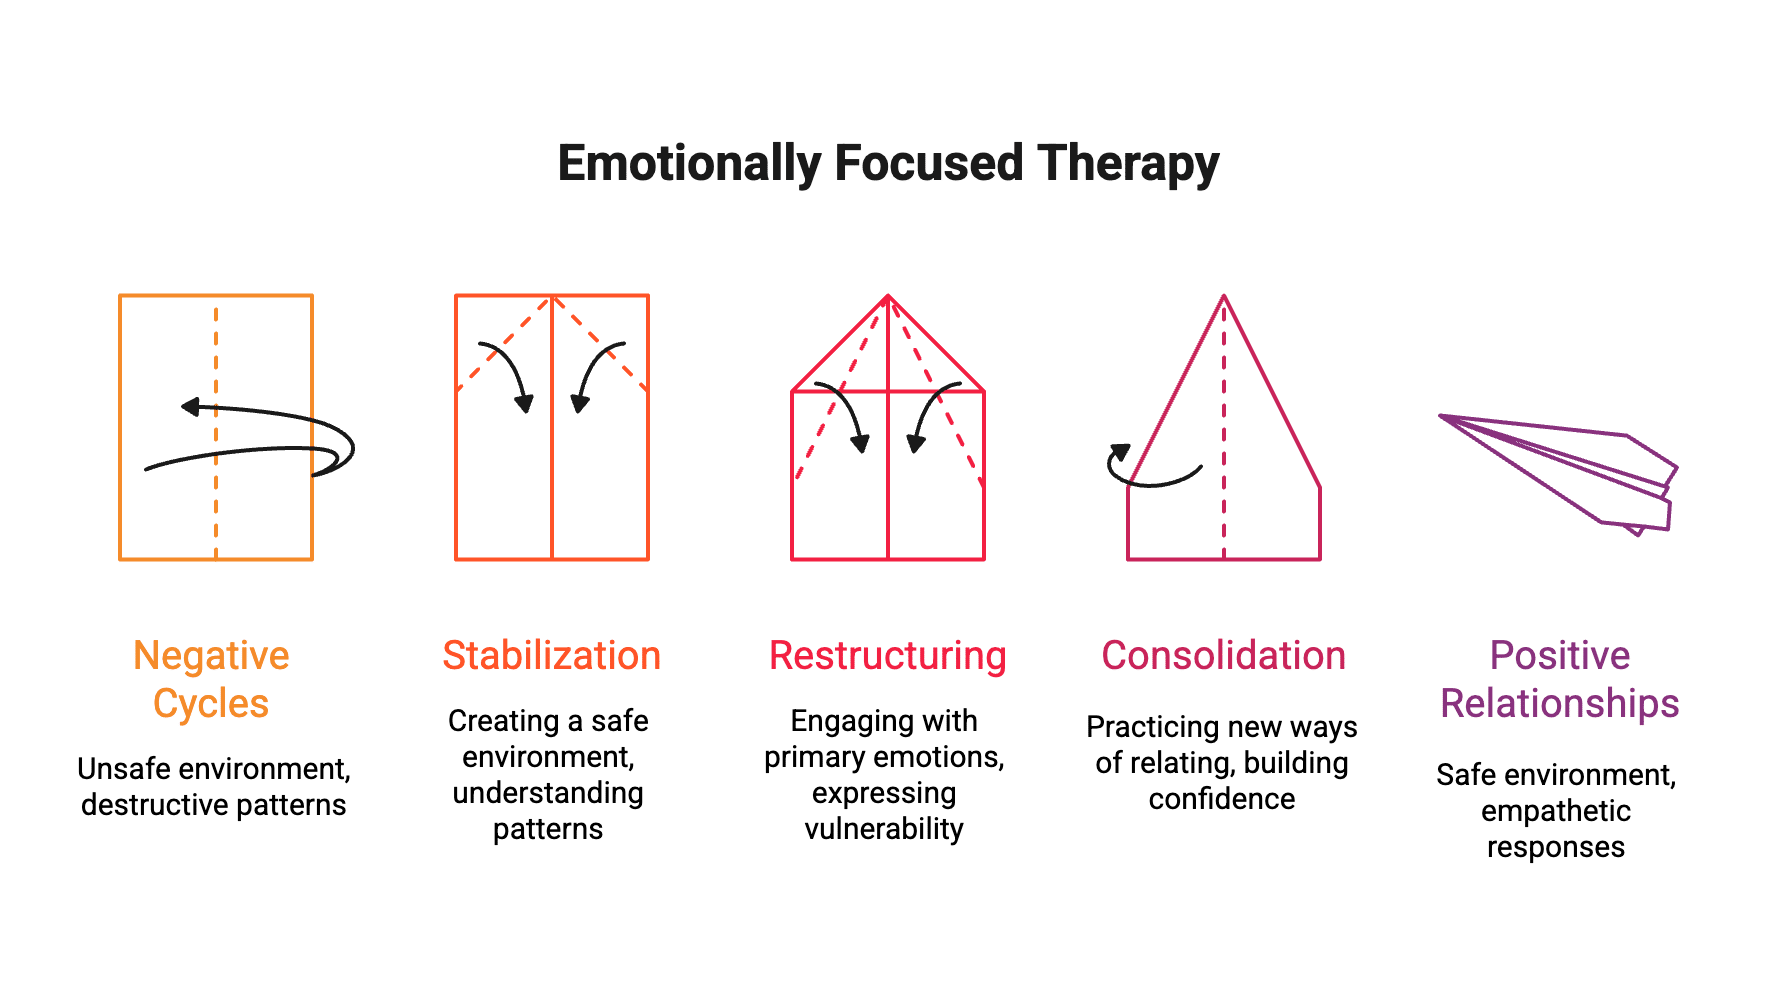
I sat in a supervision session once watching a therapist work with a couple that had been together eleven years and were about to split because they could not stop the same fight every Thursday night. The pattern was so clean it was almost surgical. He would bring up something small, she would go quiet, he would escalate, she would leave the room, and by Sunday they were exhausted and pretending everything was fine. This is the kind of cycle EFT was designed to track and disrupt, and it works until it does not. Emotionally Focused Therapy is built on attachment theory and treats relationship distress as an adaptive response to perceived threats to connection rather than a character flaw or a communication deficit. The therapist listens for the underlying emotions driving the surface arguments, reflects them back, and helps each partner express needs directly instead of attacking or withdrawing. Sessions follow a structured progression through three phases: de-escalation of the negative cycle, identification of attachment fears, and consolidation of new interaction patterns. Most protocols target twelve to twenty sessions for couples presenting with moderate distress.
Criticism Of Emotionally Focused Therapy
The most frequent objection I hear from clinicians who have used it for years is that it can gloss over structural inequalities. When one partner is dealing with financial abuse, substance dependence, or untreated bipolar disorder, asking the other to access vulnerability in the middle of an active crisis often just gives the vulnerable person another tool to be hurt with. I learned this the hard way with a client whose husband had been embezzling from their joint account for two years while the therapy was running. The EFT framework kept pulling her toward emotional engagement, but engagement in that context was exactly what kept her financially trapped. I paused the cycle work, brought in a forensic accountant, and only returned to attachment tasks once the money was secured. That is not a flaw in the model, it is a flaw in applying the model without a safety assessment first. Another persistent critique involves cultural applicability. The direct emotional expression that EFT treats as healing can feel dangerously expose or outright inappropriate for clients raised in traditions where emotional restraint signals strength and family harmony depends on not air‑dirty‑laundry in front of outsiders. I worked with a second‑generation immigrant couple where the wife had grown up in a household that treated overt emotional discussion as a sign of mental instability, and the husband had learned the same from his parents. Asking them to perform attachment‑level vulnerability in session felt to them like being asked to commit social suicide. We adapted the approach by working more with behavior patterns and indirect emotional cues, which produced results in about the same timeframe but felt less violating. The research base is strong for acute distress but thinner for long‑term maintenance. Studies tracking outcomes beyond eighteen months show significant drop‑off, particularly when external stressors like job loss, health crises, or immigration upheaval interrupt the consolidation phase. A 2019 meta‑analysis noted that roughly forty percent of couples who achieve early success relapse into familiar cycles within two years, often because the skills learned in therapy are not transferred to novel situations the couple has never practiced navigating together.
I also find the manualized nature of the approach limiting when clients present with comorbid personality pathology. The standard EFT protocol assumes both partners have a reasonable capacity for emotional regulation and reflective functioning. When one or both have borderline or narcissistic traits, the typical cycle‑identification sequence can be hijacked or weaponized. I stopped trying to force pure EFT with that population and instead integrated DBT skills first, then layered in attachment work once emotion‑regulation capacities improved enough to tolerate the vulnerability that EFT requires. The cost and training burden are also real barriers. Becoming certified in EFT typically requires three to five years of supervised practice, ongoing consultation fees, and investment in continuing education that is rarely reimbursed by insurers. Many clinicians simply cannot afford to enter the model, which creates a supply problem in rural or low‑income areas where access to any qualified therapist is already scarce. If you are considering EFT for yourself or recommending it to someone else, the practical takeaway is that it works best as a targeted intervention for specific relational patterns, not as a universal fix. It excels with couples who are fundamentally connected but stuck in destructive cycles, and it struggles with presentations involving active abuse, severe individual psychopathology, or significant cultural mismatch with its emotional‑expression norms. The work is rigorous, the outcomes are real when the fit is right, and the failures tend to happen when the fit is wrong but nobody notices until after the sixth session.
Get the Full Details