The Practical Reality of Managing Nutrition in Advanced Liver Disease
Most hepatologists will tell you that malnutrition hits patients with cirrhosis long before any dietary intervention becomes a discussion point. I have watched people with decompensated disease lose significant muscle mass over a period of months while their families fed them plain toast and broth because they were told to "eat light." The reality is that the cirrhotic liver demands more calories and more protein than a healthy liver ever would. The metabolic rate is elevated. Muscle wasting is accelerated. Ignoring this accelerates clinical decline faster than almost anything else outside of ongoing alcohol use or uncontrolled variceal bleeding.
Diet For Cirrhosis Of The Liver: What Actually Works In Practice
The foundation is straightforward but not easy to maintain. Daily sodium should stay below two grams, which translates to roughly five grams of table salt. That means no canned soups, no deli meats, no restaurant food unless you are requesting modifications, and no added salt at the table. The liver cannot handle the fluid retention that excess sodium causes, and ascites is the single most frustrating complication for patients and physicians alike.
Protein is where most people go wrong. For decades, doctors restricted protein in patients who showed signs of hepatic encephalopathy because they feared worsening confusion. That approach was based on outdated reasoning. The current guidance from major hepatology societies recommends one point two to one point five grams of protein per kilogram of body weight daily. A seventy-kilogram patient needs roughly eighty-five to one hundred five grams of protein per day. I have seen patients placed on aggressive protein restriction who then developed severe sarcopenia, which directly correlates with worse transplant outcomes and higher mortality. The encephalopathy concern is real, but the solution is not less protein. The solution is adequate protein intake combined with lactulose or rifaximin when necessary, and ensuring the patient is getting enough calories from carbohydrates and fats so the body does not break down its own muscle for fuel.
Meal timing matters more than most patients realize. The cirrhotic liver has impaired glycogen storage. Overnight fasting can trigger catabolism, meaning the body starts consuming muscle tissue while the patient sleeps. A late-evening snack containing complex carbohydrates and some protein—something like Greek yogurt with oats, or cottage cheese with whole grain crackers—can significantly reduce nighttime muscle breakdown. I worked with a patient in her early sixties who had persistent hypoglycemia in the mornings despite eating adequate meals during the day. We added a bedtime snack of peanut butter on whole wheat toast and a small bowl of oatmeal. Her morning glucose readings stabilized within two weeks. The mechanism was simple: the slow-release carbohydrates and protein provided a steady fuel source through the night.
Micronutrient deficiencies are extremely common in cirrhosis. Zinc deficiency affects up to sixty percent of patients with decompensated disease and can worsen encephalopathy and impair taste sensation, which further reduces food intake. Magnesium, selenium, and the fat-soluble vitamins A, D, E, and K are frequently low. Supplementing is necessary, but it requires care. Vitamin A in high doses is hepatotoxic, and the cirrhotic liver is already struggling with vitamin A metabolism. I have seen patients take standard multivitamins that contain ten thousand percent of the daily value of vitamin A and end up with elevated liver enzymes on top of everything else. A targeted supplement regimen under medical supervision is far safer than random over-the-counter products.
Sodium Restriction: The Hardest Part
Getting sodium under two grams per day sounds simple until you actually try to do it. Most processed foods are sodium bombs. A single cup of canned lentils can contain eight hundred milligrams of sodium. Two slices of bread can contain four hundred milligrams. Restaurant meals routinely exceed the entire daily limit in a single sitting. I had a patient who managed to stay under his sodium target for three weeks straight, then went to a family wedding and ate whatever was available. He gained four pounds in two days and his ascites returned with enough severity that he needed a therapeutic paracentesis within a week. The fluid shifts are brutal and unpleasant. Compliance with sodium restriction is not a matter of willpower alone. It requires planning, reading labels, and cooking most meals at home.
When sodium restriction becomes impossible to maintain due to social circumstances or severe taste fatigue from zinc deficiency, some hepatologists will consider a potassium-sparing diuretic adjustment or a temporary sodium-binding intestinal polymer, but these are second-line strategies with their own risks.
Fluid Management and Ascites
Fluid restriction is not routinely recommended unless the patient has hyponatremia, meaning a serum sodium below one hundred twenty-five milliequivalents per liter. If sodium is normal, drinking extra water does not help and may cause harm by diluting electrolytes further. The confusion around this is widespread. Patients are often told to "stay hydrated" without qualification, which can be dangerous in the context of advanced cirrhosis and fluid retention.
Paracentesis remains the most effective treatment for tense ascites that does not respond to sodium restriction and diuretics. However, large-volume paracentesis requires albumin infusion to prevent post-paracentesis circulatory dysfunction. Each liter removed typically requires six to eight grams of albumin administration. This is standard protocol but it adds cost and complexity to care.
Varices and Bleeding Risk
Diet interacts with portal hypertension in ways that are not always obvious. Patients with large esophageal varices should avoid foods with sharp edges or hard textures—crackers, toast points, raw vegetables, chips—that could mechanically injure the variceal tissue. I once treated a patient who developed significant hematemesis after eating dry, crusty bread rolls. The varices had not bled before. The mechanical trauma from the food was the trigger. This is not a common presentation, but it is well documented, and swallowing texture matters more than people assume.
Non-selective beta blockers such as carvedilol or propranolol are the standard prophylactic treatment for variceal bleeding. These medications lower portal pressure but also carry risks of hypotension, fatigue, and GI side effects. Dietary timing around medication can sometimes help with tolerability, though this is a minor consideration compared to the pharmacological effects.
Alcohol and Complete Abstinence
This requires no elaboration, but it bears repeating because patients constantly underestimate its impact. Any amount of alcohol in the setting of established cirrhosis accelerates liver damage, increases the risk of hepatocellular carcinoma, and worsens outcomes across every measurable parameter. Even patients with alcohol-related cirrhosis who have been abstinent for years continue to face elevated risk, and relapse statistics are unfortunately high. Support systems and behavioral interventions matter as much as any dietary modification.
Transplant Evaluation and Nutritional Status
Nutritional status is a formal criterion in liver transplant allocation in many regions. Sarcopenia, measured through CT imaging of the psoas muscle area at the L3 vertebral level, is increasingly used as a prognostic tool. Patients with severe muscle wasting have higher post-transplant complication rates and longer ICU stays. This is why nutritional rehabilitation before transplant listing is taken seriously by transplant teams. It is not theoretical. It directly affects survival outcomes.
I encountered a patient who was listed for transplant with a body mass index that looked normal but whose bioelectrical impedance analysis revealed critical muscle depletion. He appeared well-nourished on the outside. Inside, his muscle mass was dangerously low. We implemented a high-protein oral supplement regimen alongside his regular meals, added resistance exercise when his clinical status allowed, and over six months his muscle mass improved enough to change his transplant risk classification. The process was slow and required constant monitoring, but it made a measurable difference.
What This Approach Cannot Do
Dietary management will not reverse established fibrosis. It will not eliminate varices. It will not cure hepatitis C or autoimmune hepatitis on its own. It will not replace diuretics, paracentesis, beta blockers, or transplant evaluation when those are indicated. Nutrition is supportive care that can slow decline and improve quality of life, but it is not a standalone treatment for decompensated cirrhosis.
Patients with acute-on-chronic liver failure, active infection, or significant GI bleeding need hospital-level care regardless of how well their diet is managed at home. Diet is one component of a broader treatment plan, not the entire plan.
Monitoring and Follow-Up
Regular monitoring should include serum albumin, prealbumin, total protein, electrolytes, zinc, vitamin D, and full liver function panels. Weight tracking weekly provides useful trend data. Muscle strength assessment, even something as simple as grip strength measurement, can track sarcopenia progression between clinic visits. Patients should keep a food diary for at least the first month of any dietary intervention. It reveals patterns that are otherwise invisible, such as the hidden sodium in condiments or the inconsistent protein intake that leads to metabolic swings.
The diet for cirrhosis of the liver is not glamorous. It involves reading every label, cooking at home, accepting that social dining will be difficult, and committing to long-term habit changes. But the alternative—progressive malnutrition, recurrent ascites, accelerated liver failure—is worse by every clinical measure.
Gallery Diet For Cirrhosis Of The Liver
Liver Cirrhosis Diet Help, Chart of Foods for Liver Cirrhosis, Print Yourself, PDF of Foods to ...
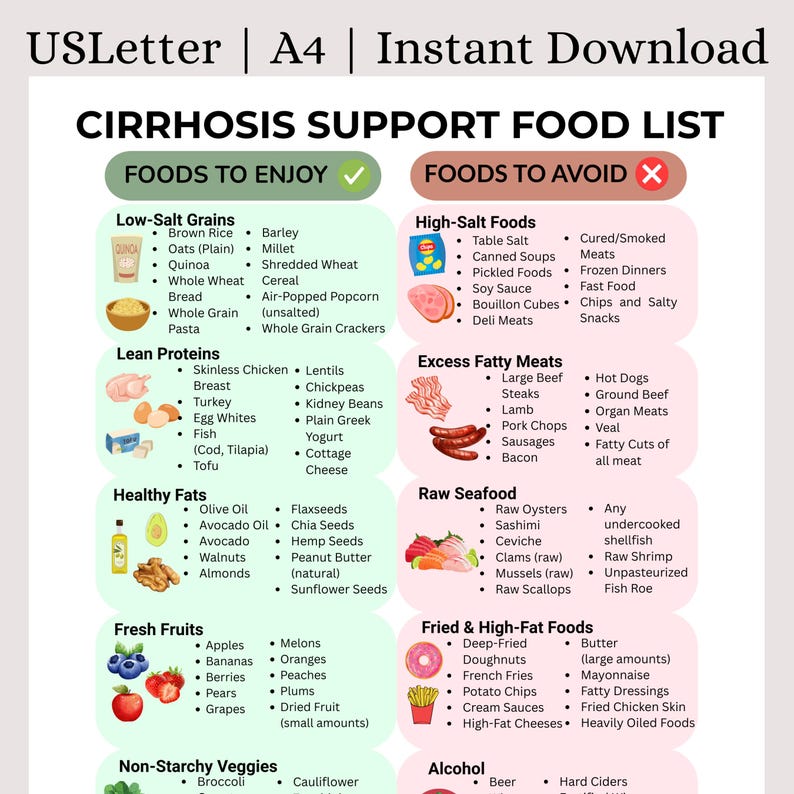
Cirrhosis Food List | Printable PDF for Liver Support | Cirrhosis Diet | Liver Health Guide ...
Liver Cirrhosis Diet List Poster, Liver Disease Diet Chart Poster - Walmart.com
Cirrhosis Diet Food List Printable | Cirrhosis Grocery List | Liver Disease Nutrition Guide ...
Liver Cirrhosis Food List Printable, Low Sodium Grocery Guide, Hepatic Diet Chart, Ascites Meal ...