Reading Simple Squamous Under the Microscope
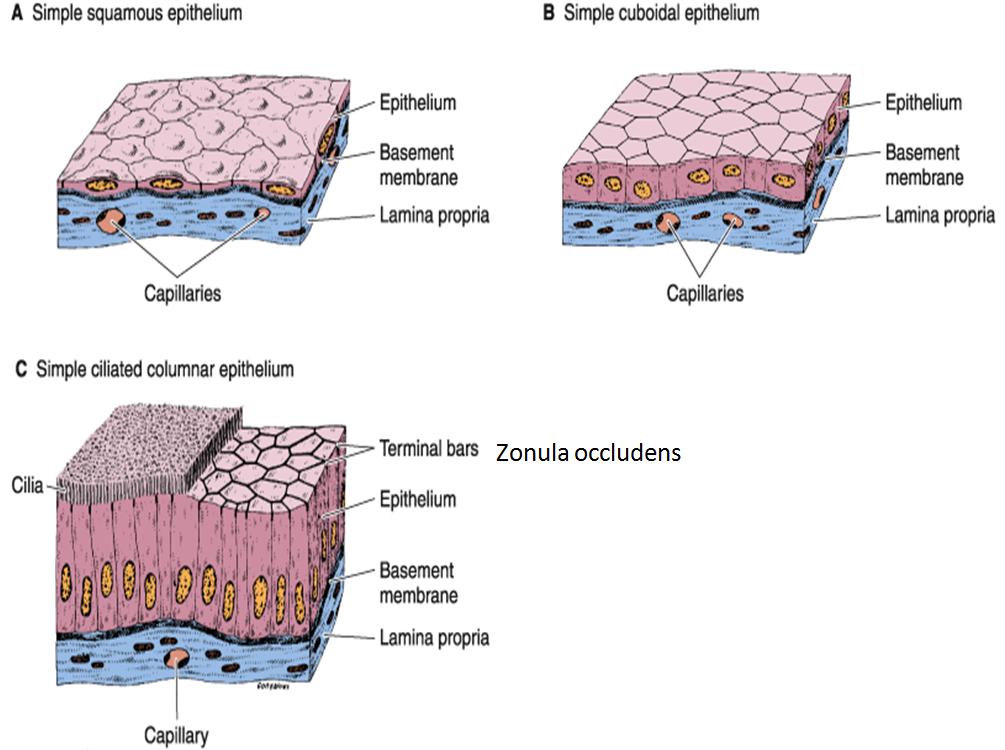
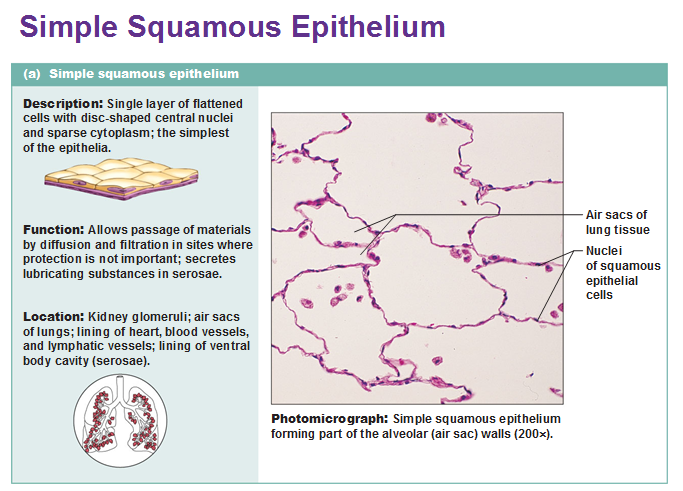
Simple squamous epithelium is the thinnest lining in the body. One layer of flat cells, nuclei bulge slightly into the lumen, and that's basically it. It's found wherever rapid diffusion or filtration matters—capillary endothelium, alveolar walls, the parietal layer of Bowman's capsule, mesothelial linings of body cavities. If you're studying histology, you'll see it everywhere and barely notice it because it's designed to be invisible. The practical problem most people run into isn't identifying the tissue type. It's that simple squamous epithelium is so thin and delicate that routine processing obliterates it. I spent an entire afternoon chasing what I thought was a sectioning artifact before realizing I was looking at actual tissue damage from the microtome blade. The cells literally shear off during cutting because there's almost no cytoplasm to hold them in place. My workaround was switching to a glass knife on the ultramicrotome for anything where I needed intact alveolar or endothelial architecture. Standard paraffin sections on steel blades just don't cooperate well here.
Identifying Epithelial Tissue Simple Squamous in Real Specimens
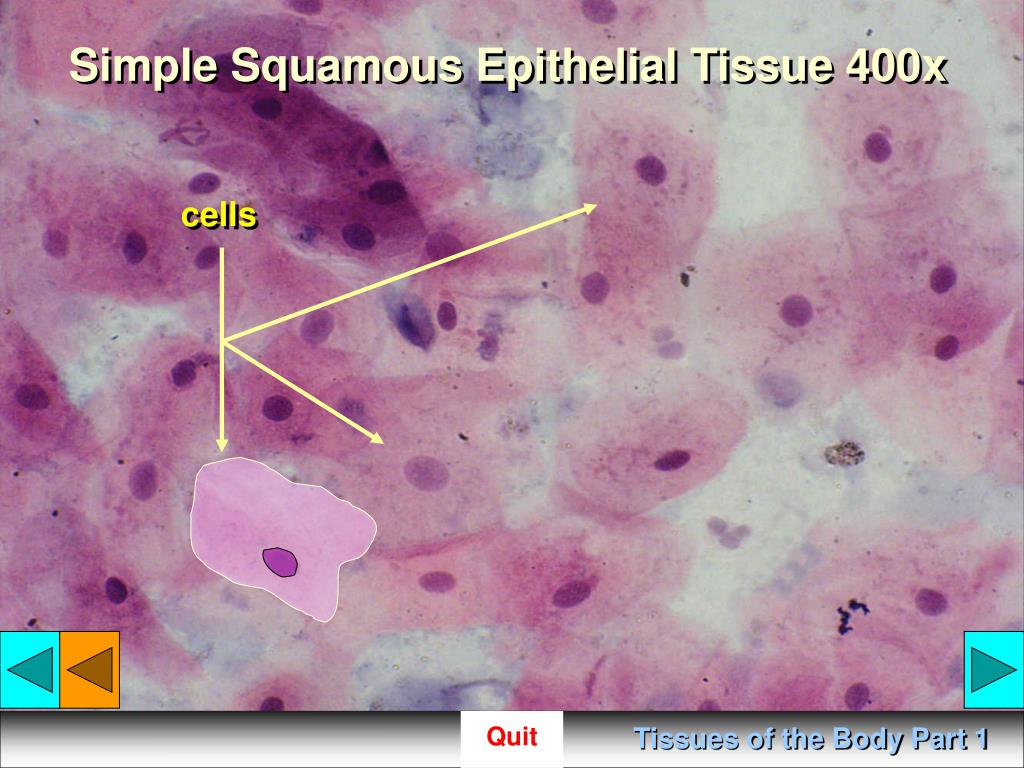
When you first look at a slide labeled "simple squamous," your brain might resist it because it looks like nothing happened. Here's what you actually need to confirm: The nuclei are centrally located, flattened, and occupy roughly the same focal plane. You should be able to trace the basement membrane as a continuous boundary with minimal intervening space. Cytoplasm is nearly undetectable without higher magnification or specific staining. When you find yourself seeing more cytoplasm than you expect, you're probably looking at simple cuboidal, not squamous. Beginners confuse the two constantly, especially in kidney tubules where the proximal convoluted tubule (cuboidal) sits right next to the parietal layer of Bowman's capsule (squamous). Another thing nobody tells you about: staining intensity. Hematoxylin and eosin on simple squamous can look washed out because there's so little cellular material to bind the dye. If your section looks pale and featureless, it might not be a bad stain—it might just be the tissue being exactly what it is. Running a PAS stain or a silver impregnation method like the Jones methenamine silver for glomerular basement membranes adds much more contrast and structural detail.
The endothelial variant presents its own headache. Capillary endothelium is simple squamous, but in dense connective tissue or in organs like the liver, the cells blend into the surrounding matrix. I once spent too long trying to orient a liver section because the sinusoidal endothelium was indistinguishable from the surrounding reticulin framework at 40x. Switching to a reticulin stain ( silver stain) immediately resolved the confusion. The reticular fibers outline the sinusoids cleanly while the endothelial nuclei sit slightly apart from the fiber network. One more edge case that caught me: mesothelium versus simple squamous endothelium. Both are technically simple squamous epithelium. Mesothelium lines the body cavities—pleura, peritoneum, pericardium—and sits on a loose connective tissue base. Endothelium lines blood vessels and sits on a basement membrane adjacent to smooth muscle or connective tissue. Under low magnification they look nearly identical. The differentiator is usually the underlying tissue architecture, which means you need context, not just a higher power view. If you pull a section away from its surrounding landmarks, you're guessing, and guessing is how you mislabel things on exams. The biggest pitfall with this tissue type is overcalling it. In regenerative contexts, after injury to a simple squamous lining, the repair process often involves metaplasia or hyperplasia that temporarily changes the cell shape. A healing alveolus or a recovering glomerular capsule might show cells that look transitional between squamous and cuboidal. Without clinical context or serial sections, you might miscategorize the stage of repair. I've seen this repeatedly in lung biopsy samples where the pathologist called it "simple squamous" without noting the patchy regeneration underneath.
Get the Full Details
If you need a reference for the staining protocols I mentioned, the standard Histotechnology textbook by Culling has the detailed procedures, and the online resources from the University of Michigan Histology site provide free slide atlases with labeled examples. The Key to Histology by Shelton covers identification patterns at a level that's useful for board prep. There isn't a single downloadable toolkit for this—I'm not sure what you'd be downloading anyway—but the protocols are openly available in laboratory manuals and the major histology references cover it thoroughly.