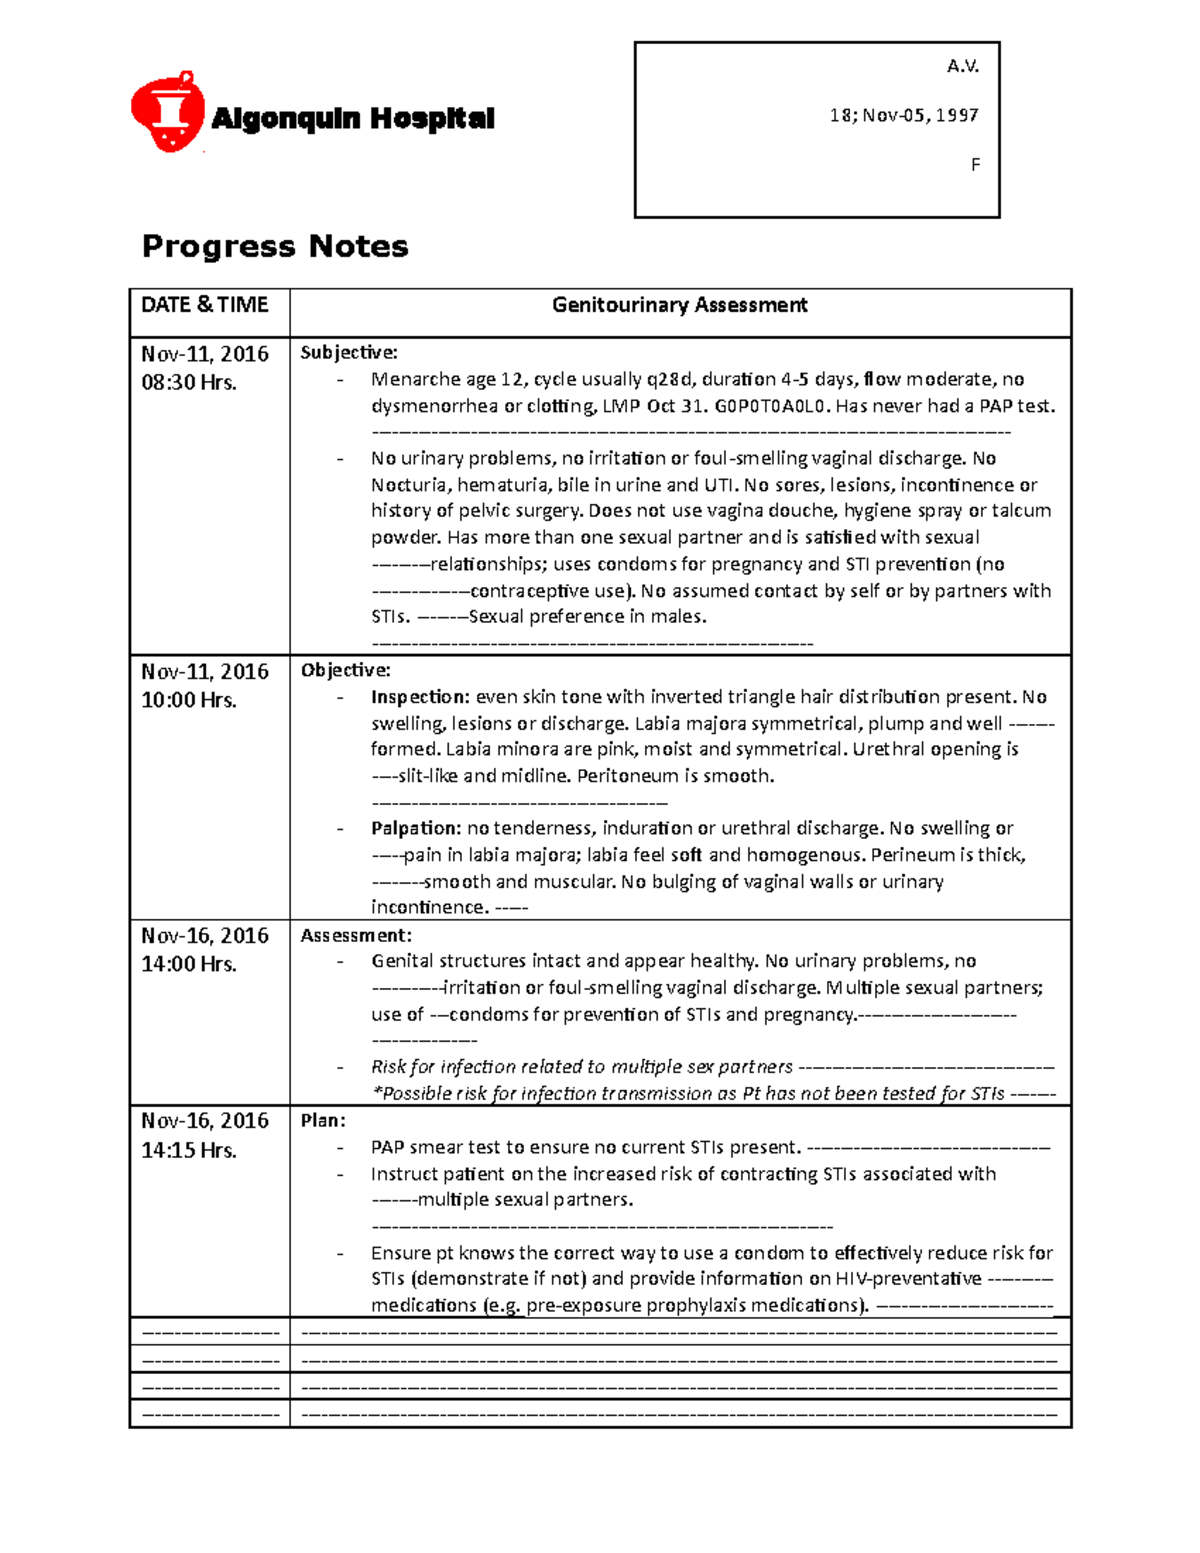
Getting Genitourinary Assessment Nursing Documentation Right
Nursing documentation for genitourinary assessments is one of those areas where most people get it passable but not defensible. When a lawyer or a compliance auditor looks at your chart, they are not looking for perfection. They are looking for consistency, specificity, and a clear timeline. The difference between a defensible record and a weak one usually comes down to three things: what you measured, when you measured it, and what you did about the results. I have spent years reviewing charts and watching new nurses struggle with this section. The problem is rarely that they do not know what to assess. It is that they document in vague generalities. "Urinary output adequate" means nothing to anyone reviewing the chart later. "Foley drainage: 45 mL clear amber urine over the last hour, no sediment, catheter patent with balloon intact at 30 mL" tells a story. That is the standard you are aiming for. Here is the core workflow I use, and what I recommend to anyone doing this type of documentation.
The Assessment Method
Start with inspection and palpation before you touch anything invasive. Document the skin integrity around the perineal area, any existing catheters, ostomy appliances, or suprapubic tubes. Note the type, size, and insertion date of any indwelling devices. If the patient has a urostomy, describe the stoma color, the appliance condition, and the peri-stomal skin. This baseline matters because changes over time are what get missed in routine assessments. Next, assess urinary output patterns. For patients with Foley catheters, measure and document hourly output in mL. For non-catheterized patients, document fluid intake, voiding frequency, and any reports of urgency, hesitancy, or incontinence. Use standardized tools like the IADLs scale or the Braden Scale sub-scores for moisture when relevant. Do not skip the neurological component. Urinary retention can be the first sign of cauda equina syndrome or spinal cord compression. Document perineal sensation, anal sphincter tone if indicated, and lower extremity strength. These are the findings that get overlooked and then become medicolegal problems later. Then move to the physical exam. Palpate the suprapubic area for distension. Percuss for bladder fullness. Assess for costovertebral angle tenderness if renal involvement is suspected. Check for edema in the lower extremities. Document everything with specific measurements. A bladder scan reading of 350 mL post-void residual is infinitely more useful than "bladder appears distended."
A Real Problem I Encountered
About two years ago, I was reviewing a case involving an elderly post-operative patient who had developed acute urinary retention. The nursing notes documented "patient uncomfortable, requested assistance to bathroom" and then later "Foley inserted, output obtained." That was it. No post-void residual measurement before the Foley, no assessment of bladder distension on palpation, no documentation of the catheter insertion rationale beyond "patient uncomfortable." When the case went under review, the hospital was exposed because there was no objective evidence that retention had actually been present before the catheter was placed. The workaround I ended up using was a simple protocol change: we started requiring a bladder scan reading to be documented in the chart before any urgent catheterization, unless the patient was in frank distress requiring immediate decompression. Even then, a post-decompression scan was mandatory within fifteen minutes. This cut down on defensive documentation issues almost immediately. The biggest mistake I see is documentation that reflects completion of a task rather than clinical assessment. Writing "restrained per protocol" or "catheter care performed" is not an assessment. It is a task checklist. Auditors and peer reviewers can spot this instantly. Every entry should answer the question: what did you find, and how does it compare to the previous finding? Another pitfall is inconsistent timing. If you document output as "800 mL overnight" without breaking it into hourly or shift-based segments, you have lost critical information. Sepsis protocols and fluid balance calculations depend on trending data, not totals. I always document output in hourly increments for unstable patients and at minimum every four hours for stable patients on a medical-surgical floor.
Get the Full Details

A third issue is failing to document the patient's own reported symptoms. If a patient says their urine smells strong or they feel burning on voiding, that goes in the chart exactly as they said it. Do not paraphrase into clinical terminology that changes the meaning. "Patient reports dysuria" is acceptable but less precise than "patient reported burning sensation with urination starting approximately two hours after last void." The latter gives someone reviewing the chart a clear timeline.
What Beginners Miss
Most nursing students are taught to assess the GU system in isolation. In practice, genitourinary findings are almost never isolated. A patient with decreased urinary output may have cardiogenic shock, sepsis, renal artery stenosis, or simply be volume depleted from excessive diuretic use. The documentation should reflect this clinical reasoning. Note the patient's vital signs, fluid balance trends, medication list including diuretics and nephrotoxic agents, and any recent changes in status. The chart should read as a connected narrative, not a series of disconnected data points. Here is a counter-intuitive point that took me a while to internalize: documenting a normal genitourinary assessment is just as legally important as documenting an abnormal one. A blank or minimally documented GU section in a chart is red flag number one for reviewers. It suggests the assessment was not performed. Write "GU assessment normal: no suprapubic tenderness, no CVA tenderness, Foley draining clear yellow urine at 40-50 mL/hr, perineal skin intact, no erythema or excoriation" even when nothing is wrong. Completeness beats brevity every time in these situations.
Documentation Standards to Keep in Mind
The legal standard for nursing documentation is the same whether you are charting a head-to-toe assessment or just the genitourinary system. The record must be accurate, complete, timely, and legible. Timely means documenting as close to the time of assessment as possible. If you assess a patient at 1400 and do not chart until 1730, note the actual time of assessment and the time of documentation. This distinction matters in litigation because it demonstrates awareness of the requirement for contemporaneous records. Use objective language throughout. Avoid terms like "apparently," "seemingly," or "roughly." These introduce uncertainty into your documentation. If you are unsure about a finding, document that you are unsure and what you did to resolve the uncertainty. "Bladder scan unreliable due to patient body habitus; manual palpation performed instead, noting moderate suprapubic fullness" is far stronger than "bladder may be full." When documenting patient education related to genitourinary health, be specific about what was taught and the patient's response. "Education provided regarding signs of UTI including fever, cloudy urine, and dysuria. Patient verbalized understanding and demonstrated correct peri-care technique." This creates a defensible record that the teaching occurred and was comprehended.

The Bottom Line
Genitourinary assessment nursing documentation is not about filling out forms. It is about creating a clinical narrative that stands up to scrutiny from other healthcare providers, from hospital compliance teams, and potentially from legal professionals. The format should be consistent, the language should be precise, and the timeline should be clear. If you follow a structured approach and document what you actually found rather than what you assume was done, your charts will be stronger and your patients will be safer. I still see too many nurses treating this section as an afterthought. It should not be. The genitourinary system gives you early warnings about fluid status, renal perfusion, neurological integrity, and infection. Document those signals properly and the rest of the chart gets stronger too.