What Actually Happens When You Try To Process Negative Emotions
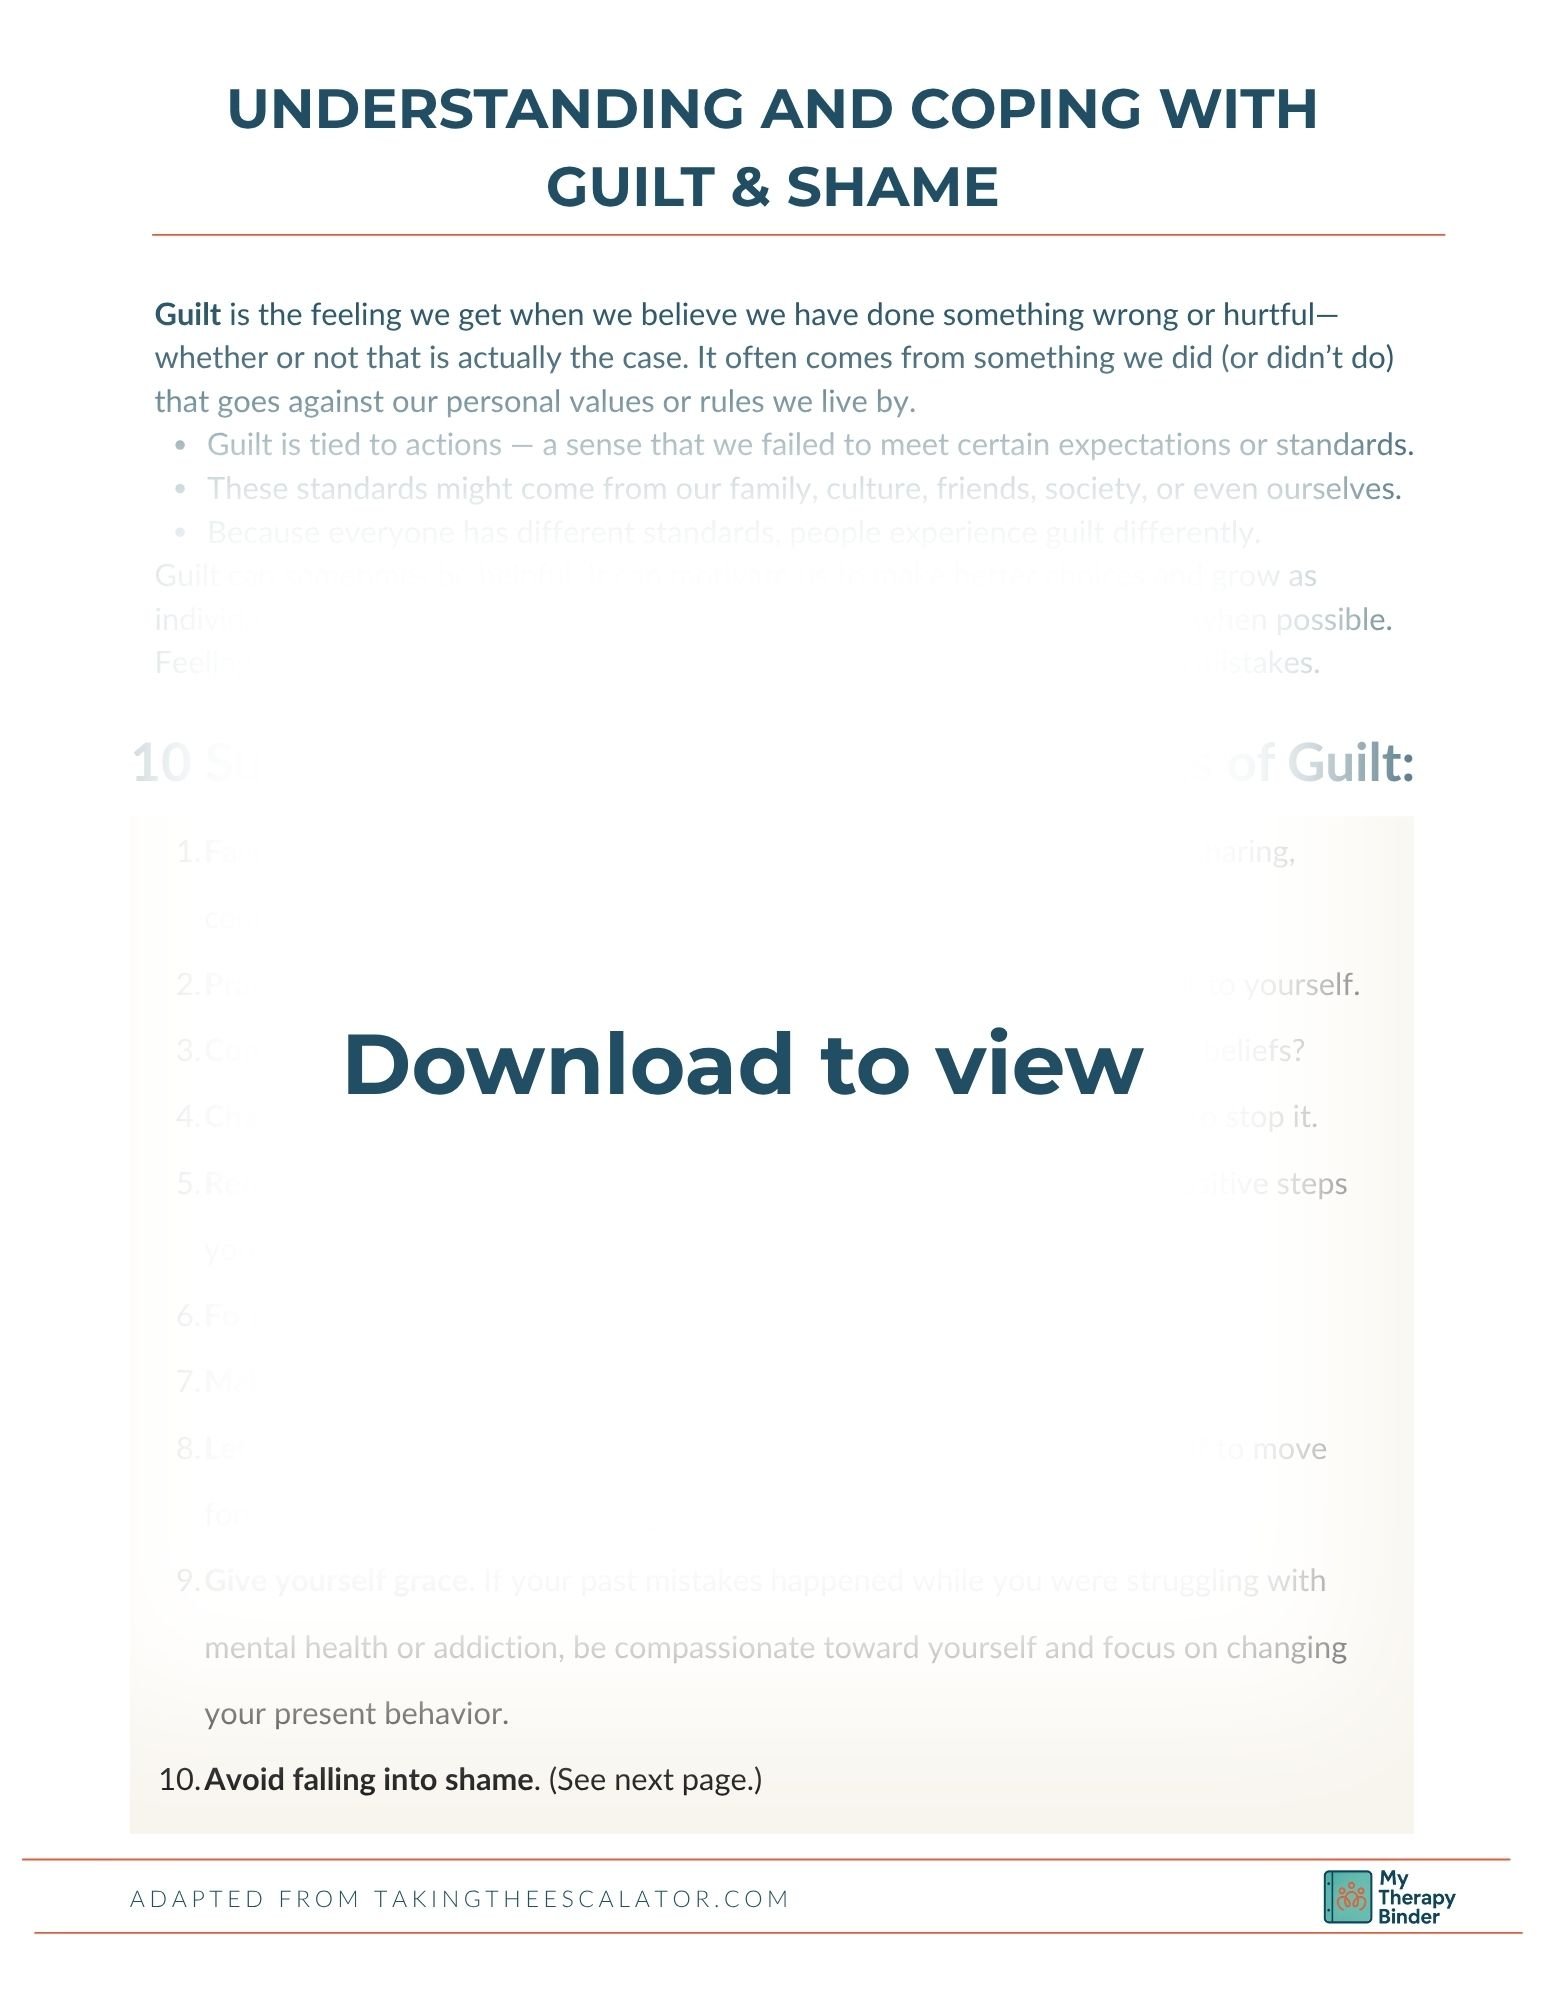
Most people approach guilt, shame, and anxiety as three separate problems that need fixing. They are not. They operate on the same underlying circuit. When you understand the mechanism, you stop fighting symptoms and start addressing the root pattern. I spent years working with clients who came in saying they had anxiety, then guilt, then shame, and every time we treated one, another showed up in its place. The breakthrough came when we stopped treating them as distinct conditions and started mapping them to the same avoidance behavior. Guilt says you did something wrong. Shame says you are wrong. Anxiety says something bad will happen. All three serve the same function: they push you away from something uncomfortable so you do not have to sit with it.
Guilt Shame And Anxiety Understanding And Overcoming Negative Emotions
The work falls into two buckets. The first is cognitive defusion, which comes from acceptance and commitment therapy. The second is shame resilience, which Brené Brown's research popularized but which most people misunderstand because they treat it as about self-compassion when it is actually about naming the emotion out loud in the presence of someone who will not fix it for you. Here is the practical method I use. It is called the triage exercise. It takes about twenty minutes and usually cuts the internal spiral down from hours of rumination to something manageable in a single session. Step one: write down every thought you are having about the situation. Not feelings. Thoughts. "I should have said something." "They probably think I am selfish." "I am going to lose this job." Get them on paper. This takes most people ten to fifteen minutes because they start filtering what is acceptable to write. Do not filter. The filtering is the problem.
Step two: tag each thought as guilt, shame, or anxiety. Guilt thoughts contain action language. Should, could, would have. Shame thoughts contain identity language. I am, I always, I never. Anxiety thoughts contain prediction language. Will happen, might go wrong, something bad. Step three: look at the tags. You will usually find one dominant category. For most people it is shame, even when they think they are dealing with guilt. This is the part that surprises people. Guilt is fixable. Shame is not. Guilt says the behavior was bad. Shame says you are bad. Fixing the behavior resolves guilt in one conversation. There is no behavior to fix when shame is the driver, so the standard advice people give you does nothing. I had a client once who came in convinced she was dealing with guilt about missing her mother's birthday. She had a whole list of ways she could make it up to her. What she was actually carrying was shame about growing up in a household where her emotions were treated as inconvenient. Missing the birthday was just the symptom that surfaced. We spent three sessions on the birthday before she admitted the real thing. The workaround was simple. I asked her to describe what she would say if she were talking to a five-year-old who felt exactly what she felt. She cried. Then she stopped. Then she could actually talk about the grief underneath the shame. It took seven sessions total, not because the method was complicated but because she had spent twenty years building defenses around it.
Get the Full Details
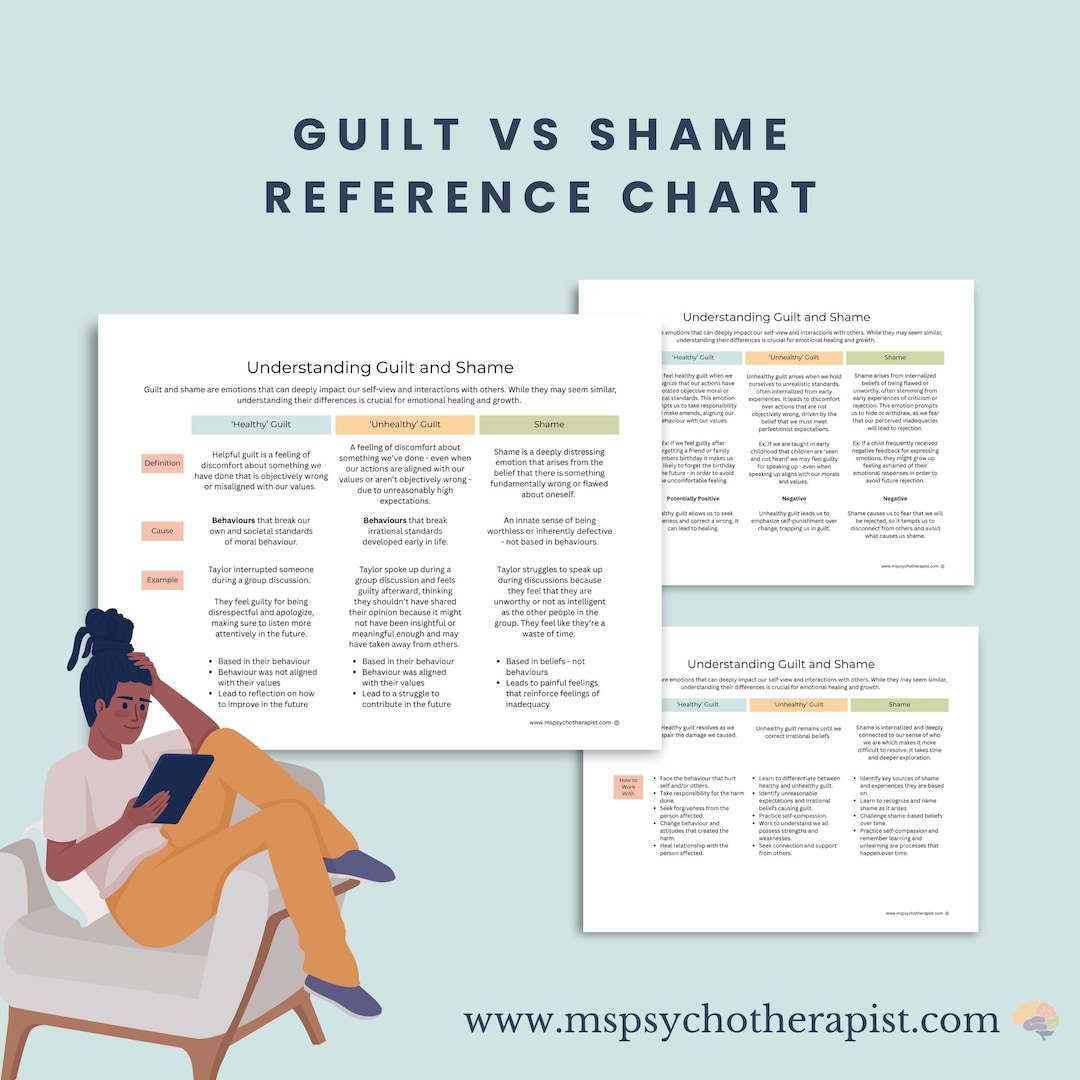
The third step of the triage exercise is the pivot. Once you know which category is dominant, you apply the corresponding intervention. For guilt, you take responsibility and make amends. That is straightforward. For shame, you share the story with one safe person and notice whether the world ends. It does not. For anxiety, you run a probability assessment. Write down the worst-case scenario, then write down the actual odds based on evidence, not feeling. This usually collapses the anxiety because it was running on vague threat detection instead of actual data. There are limitations to this approach that nobody talks about. The triage method assumes you have the cognitive capacity to write things down and categorize them. It does not work well during acute panic attacks or when you are in a severe depressive episode. In those cases, you need stabilization first. Breathing protocols, grounding techniques, sometimes medication. The framework is for the stuff that lingers, not the stuff that knocks you flat. If you try to do cognitive work while your nervous system is in fight-or-flight, you will just get more frustrated and conclude the method does not work. Another common pitfall is the overcorrection toward toxic positivity. People read about acceptance and compassion and interpret it as meaning they should feel better immediately. It does not mean that. It means you stop arguing with reality. The emotion can still hurt. The work is about changing your relationship to the hurt, not erasing it. That distinction matters because it prevents the secondary shame that comes when you feel guilty about feeling guilty.
The shame piece specifically has a trap that catches a lot of people. Sharing your story with a safe person sounds simple but the selection matters enormously. If you share with someone who immediately offers solutions or sympathy, you are not building resilience. You are outsourcing regulation. The person needs to be able to sit with you in the discomfort without trying to fix it. That is a rare skill. Most people will try to help and do more harm than good because your nervous system picks up on the urgency in their voice and interprets it as confirmation that something is wrong. I learned this the hard way with my own anxiety. I had been sharing my worries with my partner for years and assumed that was healthy. It turned out I was just conditioning her to become my emotional regulator. When I started working on the actual skill of sitting with the uncertainty, our relationship changed because I stopped using her as a buffer. That is not a criticism of her. It is a recognition that I was using closeness as a substitute for self-regulation. The work is uglier that way but it actually moves the needle. If you want a structured way to start, there are workbooks based on ACT and CBT that walk through the triage exercise in detail. The Williams and Penman book on mindfulness is solid for the foundational piece. For shame specifically, Brown's research summaries are accessible but the real work happens in the exercises, not the reading. You cannot think your way out of shame. You have to feel it and survive it.
The anxiety framework overlaps heavily with exposure and response prevention, which is the gold standard for OCD but applies broadly. The principle is the same. You expose yourself to the uncertainty you have been avoiding and you refrain from the compulsion that usually neutralizes it. For anxiety, the compulsion is rumination, reassurance-seeking, or avoidance. Breaking the loop usually takes four to six weeks of consistent practice before the neural pathway starts to rewire. That is the timeline. Not three days. Not one weekend. Four to six weeks. Here is something most guides leave out. Guilt, shame, and anxiety are not pathological by default. They are signals. Guilt signals a values violation. Shame signals a social threat. Anxiety signals an uncertainty gap. The problem is not that you feel them. The problem is that you treat every signal as an emergency that requires immediate resolution. When you can let the signal exist without acting on it, the intensity drops on its own. It is like holding a beach ball underwater. It takes effort to keep it down. If you stop pushing, it floats to the surface and stays there. The discomfort is temporary. The effort to suppress it is what makes it chronic. I do not recommend this approach for everyone. If you are dealing with clinical depression, complex trauma, or an anxiety disorder that meets diagnostic thresholds, you need professional support alongside any self-help framework. The triage exercise is a tool, not a treatment plan. It works best when layered on top of therapy, not as a replacement for it. But for the everyday version of these emotions that most people carry around without realizing it is optional, it is often enough to change the trajectory.