Understanding H1 And H2 Antagonists: A Practical Guide
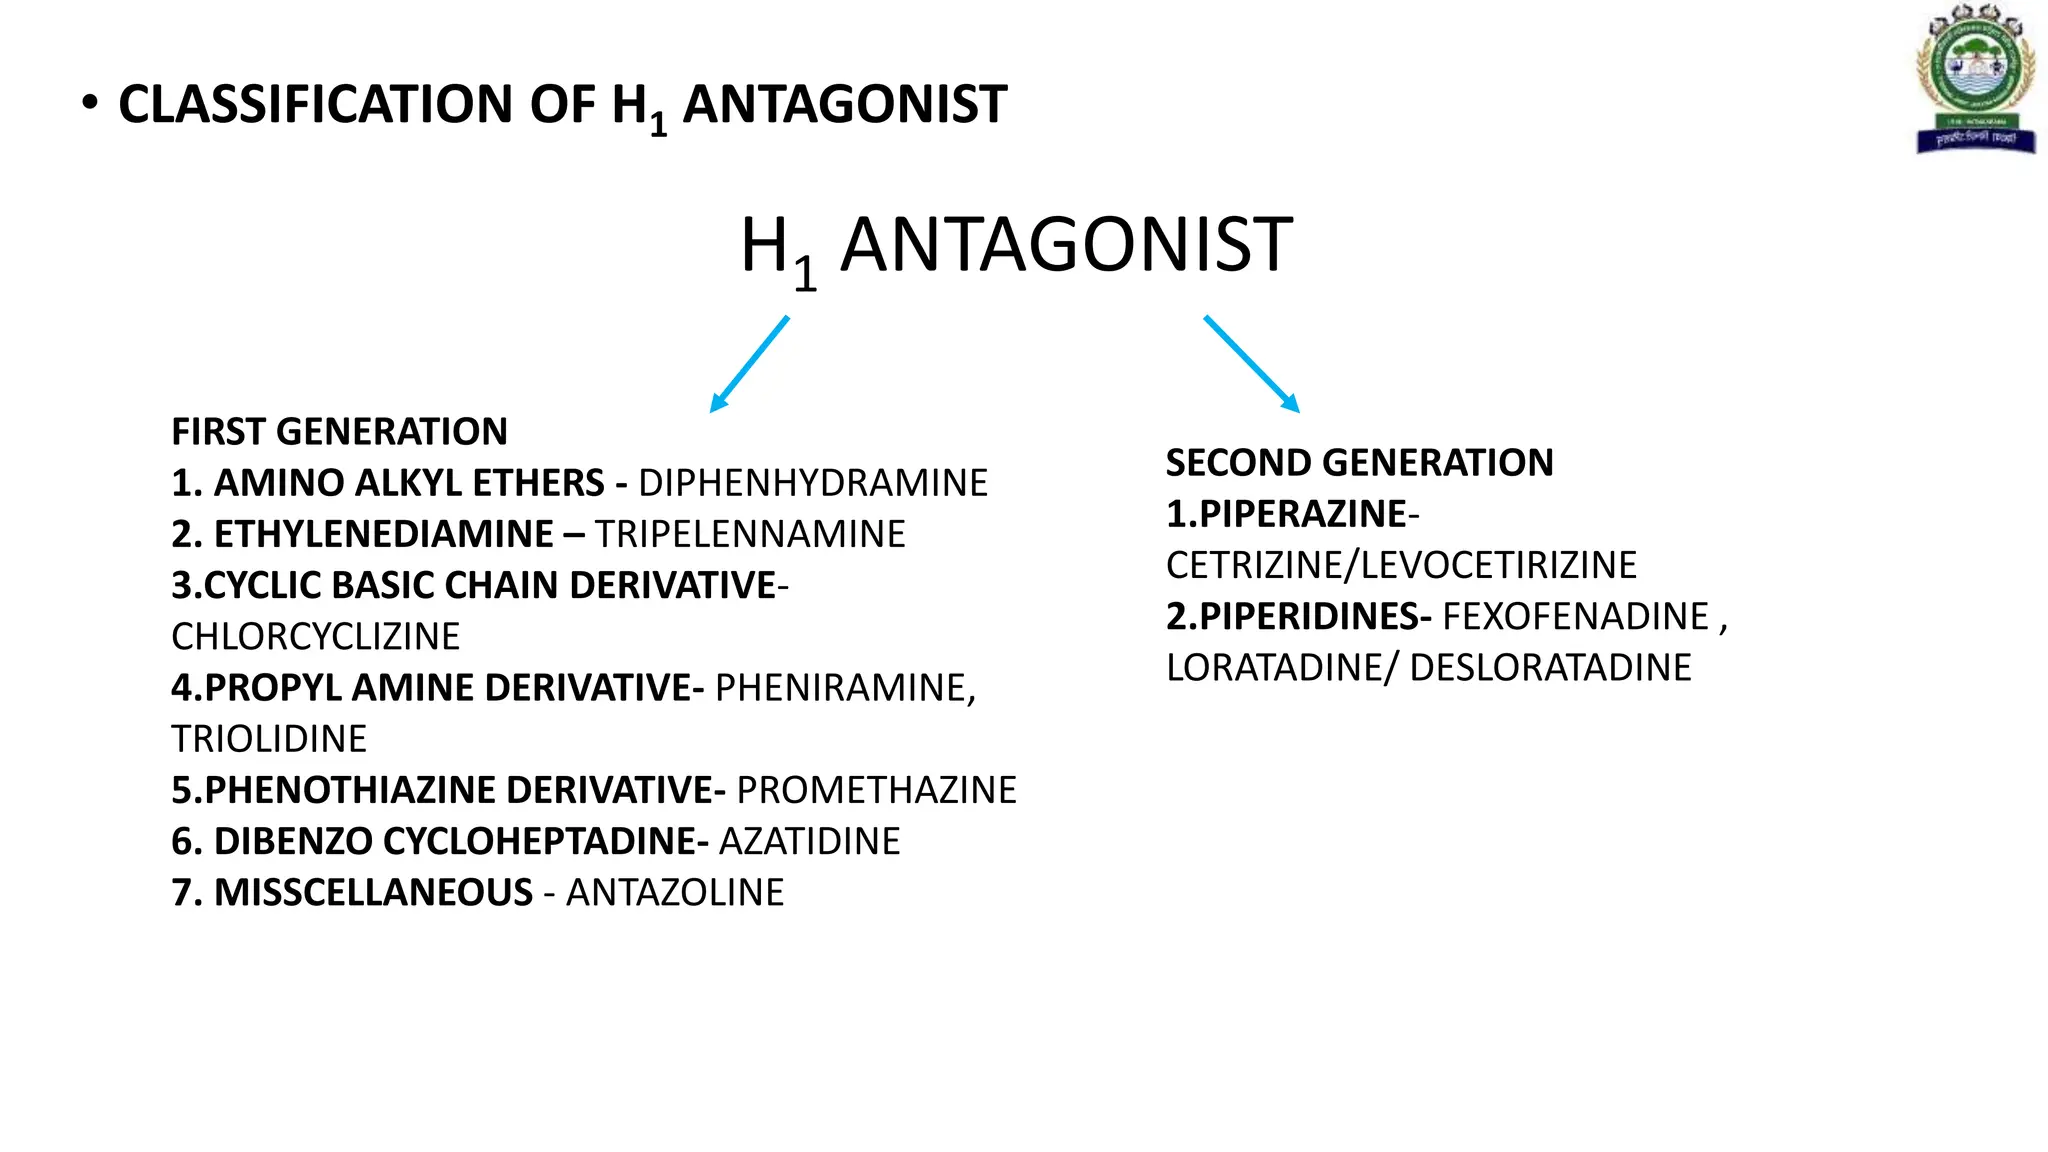
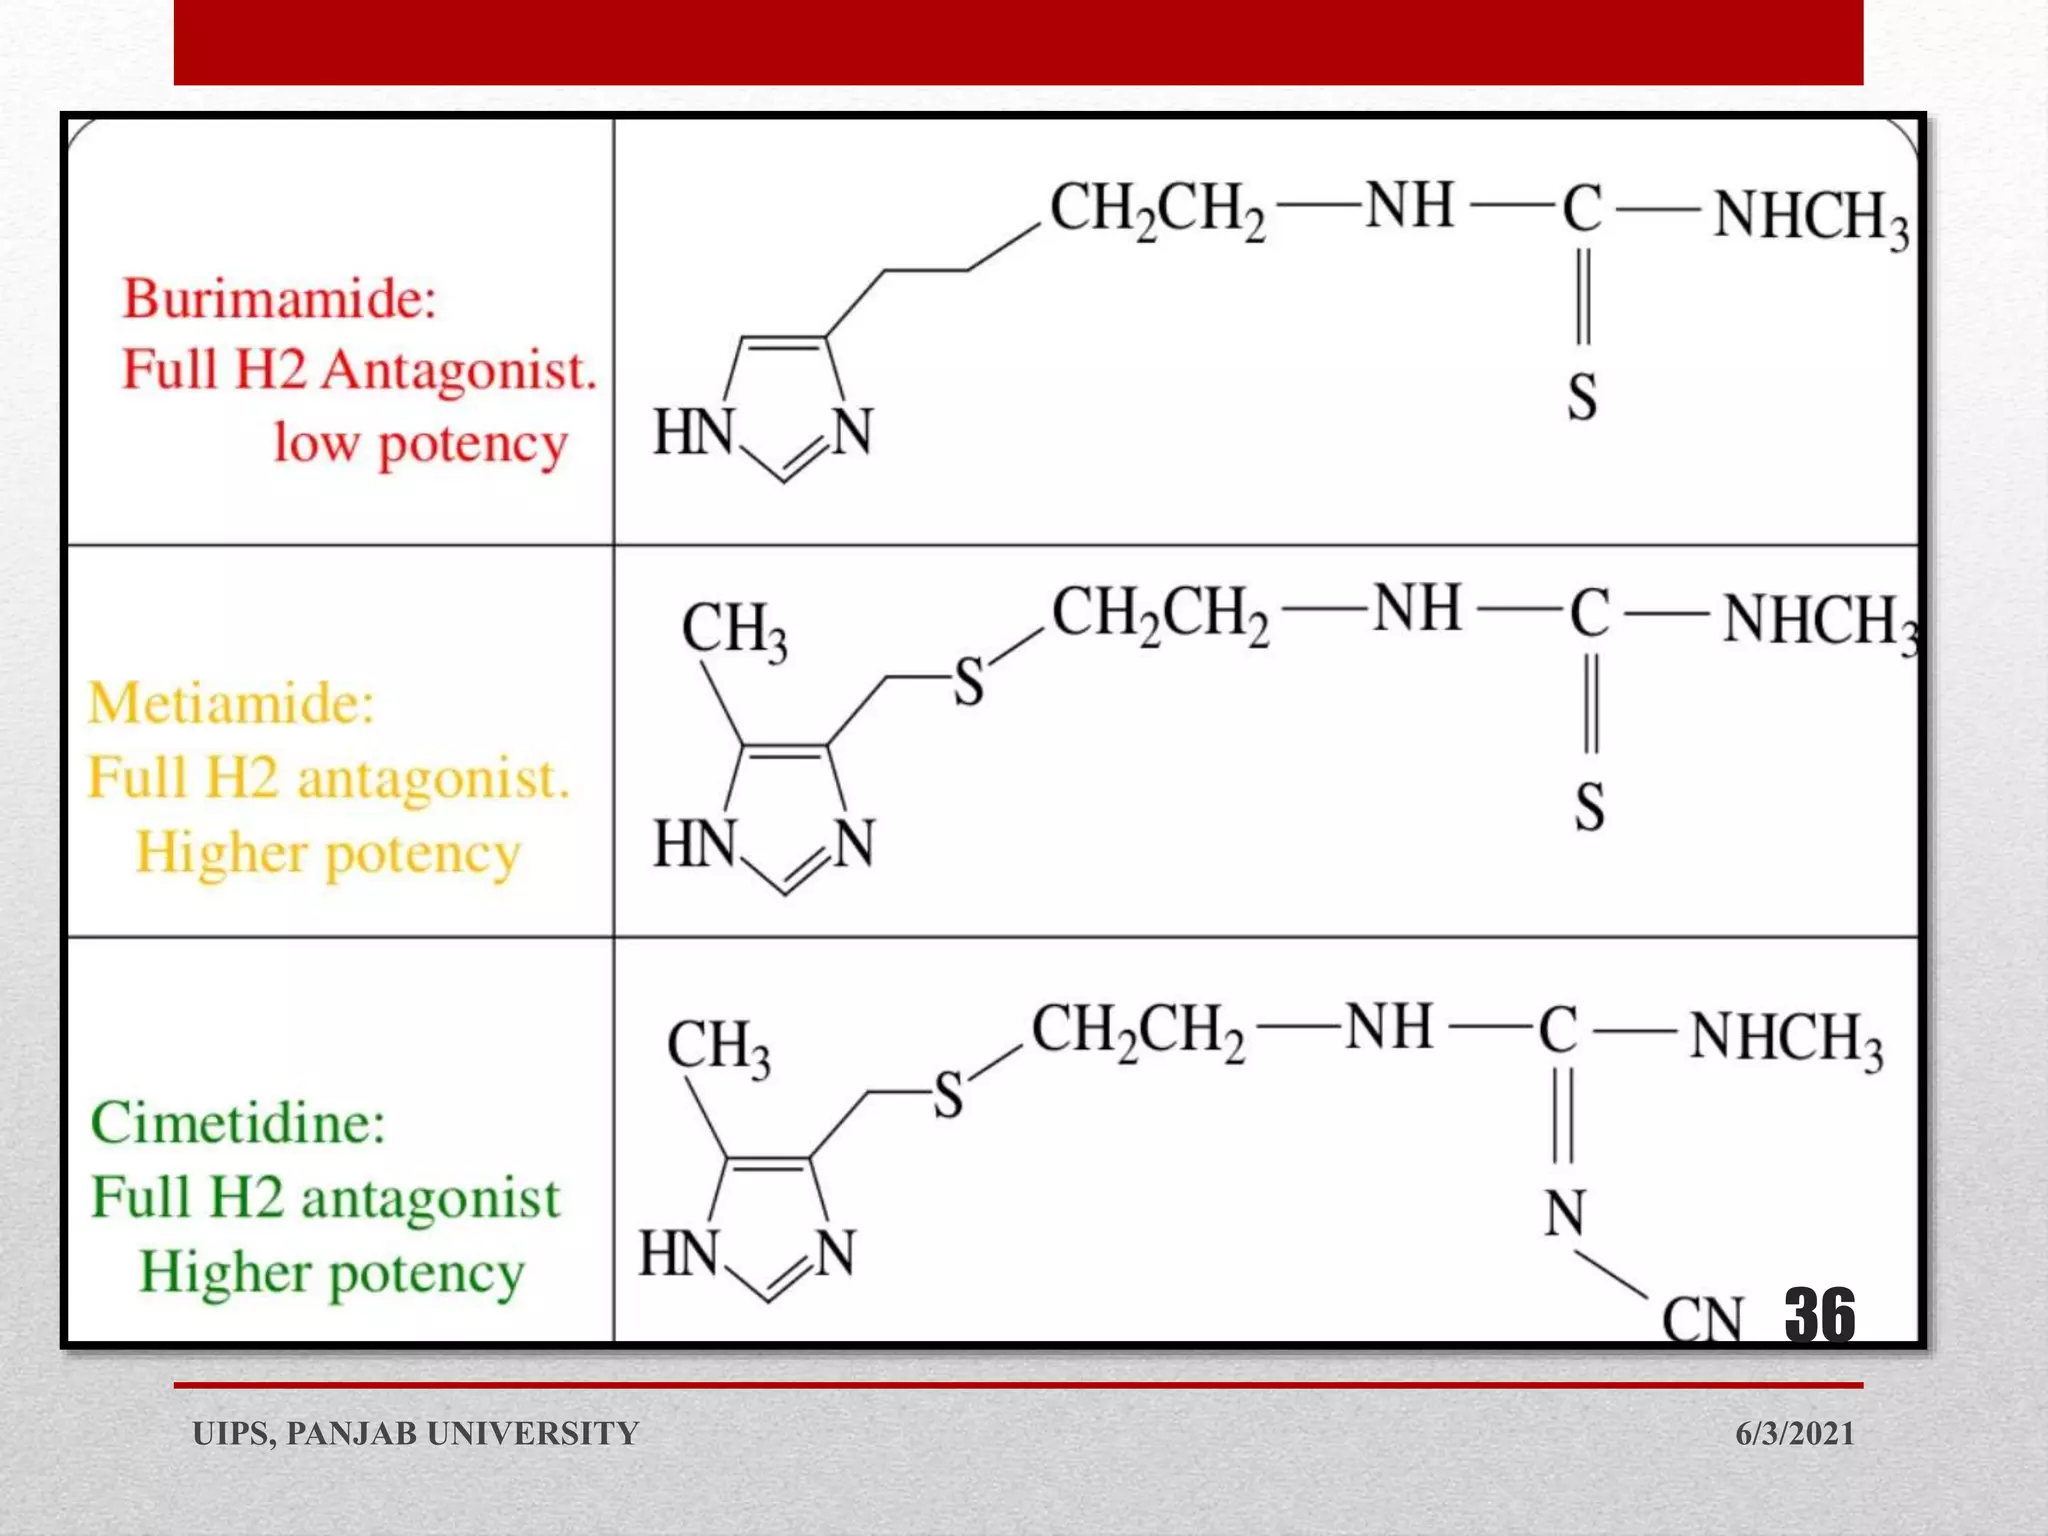
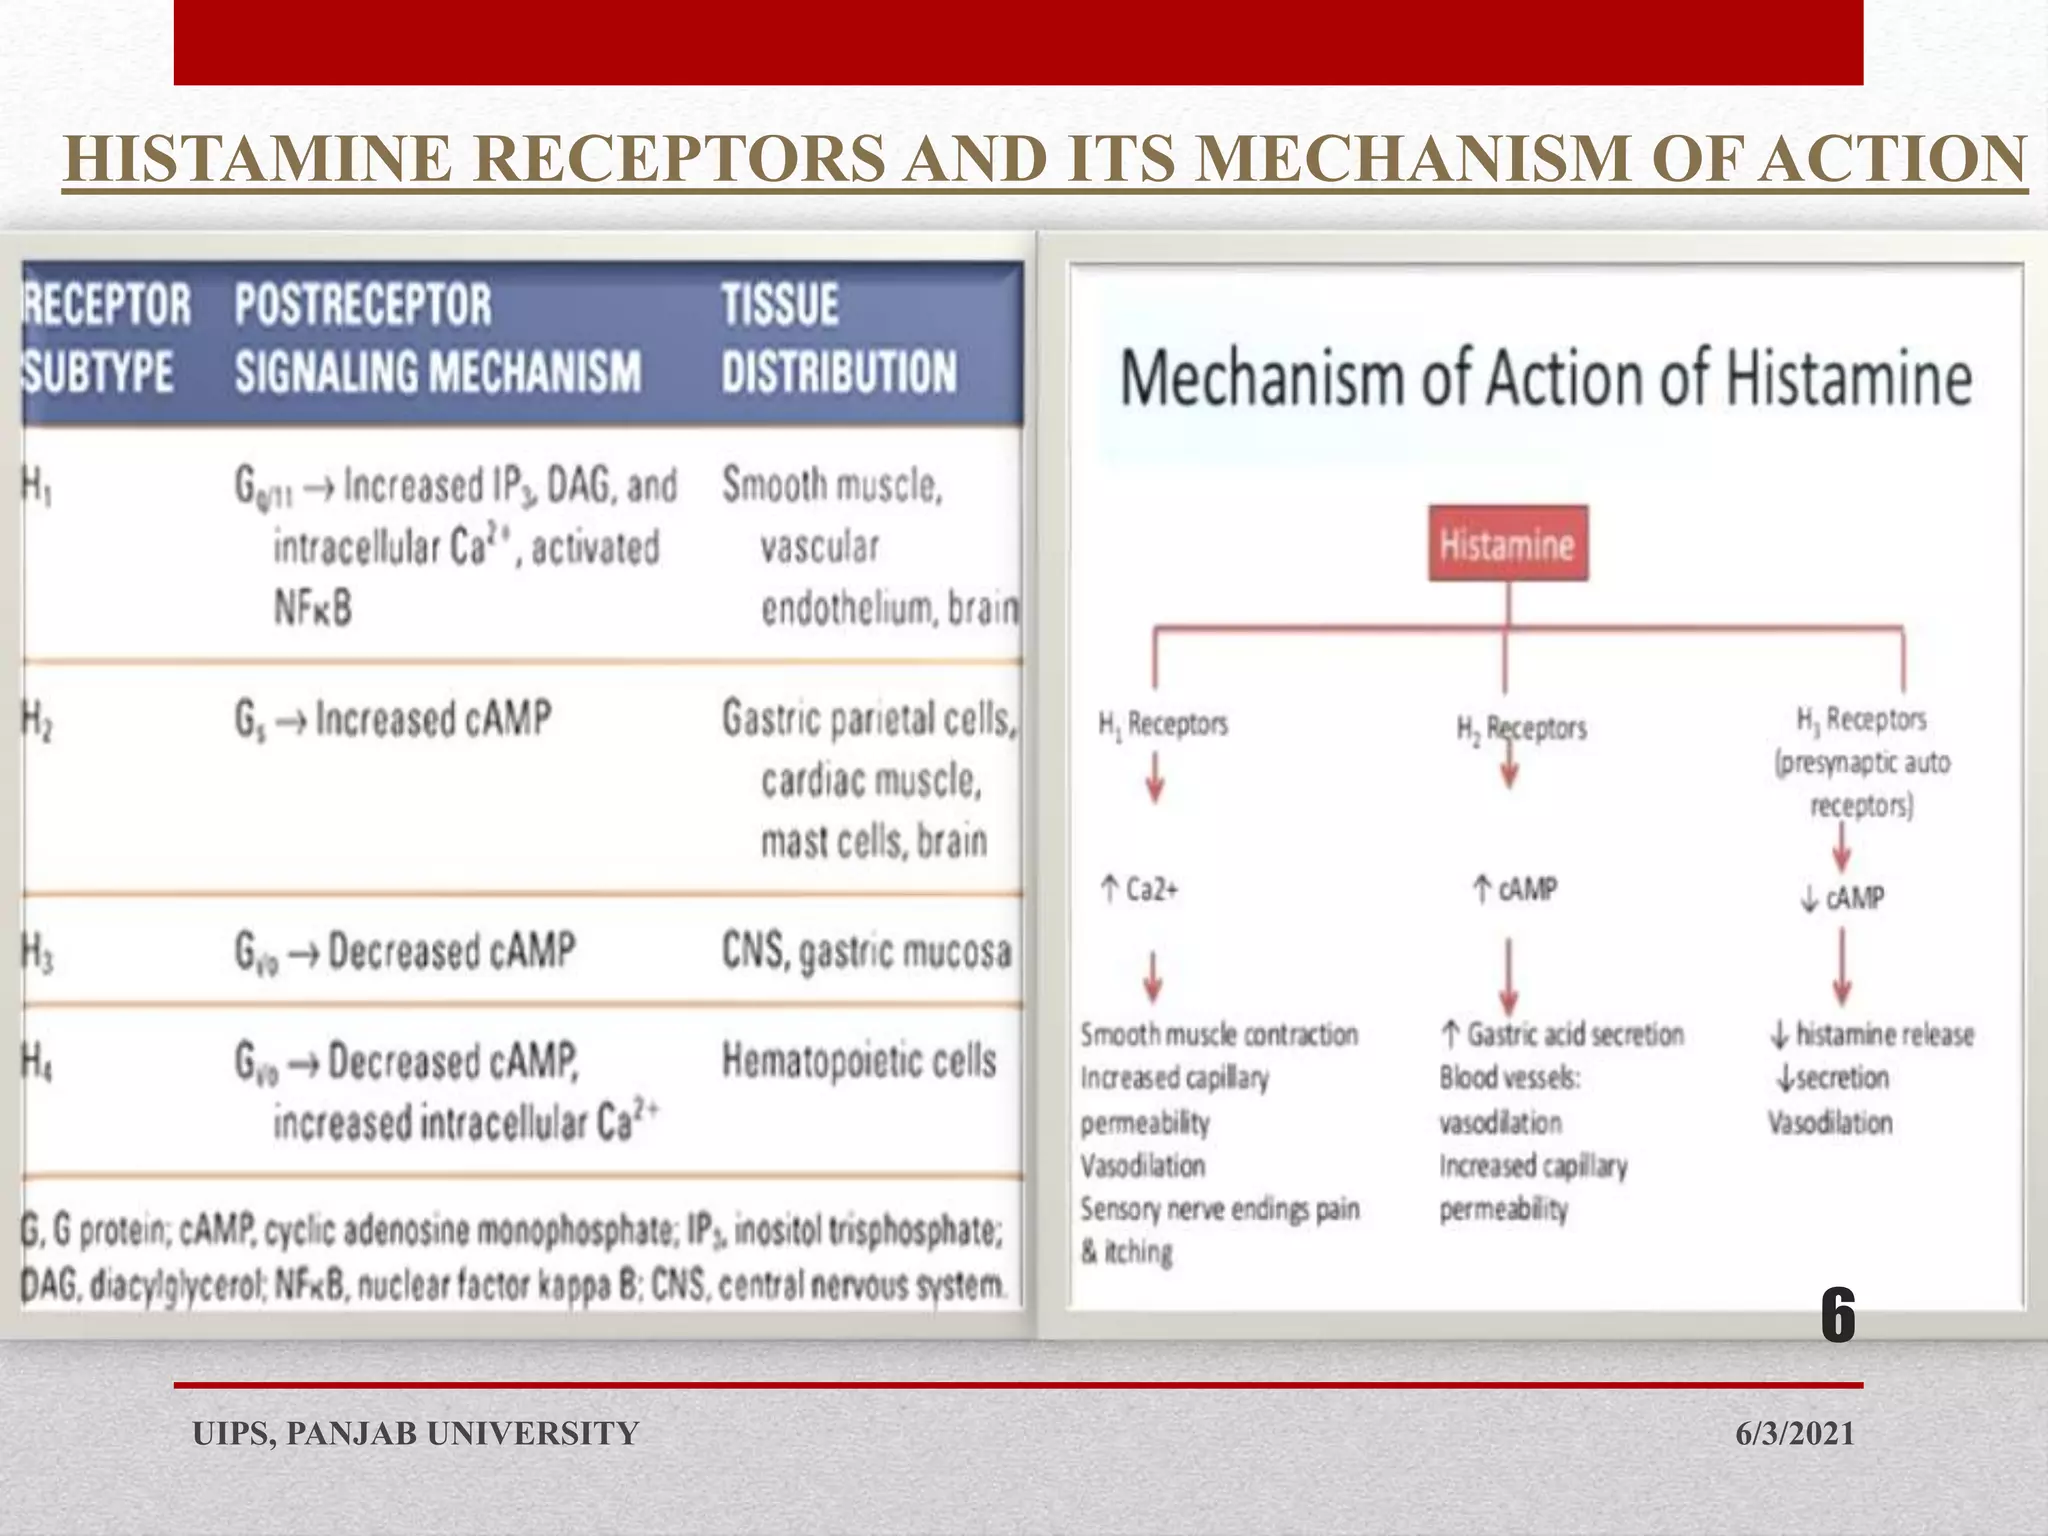
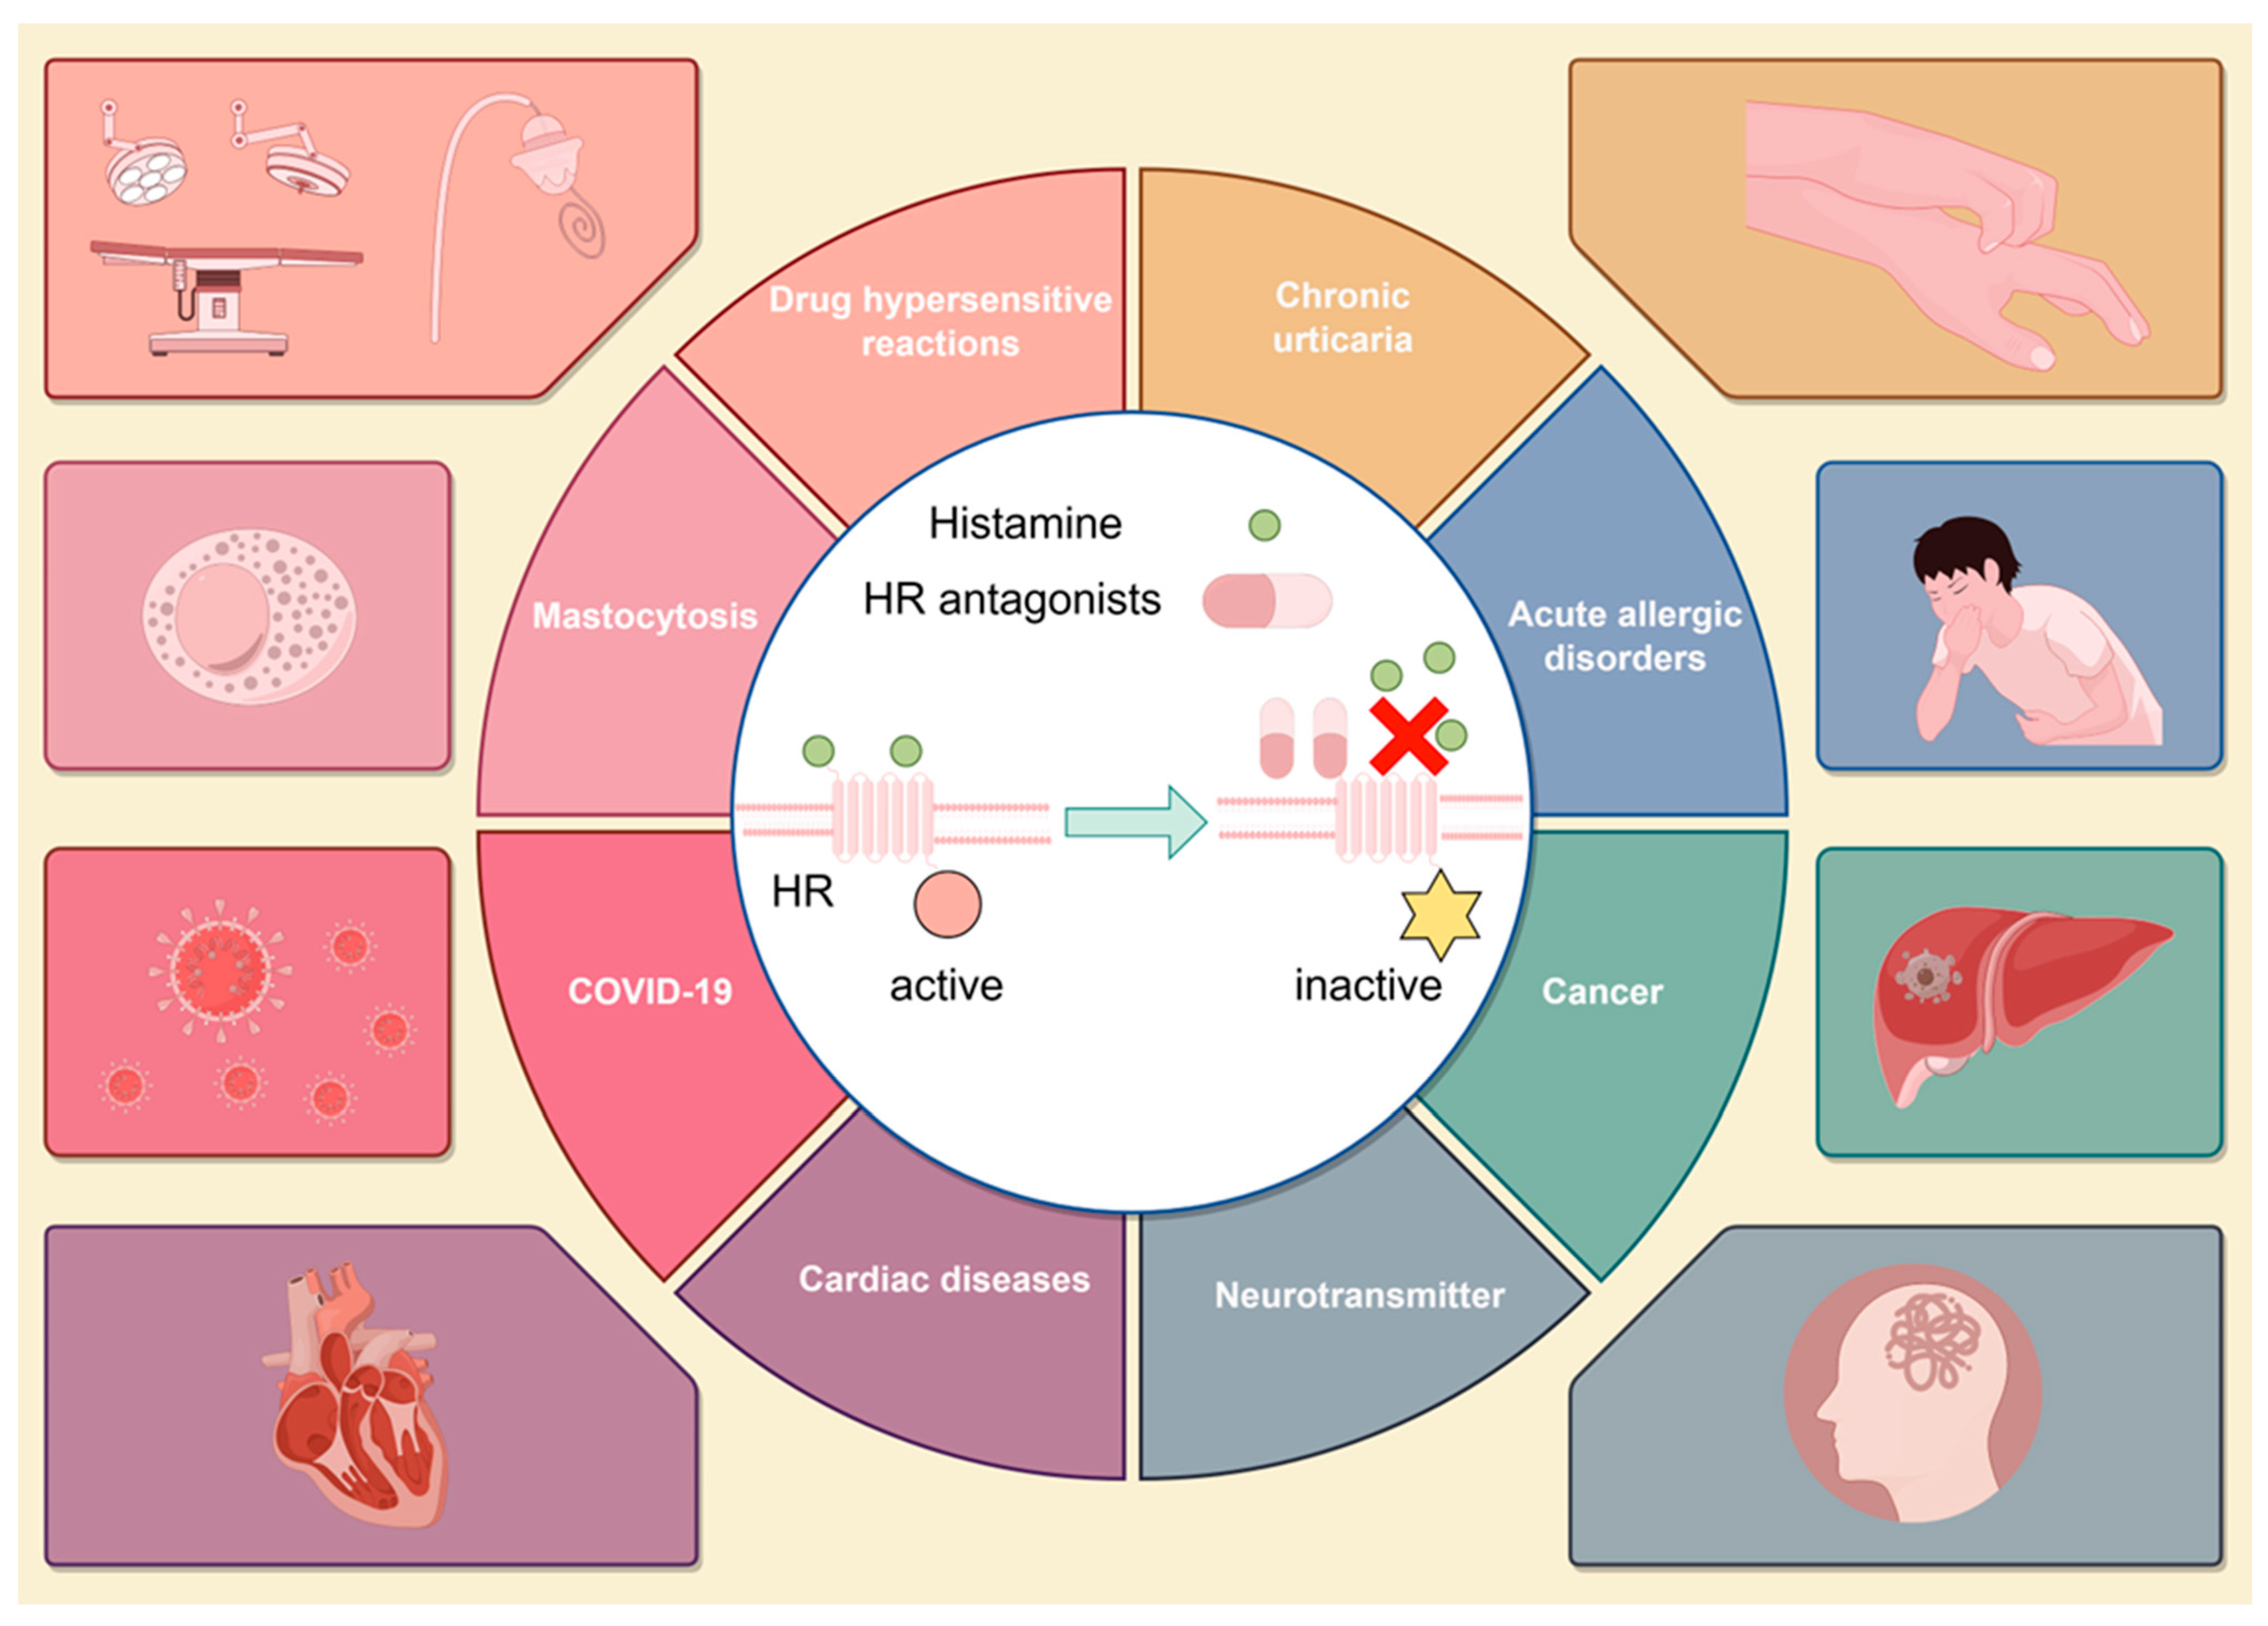
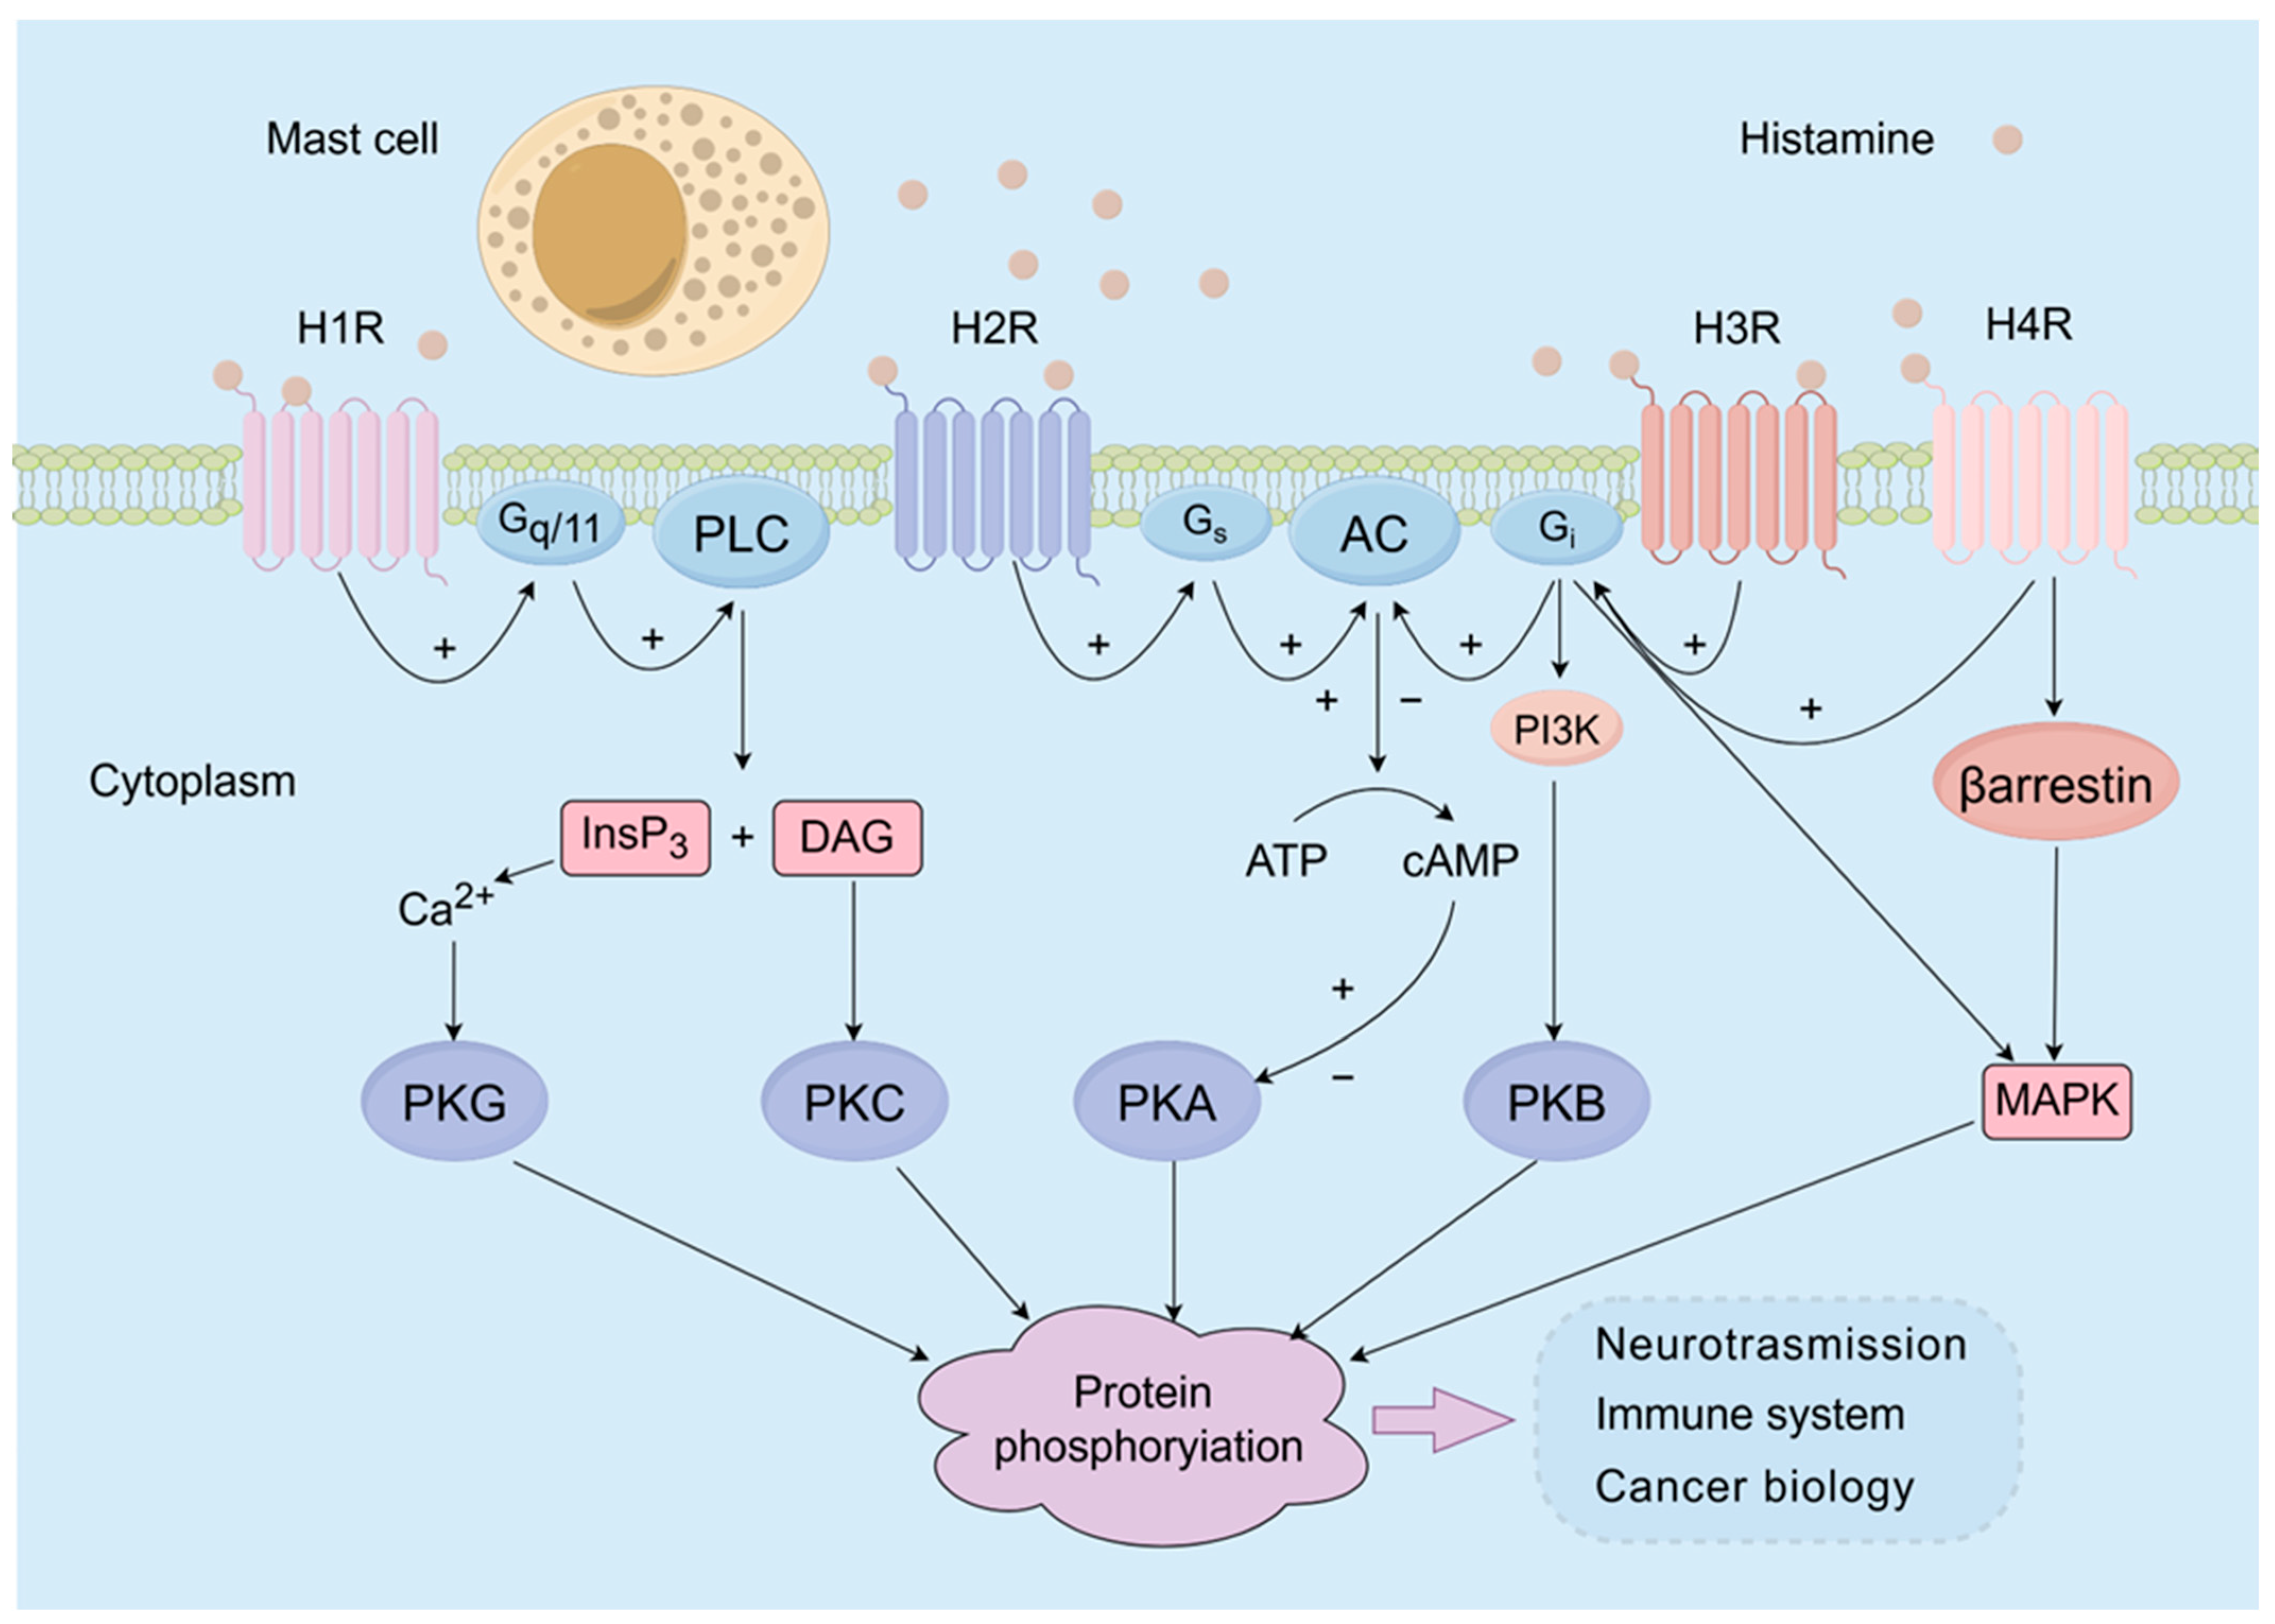
Most people know antihistamines as something you grab at the pharmacy when pollen season hits. The reality is a bit more layered than that, and knowing the difference between H1 and H2 blockers can actually matter when you are dealing with persistent symptoms that a standard dose of loratadine simply will not touch. H1 antagonists block histamine from binding to H1 receptors, which are found in your blood vessels, bronchial smooth muscle, and nasal tissues. When histamine latches onto those receptors, you get the classic allergy cascade: itching, sneezing, runny nose, vasodilation, and smooth muscle contraction. Blocking H1 receptors interrupts that process. That is why first-generation drugs like diphenhydramine make you sleepy — they cross the blood-brain barrier and block histamine in your central nervous system, which is also a key wakefulness signal. H2 antagonists work on a completely different receptor system. H2 receptors are primarily located in the parietal cells of the stomach. Histamine binding to H2 receptors triggers gastric acid secretion. Cimetidine, ranitidine, famotidine, and nizatidine block that interaction. These are the drugs you see marketed for heartburn and peptic ulcer disease, not for allergies.
The H1 And H2 Antagonists Connection
The reason these two classes get grouped together is not because they treat the same thing. It is because histamine acts through multiple receptor subtypes, and in certain clinical situations you need to address both pathways simultaneously. This comes up more often than most general practitioners bother to consider. I ran into this a few years back when a patient came in with chronic urticaria that was completely refractory to second-generation H1 blockers at standard doses. Cetirizine at ten milligrams daily, fexofenadine at one hundred eighty milligrams, you name it. Nothing moved the needle. Her hives flared daily, mostly at night, and she was exhausted from the cycle of itching and disrupted sleep. I had her running a histamine diary alongside her medication log, and the pattern was clear: the flares were worse after meals, especially meals high in aged cheeses, fermented foods, and wine. That meal-related timing was the clue that H2 receptors were playing a role here, since histamine release from mast cells during digestion was getting amplified by the H2-mediated gastric response. The workaround was straightforward but not exactly standard protocol. We added famotidine at forty milligrams twice daily to her existing cetirizine regimen. Within three days the nightly hives dropped from severe to barely noticeable. Within two weeks she was essentially symptom-free on the combination. This is actually documented in dermatology literature, but you would be surprised how many prescribers have never considered it. The British Association of Dermatologists has included this combination approach in their urticaria guidelines, yet it rarely shows up in primary care discussions.
Key Differences You Need to Know
Sedation is the first major distinction. First-generation H1 antagonists like promethazine and hydroxyzine cause significant drowsiness in a large percentage of users. Second-generation agents such as levocetirizine, desloratadine, and bilastine were specifically designed to avoid this. They do not cross the blood-brain barrier nearly as efficiently. If you are driving or operating machinery, stick to the newer agents. H2 antagonists generally do not cause sedation, though cimetidine has a broader side effect profile including anti-androgenic effects and cytochrome P450 inhibition, which can mess with the metabolism of other drugs like warfarin and phenytoin. Onset and duration vary significantly within each class. Intravenous diphenhydramine starts working within minutes and lasts about four to six hours. Oral fexofenadine takes roughly an hour to peak and covers you for twenty-four hours. Famotidine onset is about thirty minutes orally and lasts twelve to twenty-four hours depending on the dose. This matters when you are trying to match medication timing to your symptom pattern. There is also a meaningful difference in how these drugs interact with food. H2 antagonists like famotidine can be taken with or without food without major impact on absorption. But some H1 antihistamines have food interactions worth noting. Bilastine, for example, has dramatically reduced bioavailability when taken with food or grapefruit juice. You have to take it on an empty stomach, at least one hour before or two hours after eating. If you miss that window, you are essentially wasting the dose.
Get the Full Details
When the Standard Approach Fails
Not every case of histamine-mediated illness responds to simple receptor blockade. There are patients with mast cell activation syndrome where the problem is not receptor sensitivity but the sheer volume of histamine being dumped into their system. In those cases, adding a second H1 blocker or throwing an H2 antagonist at the problem might buy some relief, but the underlying issue requires a different strategy altogether. Mast cell stabilizers like cromolyn sodium, low-histamine dietary modification, and in severe cases immunosuppressive therapy become necessary. Another scenario where H1 antagonists fall flat is angioedema that is not histamine-mediated. ACE inhibitor-induced angioedema involves bradykinin, not histamine. Antihistamines will not help you there, and giving them creates a false sense of security while the airway situation worsens. This is one of those distinctions that separates routine allergy management from actual clinical judgment. Routine use of H2 antagonists for acid-related conditions has also shifted over the years. Ranitidine was pulled from the market in 2020 due to NDMA contamination concerns, which is a reminder that drug safety profiles are not static. Famotidine remains widely available and is generally considered safe for long-term use at appropriate doses. Cimetidine, the oldest H2 antagonist, is still effective but its drug interaction profile makes it a poor choice for anyone on multiple medications.
Practical Dosing Notes
For occasional allergic rhinitis, a second-generation H1 antagonist like cetirizine ten milligrams once daily or fexofenadine one hundred eighty milligrams once daily is usually sufficient. For acute urticaria, some specialists push the H1 blocker dose up to four times the standard recommendation. This is off-label but supported by guidelines, and it tends to be well tolerated since the newer agents have a wide safety margin. For combination therapy in refractory urticaria, famotidine forty milligrams twice daily paired with a non-sedating H1 antagonist is a reasonable starting point. Some patients respond to once-daily H2 blockade alone, but twice-daily dosing provides more consistent coverage, especially if symptoms follow a circadian pattern with evening worsening. If you are using an H1 antagonist for travel sickness, the first-generation options like dimenhydrinate or meclizine are your only real choices. H2 antagonists have zero antiemetic effect. This is one of the few situations where the older, more sedating H1 drugs are actually the better option, and the sedation is not a side effect but the therapeutic mechanism.
The main limitation of H1 and H2 antagonists combined is that they manage symptoms rather than address underlying causes. They are effective for acute episodes and chronic suppression in suitable cases, but they do not modify disease progression in conditions like asthma or autoimmune urticaria. If you find yourself needing continuous combination therapy beyond a few weeks without a clear diagnosis, getting a referral to an allergist or immunologist is the practical move rather than escalating medication on your own.