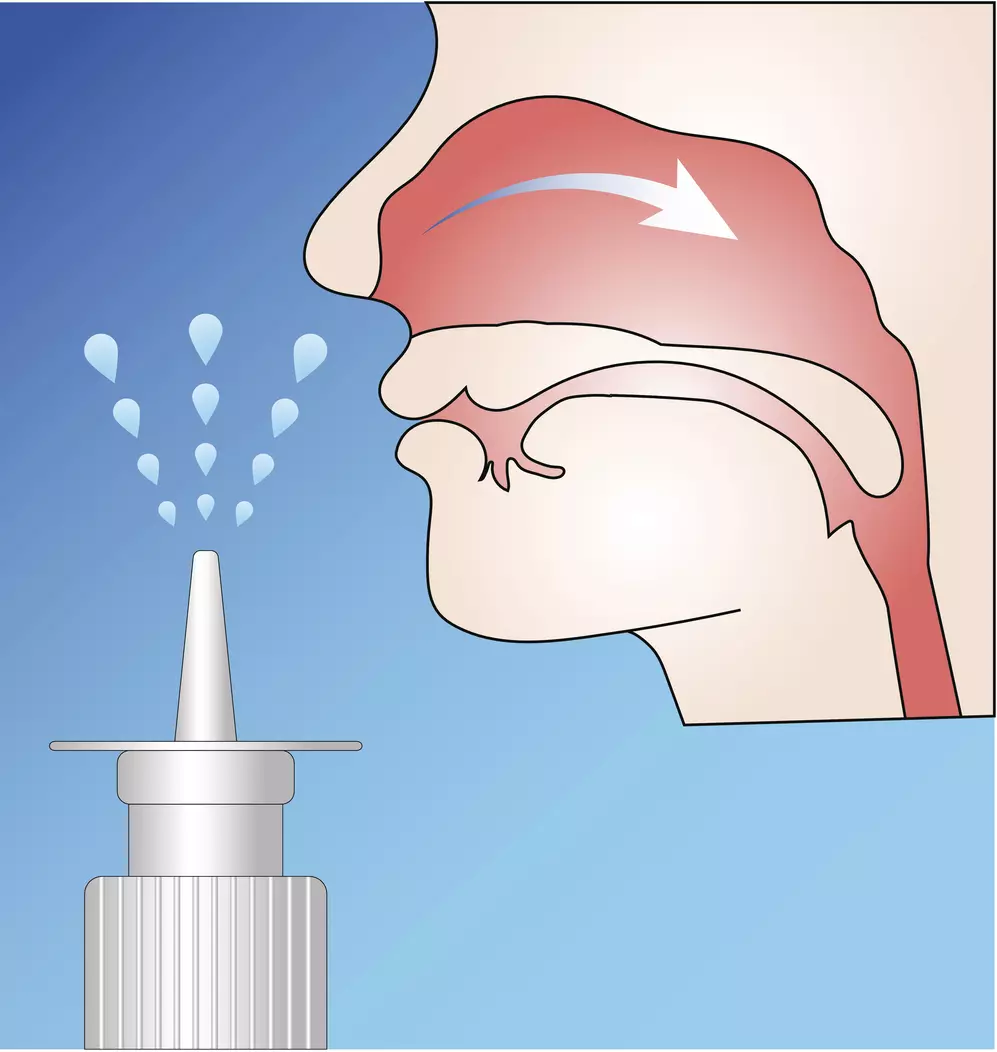
Post Nasal Drip Explanation and Treatment
Most people treat post nasal drip as a mucus problem. It is usually an inflammation problem disguised as a mucus issue. The drip itself is not the disease. It is the symptom your body produces when the nasal passages and sinuses are irritated for reasons that have nothing to do with infection. I spent years watching patients come in with the same complaint: constant throat clearing, a sensation of something stuck at the back of the throat, especially worse in the morning. The standard approach is saline rinses and antihistamines. That approach works sometimes. More often it fails because nobody checks the actual trigger. The mucus keeps coming from the same place regardless of what you throw at it. Identifying the source changes everything.
How Do You Stop Post Nasal Drip
The first step is figuring out what is irritating the mucosa. There are five common categories and they look identical on the surface. Allergic rhinitis is the most obvious. Pollen, dust mites, pet dander. The mucus is typically thin and watery. Eyes itch. You sneeze. If this is your trigger, a daily intranasal corticosteroid like fluticasone or mometasone will blunt the response more reliably than any oral antihistamine. The difference matters because oral antihistamines dry everything out systemically. Intranasal steroids act locally. The onset is slower, usually three to five days for full effect, but the side effect profile is dramatically better. Non-allergic rhinitis, also called vasomotor rhinitis, is the category most people never hear about and it is exactly the one that frustrates doctors the most. The nerves in your nasal passages overreact to temperature changes, strong smells, spicy food, humidity shifts, or even stress. The mucus is watery. The nose runs. Allergy tests come back negative. The treatment here is different. Ipratropium bromide nasal spray is the go-to. It is an anticholinergic that directly blocks the glandular secretion reflex. It does nothing for inflammation. It stops the drip. My own experience with this was borderline. I developed a chronic post nasal drip in my late twenties that resisted every over-the-counter treatment. The pattern was obvious but never consistent enough to be allergies. Hot showers triggered it. Walking outside in cold air triggered it. Eating soup triggered it. Ipratropium 0.03% twice daily cut the symptom time by roughly eighty percent within a week. That was the first time in two years I went more than a day without constant throat clearing.
Acid reflux is the third major category and the one people miss most often. Laryngopharyngeal reflux, sometimes called silent reflux, sends stomach acid up to the very back of the throat. The tissue there reacts by producing thick, sticky mucus as a protective mechanism. You do not need heartburn to have this. Most patients with LPR report zero classic reflux symptoms. The post nasal drip sensation is frequently the only sign. If you have tried every nasal spray and rinse with minimal relief, a trial of a proton pump inhibitor for eight to twelve weeks is reasonable. Omeprazole twenty milligrams taken thirty minutes before breakfast. If the drip improves, the source was the throat, not the nose. Chronic sinusitis involves thick discolored mucus, facial pressure, reduced sense of smell, and symptoms lasting longer than twelve weeks. The irrigation approach works best here. A neti pot or squeeze bottle with distilled or boiled water and a pre-mixed saline packet. The volume matters. Small amounts do not reach the posterior nasopharynx where the drip accumulates. You need at least two hundred forty milliliters per nostril to get meaningful clearance. Doing this once daily for two weeks followed by maintenance three times a week is the typical protocol. Add a topical steroid spray after the rinse, not before. Rinsing first clears the debris so the medication can contact the actual mucosal surface instead of sitting on top of accumulated mucus. Environmental dryness is the simplest and most overlooked cause. Indoor heating in winter drops relative humidity to below twenty percent in many homes. The nasal mucosa responds by overproducing mucus to compensate for the dryness. A humidifier set to around forty-five percent relative humidity often resolves the problem completely. I have seen people spend hundreds on sprays and rinses only to fix it with a four-dollar hygrometer and a bedroom humidifier.
Get the Full Details

There is a structural issue that falls outside these categories. A deviated septum or enlarged turbinates can create turbulent airflow that irritates the posterior nasal passage continuously. This does not respond to medications. An ENT evaluation with nasal endoscopy will show it clearly. Turbinate reduction or septoplasty addresses the root cause. Nobody needs surgery for this, but it is important to know the option exists when conservative treatment fails after six months. The biggest mistake people make is treating every symptom with the same generic approach. Saline rinse. Antihistamine. Decongestant. Repeat. This works initially because it addresses the most common causes. When it stops working, people escalate to stronger decongestants, which create their own problems. Oxymetazoline spray used beyond three days causes rebound congestion that is nearly impossible to quit without medical support. The rebound makes the drip worse than it started. Do not use it longer than prescribed. If you want a practical diagnostic sequence, do this in order. Try daily saline irrigation with proper technique for fourteen days. If no improvement, add a daily intranasal corticosteroid for another fourteen days. If still no improvement, evaluate for reflux and consider an eight-week PPI trial. If all three fail, see an ENT for endoscopic evaluation. Most people never make it past step one. That is why the condition feels so persistent. The wrong treatment gets tried for years while the actual cause goes unexamined.
The mucus will not stop overnight. Nasal steroid sprays take about five days to reach peak effect. Ipratropium works within hours but you need consistent twice-daily use. Reflux treatment takes weeks. Patience with the protocol is more important than switching treatments every few days. Give each intervention at least two weeks before deciding it is not working.