The Mechanics of Breathing, Plain and Simple
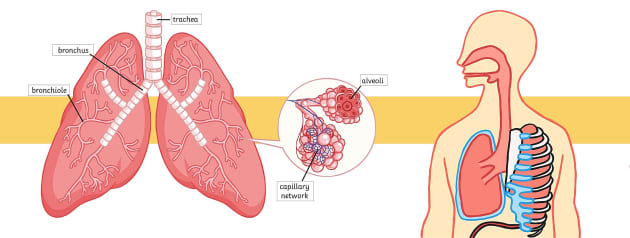
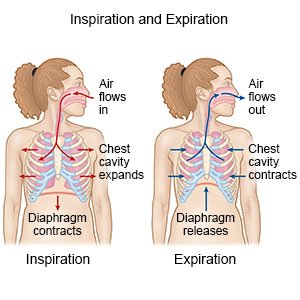
Most people don't think about their lungs unless something goes wrong, which is probably for the best. Breathing is an automatic process controlled by the brainstem, specifically the medulla oblongata and pons. These areas monitor carbon dioxide levels in your blood and adjust your breathing rate accordingly. You're not consciously telling yourself to breathe right now. It's happening regardless. When you inhale, your diaphragm contracts and moves downward. The external intercostal muscles between your ribs also contract, pulling your rib cage upward and outward. This creates negative pressure inside your thoracic cavity. Air rushes in to equalize that pressure. The air travels through your trachea, down your bronchi, and into smaller and smaller branching tubes until it reaches the alveoli. Those are tiny grape-shaped sacs where the actual gas exchange happens. Each lung contains roughly 300 to 500 million alveoli, giving you a total surface area of about 70 square meters. That's roughly the size of a tennis court packed inside your chest.
How Does Your Lungs Work During Gas Exchange
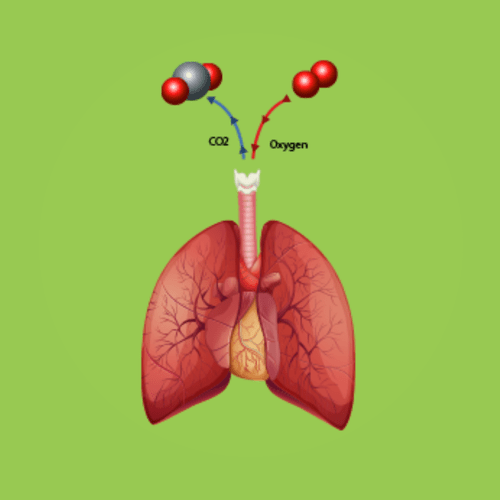
Here's where it gets specific. Oxygen diffuses across the alveolar membrane into the capillaries surrounding each sac. Carbon dioxide moves in the opposite direction, from your blood into the alveoli, to be exhaled. This process relies on partial pressure gradients. Oxygen moves from areas of high concentration to low concentration. The gradient is maintained because blood flowing through the pulmonary capillaries is constantly being replaced with deoxygenated blood from your heart. If that gradient breaks down, gas exchange slows or stops entirely. I worked with a respiratory therapist for a few years and saw plenty of cases where people misunderstood how their lungs actually function. One common mistake I encountered involved patients who thought deep breathing exercises were primarily about taking in more oxygen. They'd sit and gasp aggressively, expecting immediate relief from anxiety or fatigue. The real benefit comes from prolonged exhalation, which activates the parasympathetic nervous system. A slow exhale signals your body to downshift. The inhalation is only half the equation. Most people spend more time inhaling than exhaling when they're stressed, which keeps their sympathetic nervous system engaged and maintains elevated cortisol levels throughout the day. Another thing people get wrong is the role of mucus in your respiratory tract. Your airways produce about 100 milliliters of mucus every day. That mucus traps particles, bacteria, and viruses. Cilia, the tiny hair-like structures lining your airways, sweep that mucus upward toward your throat where you swallow it unconsciously. Stomach acid handles whatever gets caught. Smokers destroy those cilia over time, which is why chronic coughing develops. The mucus just sits there because nothing is moving it anymore.
What Actually Limits Lung Capacity
Vital capacity is the maximum amount of air you can exhale after a maximal inhalation. For a healthy adult male, this averages around 4.8 liters. Total lung capacity is higher because residual volume, the air that remains in your lungs after maximum exhalation, is typically about 1.2 liters. You can never fully empty your lungs. That residual air keeps the alveoli inflated so they don't collapse onto each other. Lung capacity decreases with age regardless of whether you exercise. Starting around age 35, your elastic recoil diminishes slightly. Your chest wall becomes less compliant. The diaphragm weakens a bit. These are normal changes. Smoking accelerates them significantly. Studies show smokers lose lung function at roughly twice the rate of non-smokers, independent of age-related decline. There's also a limitation that most people overlook. Your lungs aren't the primary limiting factor in aerobic performance for healthy individuals. Cardiovascular output, specifically how much blood your heart can pump per minute, is usually the bottleneck. Training your lungs directly produces minimal gains in endurance. Training your heart and blood vessels does. This is why altitude training works differently than you'd expect. At altitude, the problem isn't your lungs failing to absorb oxygen. It's that your blood has fewer red blood cells relative to the oxygen available, and your heart has to work harder to deliver what it has.
Get the Full Details
Common Problems and What Actually Helps
Asthma is one of the most misunderstood conditions I've encountered in clinical settings. People assume it's purely a lung problem. It's actually an inflammatory condition affecting the airways. The bronchial tubes become hypersensitive and constrict in response to triggers. Inflammation causes swelling and excess mucus production. The obstruction is in the passages, not the alveoli themselves. This distinction matters for treatment. Anti-inflammatory medications like corticosteroids address the root cause. Rescue inhalers like albuterol only provide temporary relief by relaxing the smooth muscles around the airways. They don't reduce inflammation. Pneumonia is another condition where the mechanics change entirely. Fluid or pus fills the alveoli instead of air. Gas exchange becomes severely compromised because the oxygen can't reach the capillary membrane. The lungs themselves aren't damaged permanently in most cases, but the filling process reduces the effective surface area dramatically. A severe pneumonia case can drop your functional alveolar surface area by half or more until the infection clears. I once had a patient who was convinced that certain breathing devices could "retrain" his lungs to work better. The device was basically a resistance trainer for your inhalation muscles. It made him stronger at inhaling, which isn't really a limitation for anyone with healthy lungs. The diaphragm is already working efficiently. Adding resistance doesn't translate to better oxygen uptake or improved exercise performance. It just built up his accessory breathing muscles, which can actually create tension and reduce diaphragmatic efficiency. I recommended he focus on diaphragmatic breathing practice instead, where the goal is smooth, full exhalations rather than forceful inhalations. His resting respiratory rate dropped from about 18 breaths per minute to 12 within a few weeks. That's a meaningful change that came from coordination, not strength.
Practical Takeaways
If you want to support your lung health, the evidence points to a few straightforward actions. Don't smoke. Avoid secondhand smoke when possible. Maintain cardiovascular fitness through regular aerobic exercise. Manage environmental exposures like dust, chemicals, and pollution where you can. If you have a chronic respiratory condition, follow your treatment plan consistently rather than waiting for symptoms to escalate. Your lungs will continue working automatically for decades unless you interfere with that process through smoking, significant pollutant exposure, or untreated disease. They're designed to operate without conscious attention. Paying attention only becomes necessary when something is already broken.