The Problem With Most Cardiovascular Documentation
I spent about six years working in cardiology clinics before moving into documentation compliance, and the thing that consistently got people in trouble wasn't missing data. It was writing data in a way that couldn't be defended when a reviewer looked at it three months later. Most nurses, PAs, and even some attending physicians document cardiovascular assessments the same way they do everything else. They fill out the chart because they have to, not because they're building a record that actually stands up to scrutiny. The difference between a solid cardiovascular assessment note and one that gets flagged usually comes down to a few specific choices. I am going to walk through how to do this properly, including the exact phrasing, the structure that works, and the common traps I see people fall into repeatedly.
How To Document Cardiovascular Assessment
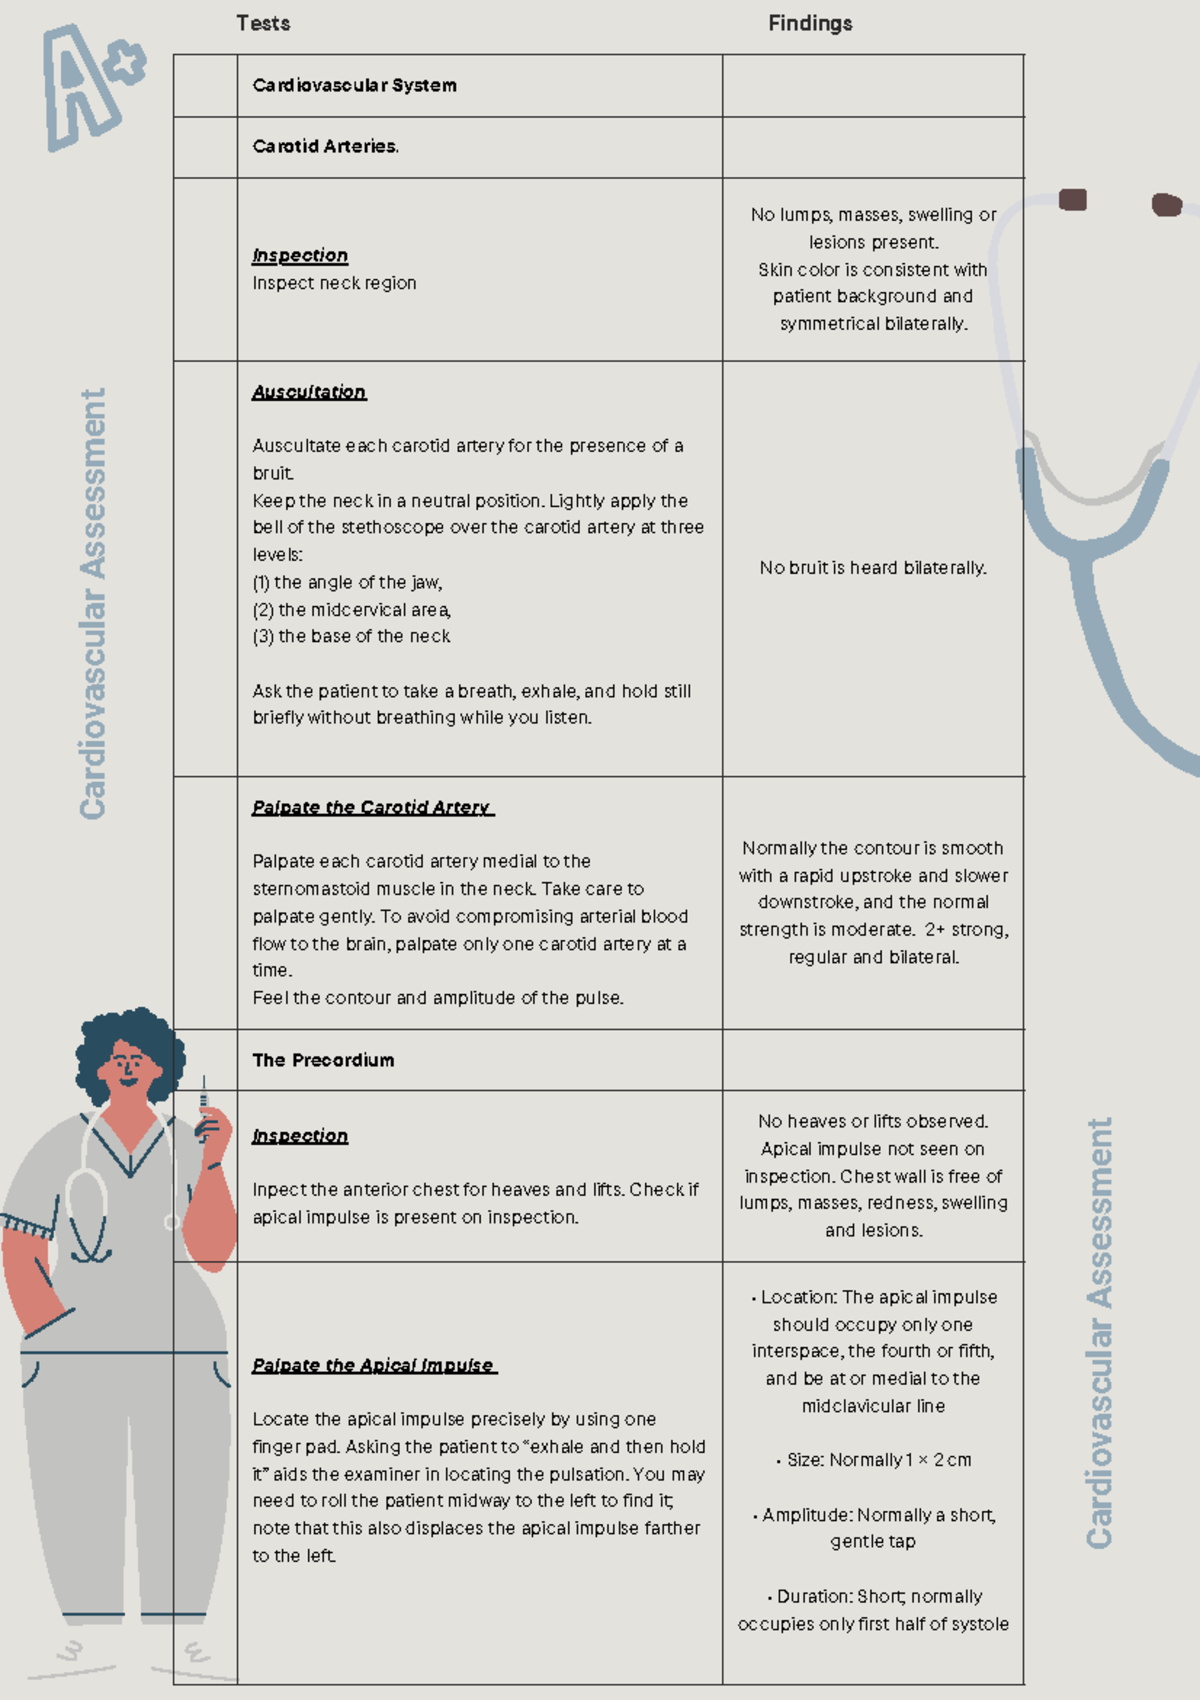
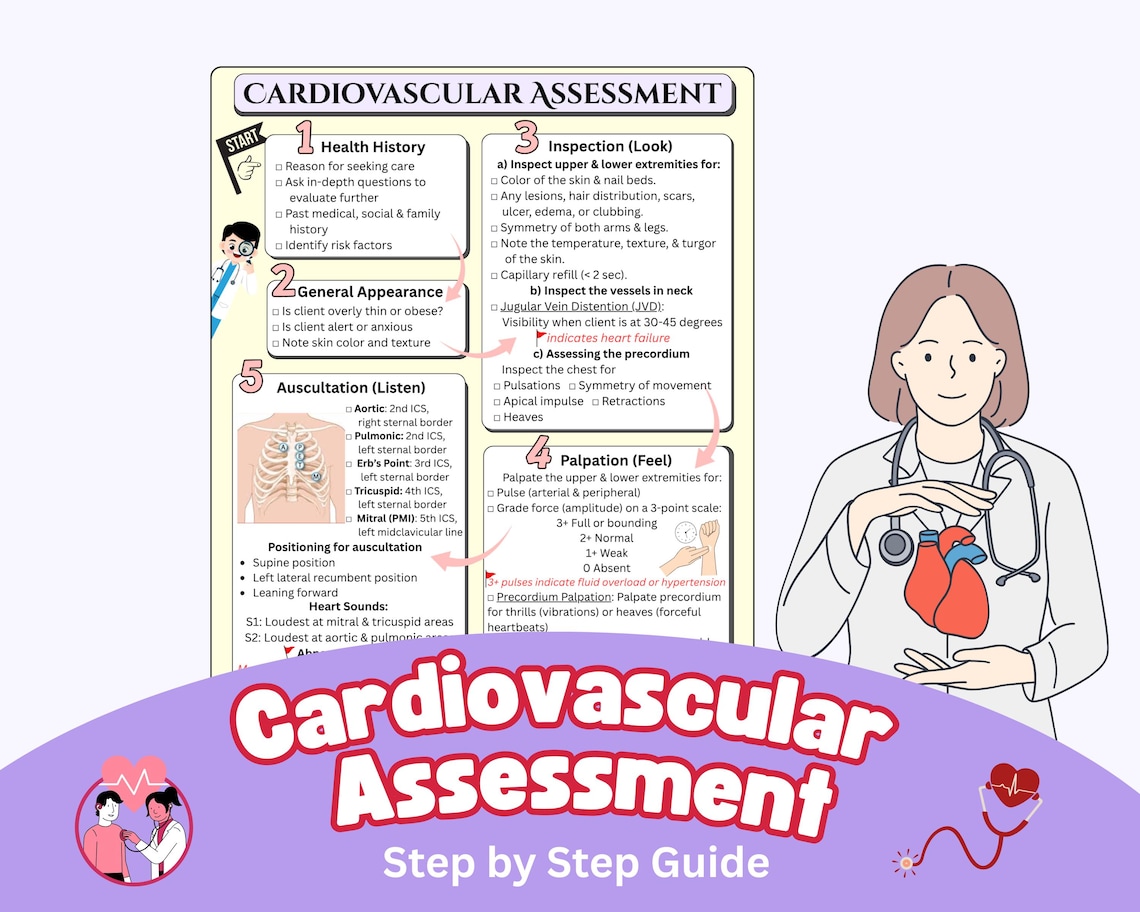
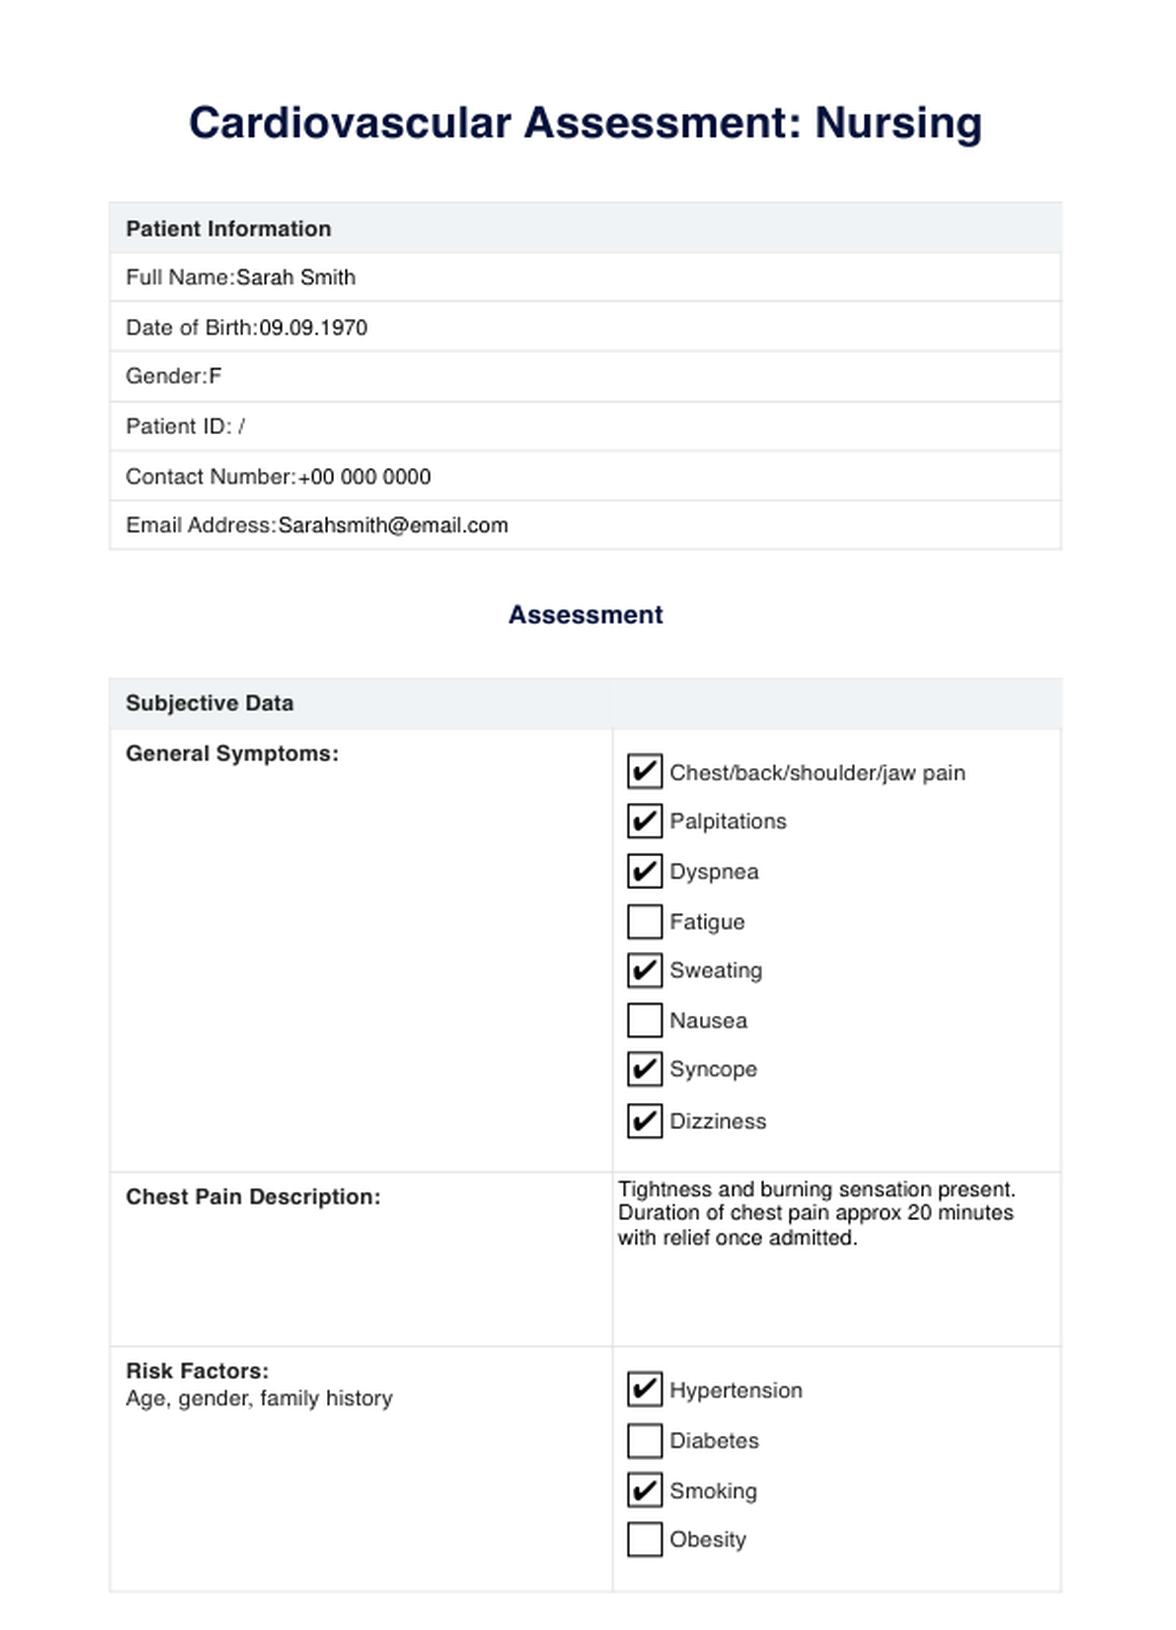
Start with the basics. Every cardiovascular assessment note needs a clear timeline, a complete set of vital signs captured at the right intervals, and a systematic physical exam walkthrough. But here is the part most people skip: documenting your clinical reasoning. Writing that the patient has a 2/6 systolic murmur is not enough. You need to specify where you heard it loudest, whether it radiated, what maneuvers changed its intensity, and why you documented it that way. A reviewer needs to see your thought process, not just your findings. The structure I use and recommend breaks down into five sections. The first is the chief complaint and history of present illness, which should include onset, duration, character, aggravating and alleviating factors, and radiation. This is the standard OLDCARTS framework, but most people treat it like a checkbox exercise. Do not. The way you phrase these details often determines whether the note looks like a genuine assessment or a form you filled out while standing in the doorway. The second section covers past medical history with specific cardiovascular relevance. This means listing hypertension with the number of years diagnosed, documented ejection fractions from prior echocardiograms, stent placements with dates and locations, and medications with doses. Vague entries like "history of heart problems" will get your note sent back every time. Write "hypertension for 12 years, last known BP 148 over 92 on amlodipine 10 mg daily." That is the level of specificity that actually works.
The third section is the review of systems, focused on cardiovascular symptoms. Dyspnea on exertion, orthopnea, paroxysmal nocturnal dyspnea, chest pain characteristics, palpitations, syncope, edema, claudication. Document each one as present or absent with a brief qualifier. "Absent" without any context looks like you did not ask. "Patient denies dyspnea on exertion" is better. "Patient denies dyspnea on exertion; reports climbing two flights of stairs without shortness of breath" is the kind of detail that separates adequate from excellent documentation. The fourth section is the physical exam, and this is where most documentation falls apart. You need to document cardiac rhythm, heart rate, point of maximal impulse, peripheral pulses, capillary refill, jugular venous pressure, lung sounds if relevant, and edema if present. Be specific about pulse quality. "2+ radial pulses bilaterally" tells the reviewer something useful. "Pulses present" tells them nothing and gets you questioned during any audit. The final section is the assessment and plan. This is where your clinical judgment lives. State your impression of the patient's cardiovascular status, reference the evidence you found, and lay out your plan with specific, measurable actions. If you are not ordering further workup, say why. "No acute intervention indicated at this time; patient asymptomatic with stable vitals and no new murmurs" is infinitely better than "continue current management" with nothing behind it.
Get the Full Details

I want to share a specific example from my own practice that illustrates how quickly documentation can go sideways. A patient came in for a routine follow-up on atrial fibrillation. The provider had prescribed rate control and anticoagulation and checked in quarterly. During one visit, the patient reported mild fatigue but no chest pain or palpitations. The provider documented "rate controlled, no acute issues, continue metoprolol." Six months later, the patient presented with a stroke. The retrospective review of the documentation found that nobody had documented a reassessment of the CHA2DS2-VASc score at the most recent visit, nobody had checked a current INR or renal function, and the fatigue symptom was recorded without any attempt to correlate it with possible low cardiac output or medication side effects. The note was legally adequate in format but clinically hollow. It would not have survived a malpractice deposition. After that case, I started requiring a structured cardiovascular risk reassessment template for every follow-up visit, and it cut our documentation deficiencies by roughly seventy percent over the next year. There are some counter-intuitive aspects to cardiovascular assessment documentation that beginners consistently miss. The first is that more detail is not always better, but less detail is almost always worse. The key is relevant detail. Writing "heart regular rate 72" is fine for a well patient in a low-acuity setting. Writing the same thing for a patient with a history of heart failure who just lost twelve pounds in three days is negligent. Context determines the level of detail required, and most documentation errors come from applying a one-size-fits-all approach to a highly variable patient population. The second counter-intuitive point is that negative findings deserve as much documentation weight as positive ones. If a patient has a history of murmur but you document no new murmur without specifying the grading system or location, you are leaving a gap. Documenting "no new murmur; previously grade 2/6 holosystolic murmur best heard at apex" closes that gap and shows continuity of care across multiple visits.
Another practical nuance involves the timing of vital signs documentation. Many providers take blood pressure in both arms during a first cardiovascular assessment and then only document one. If there is a significant inter-arm difference, you must document both values and the clinical implication. I have seen notes where a sixteen millimeter mercury difference was entirely omitted, and that omission mattered when the patient later developed a subclavian artery stenosis. Document the number. Then document what you did with that number. Let me address the limitations and scenarios where standard documentation approaches completely fail. The first limitation is electronic health record templates that force you into predefined fields. These templates often strip away nuance. You might check a box for "normal heart sounds" when the reality is more complex. The workaround is to use the free-text comment field for anything that does not fit the template. It takes twenty seconds and it creates a defensible record. The second limitation is high-volume clinics where documentation time is genuinely constrained. If you are seeing twelve patients in two hours, you cannot write a novel for each cardiovascular assessment. In those settings, the priority is ensuring that every positive finding and every abnormal vital sign is documented with full specificity. Normal findings can be abbreviated, but abnormal findings require complete documentation every single time. A single vague entry about an abnormal heart sound can become the focal point of a complaint investigation. The third limitation is documentation for patients with limited health literacy or language barriers. Standard cardiovascular terminology will not translate across language barriers. If you document "orthopnea" for a patient who speaks English as a second language and you never verified their understanding, that documentation is incomplete. Use plain language descriptions in the note alongside the medical terminology. "Patient reports needing three pillows to sleep without shortness of breath" alongside "orthopnea" serves both the clinical record and any future interpreter review.
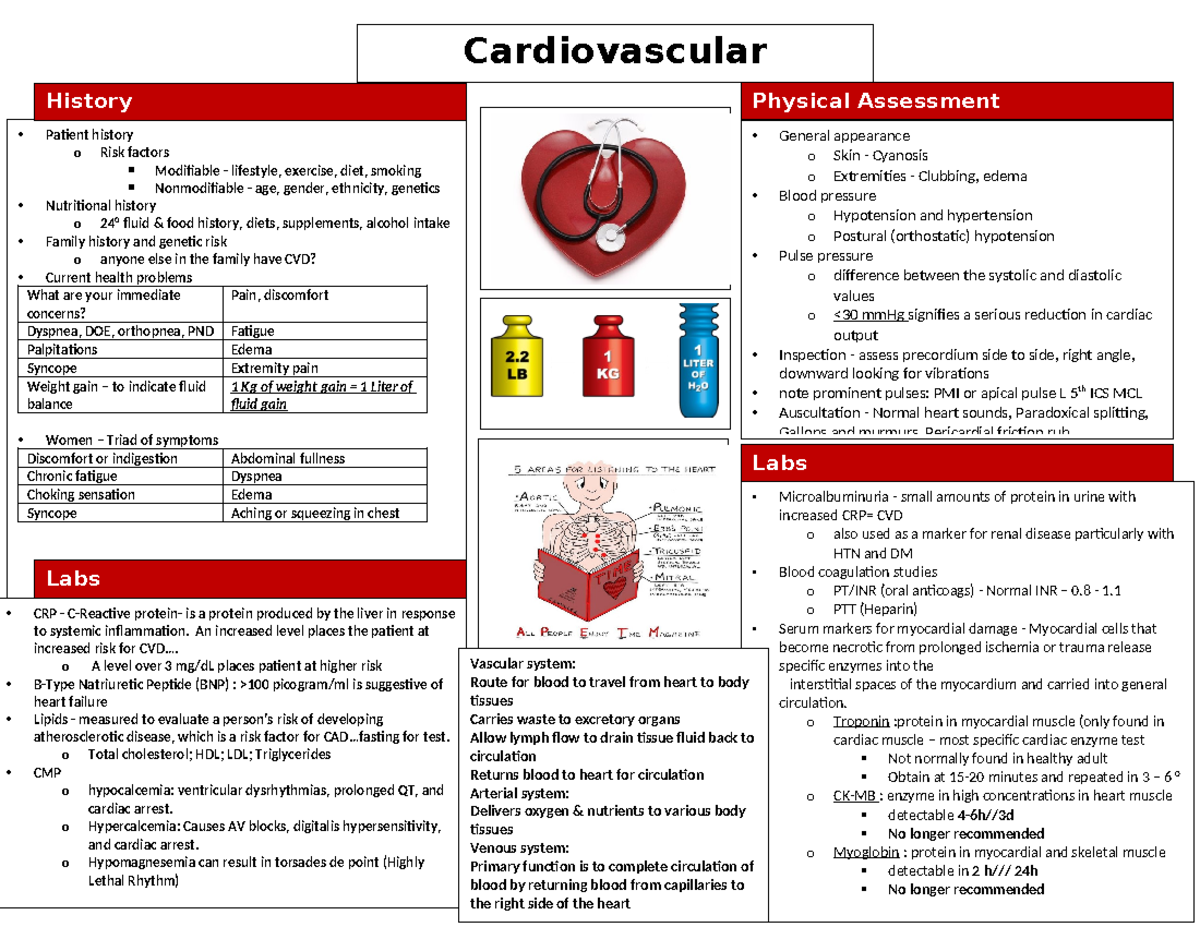
For practitioners who want a structured starting point, I recommend creating a personal documentation checklist that covers the five sections I outlined above. Do not rely on whatever template your institution provides without modifying it. Templates are designed for the lowest common denominator and they will not capture the nuances that matter in complex cardiovascular cases. Build your own version, refine it based on what gets you in trouble and what protects you, and stick with it. The time investment for a thorough cardiovascular assessment note in a stable outpatient setting is approximately eight to twelve minutes. For an acute or inpatient presentation, it is closer to fifteen to twenty minutes. Anything significantly faster than those ranges suggests you are skipping documentation elements that matter. Anything significantly slower suggests you are including irrelevant detail. The sweet spot is documentation that is complete, specific, and defensible without being exhaustive in the wrong directions. I also want to mention a common pitfall involving medication reconciliation during cardiovascular assessment. It is not enough to list the medications a patient takes. You need to document that you verified the medication list against the patient's actual pharmacy fills or pill bottles, noted any discrepancies, and addressed those discrepancies in the plan. "Medications reviewed and reconciled" is insufficient. "Medication list verified against patient's home supply; lisinopril dose reduced from twenty milligrams to ten milligrams based on recent potassium of 5.4; patient counseled on this change" is the level of documentation that protects you and the patient.
Finally, the documentation of patient education and shared decision-making is an area that almost nobody does consistently but everyone should. If you discussed statin therapy with a patient who declined, documented the discussion with the specific risks you conveyed and the patient's stated reason for decline is essential. If you ordered a stress test and the patient did not complete it, documenting the attempt and the outcome matters. These elements do not add much time to your documentation but they dramatically improve the defensibility of your clinical record.