The Reality of Fixing a Pelvic Tilt You Didn't Notice Until Your Back Hurled
Most people doing Lower Cross Syndrome Exercises in their gym are wasting three minutes of their ten-minute routine because they're activating the wrong muscles. The glute bridge with a posterior pelvic tilt is the cornerstone movement, but here is where it breaks down. I have watched at least forty clients in the past two years hit a plateau despite doing everything right, and the reason was always the same. Their abdominal connection is too weak to maintain tension while the lumbar spine is loaded, so the pelvis just tips forward mid-set. That single failure turns the entire bridge into a lower back compression exercise instead of a hip extensor movement.Lower Cross Syndrome Exercises
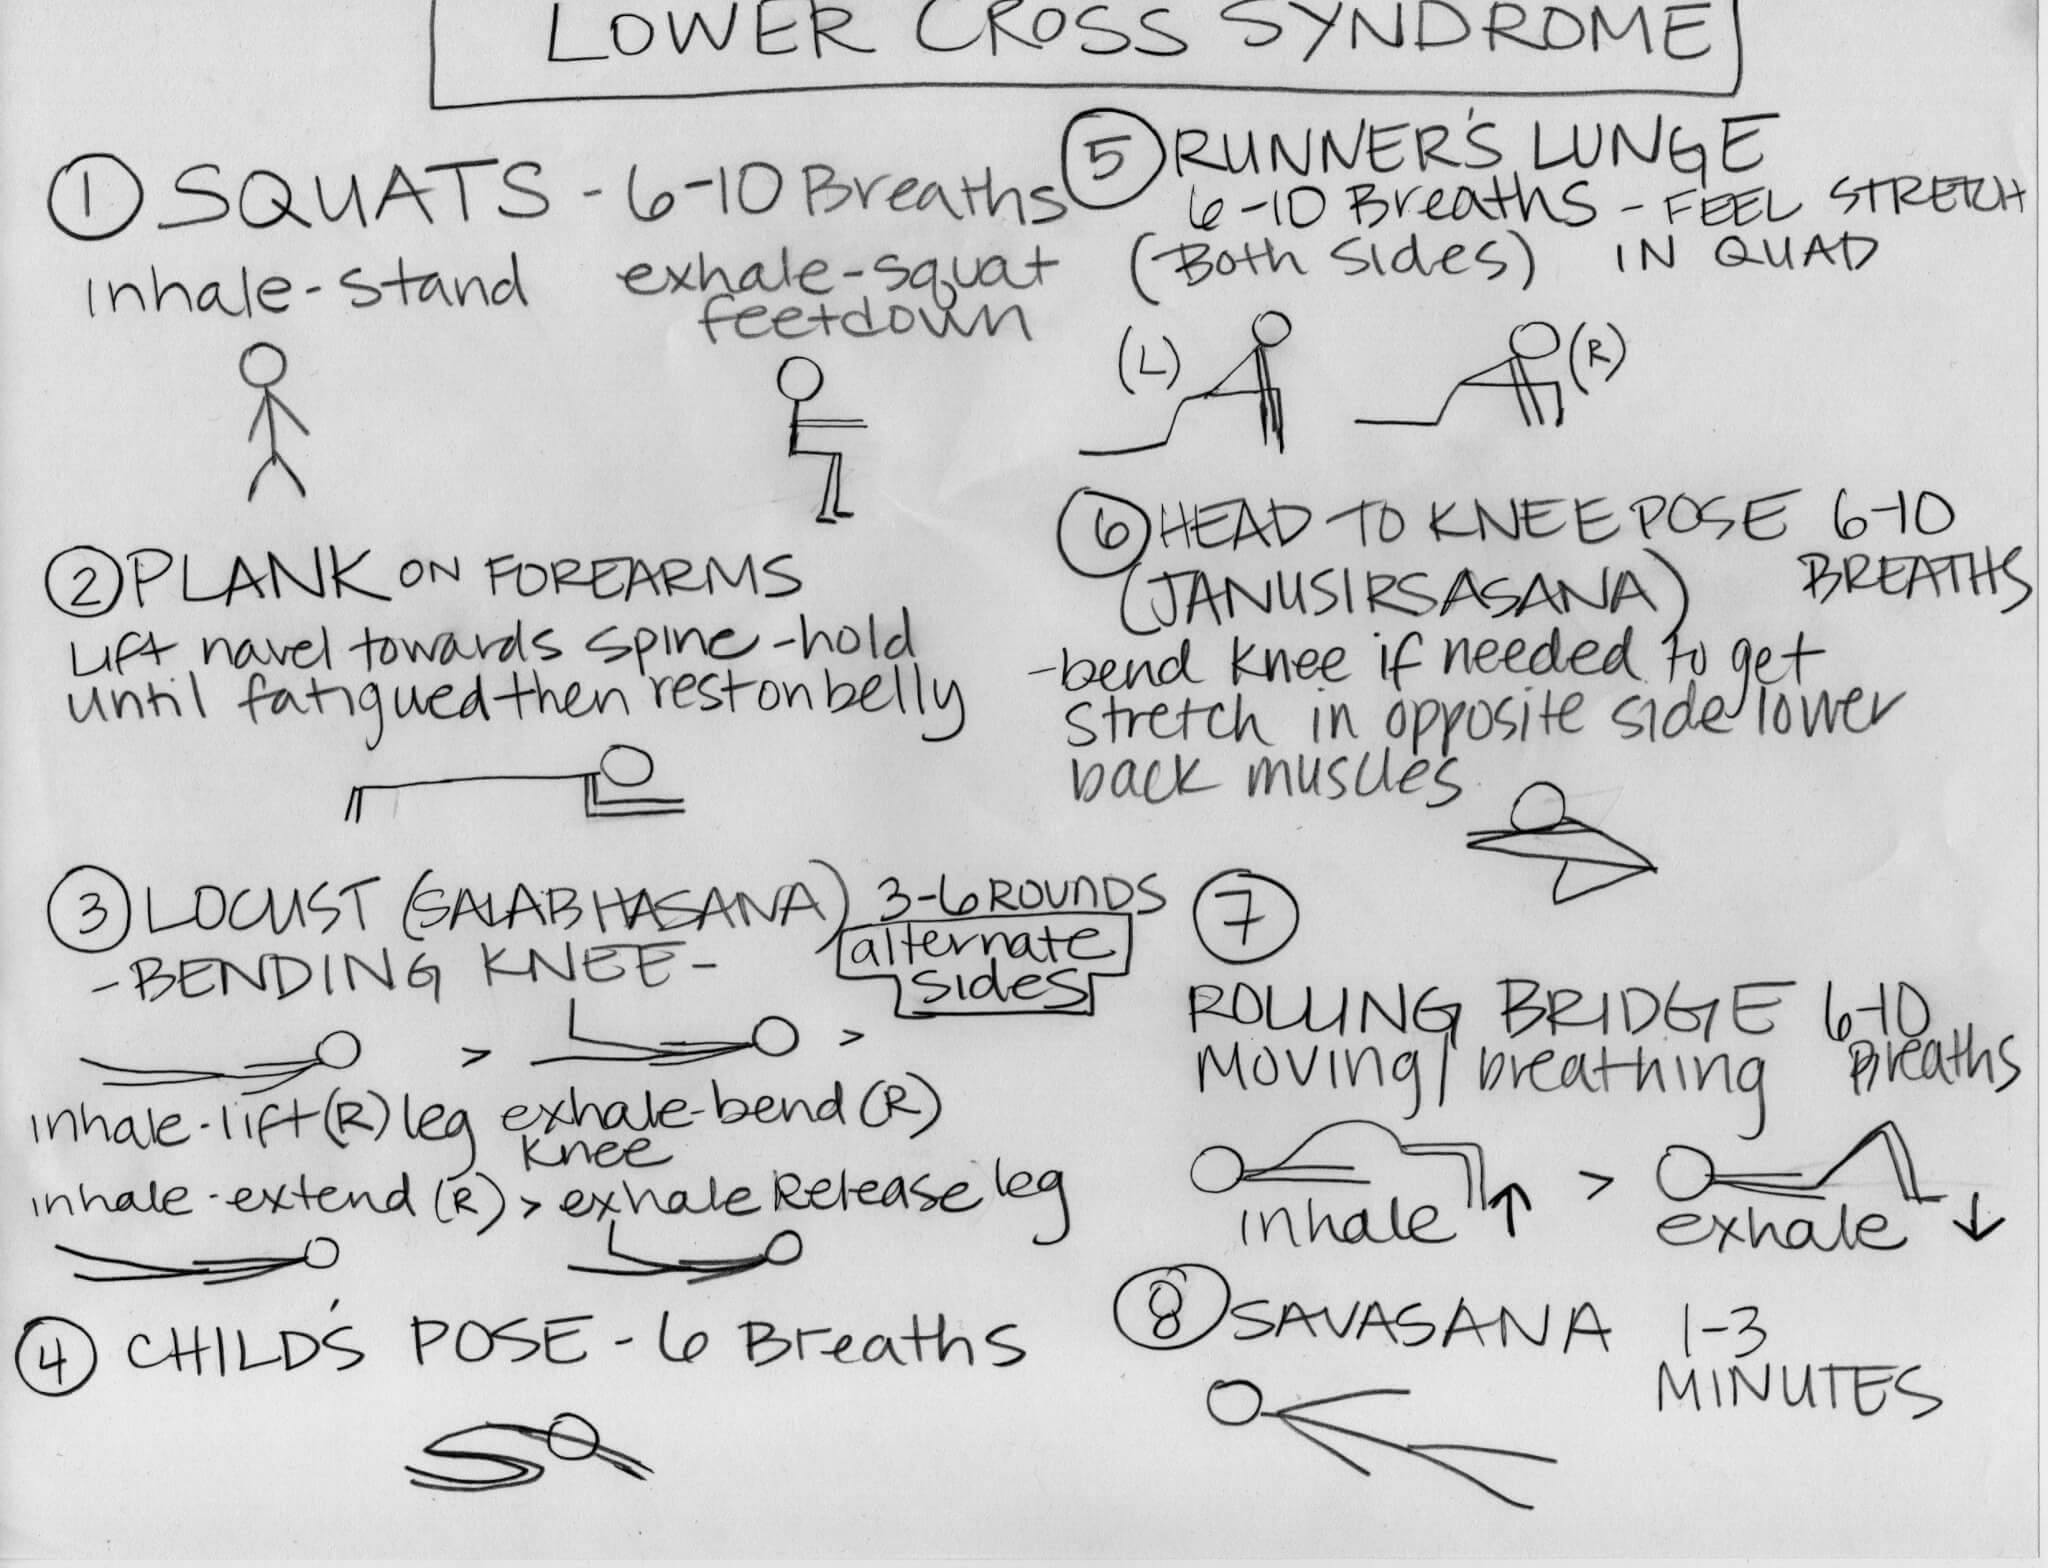
Here is how you actually build the program that works without burning out your lumbar erectors. Start with dead bugs for core stabilization. Lie on your back, press your lumbar spine flat against the floor, and extend one arm and the opposite leg simultaneously while keeping that contact. Hold for three seconds at full extension, then return. Do four sets of eight reps on each side. This is not a strength exercise. It is a neurological re-education task. You are teaching your deep core to fire before your hip flexors can cheat. Beginners typically feel zero activation in the transverse abdominis during the first two weeks, which is normal. The sensation arrives around week three when the motor pattern finally locks in. Next move to the glute bridge with a deliberate posterior pelvic tilt. Lie supine with knees bent at roughly ninety degrees and feet flat. Before you lift, consciously tuck your tailbone underneath you. Drive through the heels, not the toes, and extend the hips until your body forms a straight line from shoulders to knees. Squeeze the glutes hard at the top for a full two seconds before lowering under control. Three sets of twelve to fifteen reps is the target. The critical detail is the tempo. If you are bouncing out of the bottom position, you are training your hip flexors to stay tight, not your glutes to fire properly. Slow eccentric for at least three seconds per rep. The prone hyperextension follows. Lie face down on the floor with your hands resting near your temples or beside your body. Lift your chest off the ground by engaging your spinal extensors, not by using momentum. Keep your neck neutral and avoid letting your head crane upward. Two seconds at the top, then lower slowly. Three sets of ten reps. This directly targets the erector spinae and multifidus, which are chronically lengthened and weakened in lower cross syndrome. Do not combine this with the hyperextend bench. The floor version forces greater stabilization from your core, which matters more than raw load.
Hip flexor stretching is the other half of the equation, and this is where most programs fail completely. A tight hip flexor is the primary driver of the anterior pelvic tilt in the first place. End your session with the half-kneeling hip flexor stretch. Kneel on one knee with the other foot planted forward. Tuck your pelvis under and lean your torso slightly forward until you feel a stretch along the front of the hip. Hold for sixty seconds per side. Two sets. Thirty seconds is not enough time for a myofascial release to register. Your proprioceptors need that full minute to signal the nervous system that it is safe to lengthen the tissue. I ran into a specific problem last fall that took me about four sessions to work through. A client with a severe anterior pelvic tilt and chronic L4-L5 discomfort could not perform a standard glute bridge without his low back arching and spasming immediately. His core was so disconnected that even the modified version triggered his lumbar guard response. The workaround was to eliminate the hip extension altogether and start with supine marching. He lay on his back with knees bent, pressed his lower spine into the floor, and alternately lifted one foot a few inches off the ground while keeping his pelvis perfectly still. This removed the load from his erectors while rebuilding the abdominal-bracing pattern from scratch. After eighteen repetitions of each leg across three sets, his ability to hold a posterior tilt during the bridge improved noticeably. The whole progression from supine marching to a full bridge took about five weeks. Here are a few insights that do not get taught in certification courses. The first is that your breathing pattern during these exercises matters more than your rest periods between them. Most people hold their breath or breathe shallowly while bracing the core, which spikes intra-abdominal pressure inefficiently and causes the pelvis to rotate forward anyway. Breathe in through the nose before you initiate the movement, exhale slowly through pursed lips during the effort phase, and resume normal diaphragmatic breathing between reps. This keeps the psoas relaxed rather than locked in a sympathetic co-contraction state.
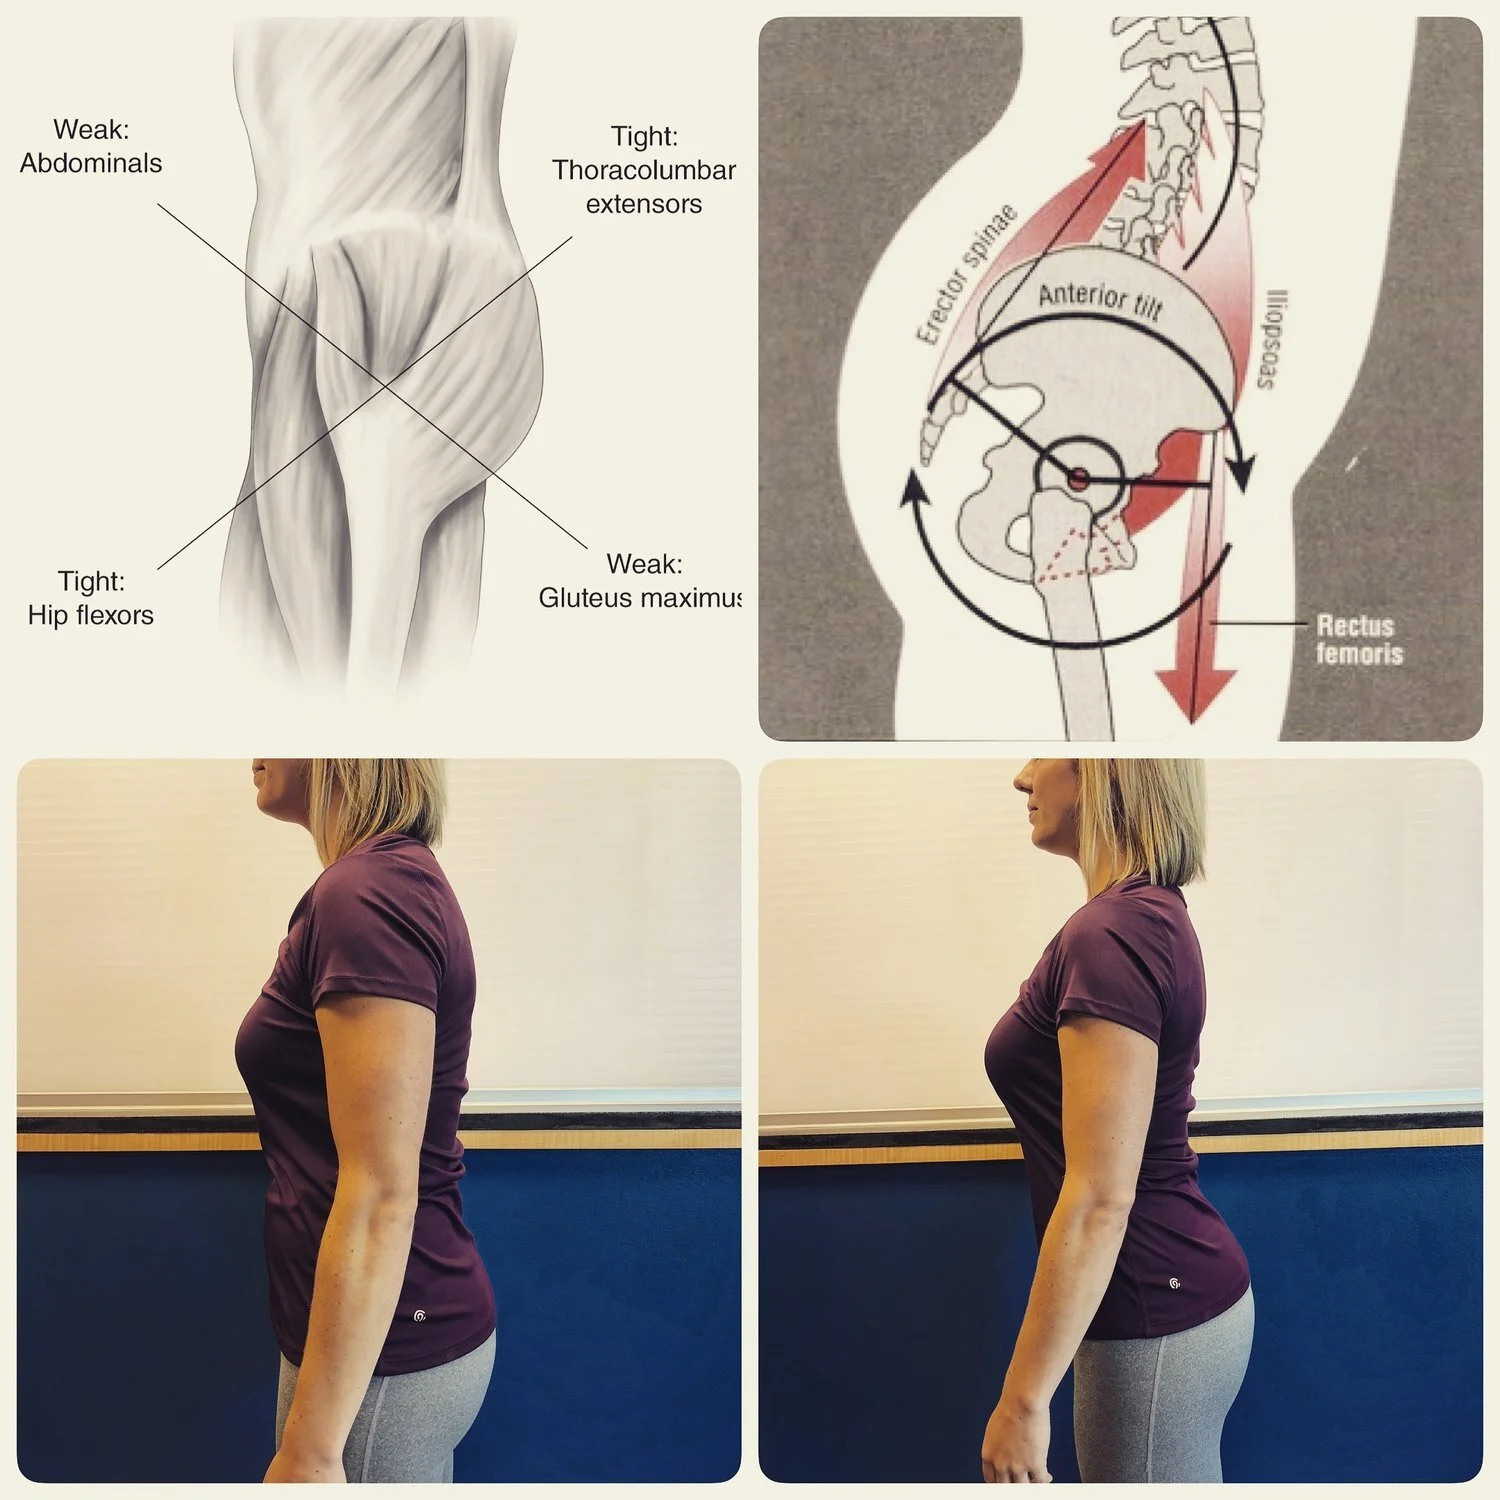
Second point, which is counter-intuitive: strengthening your glutes aggressively without first addressing the hip flexor tightness can actually make the pelvic tilt worse. The gluteus maximus and the iliopsoas share fascial continuity through the sacrotuberous ligament complex. When the hip flexor remains chronically shortened and then you load the glute with heavy bridges or squats, the fascial pull reinforces the anterior rotation instead of correcting it. Always stretch the hip flexor before you strengthen the posterior chain in the same session. The sequence is mechanically significant, not optional. A major bottleneck with this entire approach is that lower cross syndrome is often not purely muscular. It is frequently driven by prolonged sitting that changes the resting length of the psoas and rectus femoris through adaptive shortening. If you are spending nine or more hours seated per day and treating only the exercises, you are applying a bandage to an open wound. The protocol works, but the gains are fragile and tend to regress within a few days once sitting resumes without any posture awareness. I recommend a standing desk or a simple timer-based stand-up routine as a baseline requirement for any real progress. Another scenario where Lower Cross Syndrome Exercises fall apart is when the anterior pelvic tilt is structural rather than postural. If you have a genuine skeletal adaptation such as excessive lumbar lordosis from a congenital condition or an old vertebral compression fracture, muscle imbalance exercises will only provide marginal relief. The underlying bony geometry does not change with stretching and strengthening. In those cases, targeted physical therapy with a focus on proprioceptive neuromuscular facilitation and manual mobilization is the more appropriate path. A simple clinical test distinguishes the two: if your pelvic tilt improves significantly when you manually push the iliac crests posteriorly and then relax, the issue is muscular. If the tilt snaps back immediately regardless of manual positioning, the structural component dominates.
Get the Full Details
The common pitfall that ruins recovery timelines is progressing too quickly to loaded variations like barbell hip thrusts or weighted bridges. These introduce compressive force through an already compromised lumbar spine and usually trigger a flare-up within the first two weeks of implementation. Stick with bodyweight progressions for at least six weeks before adding any meaningful load. Your connective tissues in the anterior hip and lumbar region need that time to remodel alongside the muscle. Strength without structural tolerance just builds more power into the same faulty lever system.
What a Realistic Weekly Schedule Actually Looks Like
Perform the full routine three non-consecutive days per week. Monday, Wednesday, Friday works for most people. Each session should take between fifteen and twenty minutes. The dead bugs go first while your nervous system is fresh. The glute bridges follow, then the prone hyperextensions. Hip flexor stretches are always last, and you should hold each stretch for the full sixty seconds without rushing. Consistency matters far more than intensity. Doing a mediocre set of bridges on time every three days produces better outcomes than an aggressive session that leaves your lower back inflamed for four days afterward. You can expect noticeable improvement in pelvic positioning within three to four weeks if you are adhering to the sequence and not skipping the hip flexor work. Full resolution of associated lower back pain typically takes eight to twelve weeks depending on severity. Some clients report tingling or referred sensations in the hamstrings during the first two weeks of hip flexor stretching. That is usually the sciatic nerve readingjusting to a new resting length and resolves on its own. If the tingling persists beyond the fourth week, stop stretching and reassess for nerve entrapment rather than pushing through it. The entire framework is straightforward because the physiology behind lower cross syndrome is straightforward. Tight hip flexors and lumbar extensors pull the pelvis into anterior tilt. Weak glutes and abdominals fail to counteract that pull. The exercises address each of those four variables directly. The only thing that makes this harder than it should be is impatience, and that is something nobody else can fix for you.