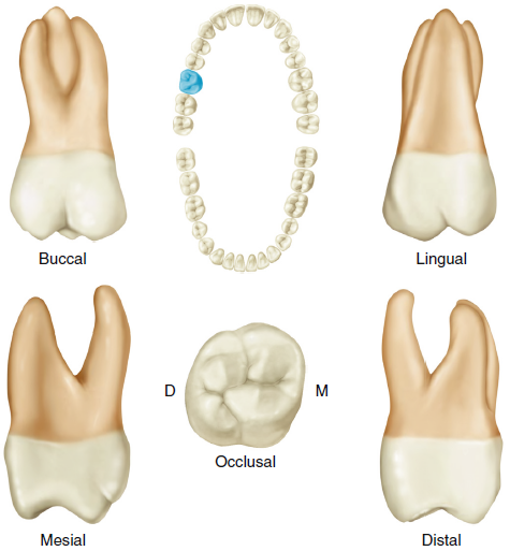
Working with the Maxillary First Molar
The maxillary first molar is the largest tooth in the permanent dentition and it shows up constantly in restorative work, endo, and oral surgery. I run into it every single week in the operatory. Understanding the anatomy properly saves time and prevents complications. Most errors come from rushing through the surface landmarks or ignoring the root configuration. This tooth typically has four cusps: the mesiobuccal, distobuccal, mesiolingual, and distolingual. The mesiolingual cusp is the largest and forms the central functional support. The oblique ridge connects the mesiolingual cusp to the distobuccal cusp and is a key landmark for occlusal cavity preparations. If you are prepping a Class II and you miss the oblique ridge orientation, you will weaken the tooth structure unnecessarily. The crown contours buccally and lingually. The buccal surface has two developmental depressions separating the two buccal cusps. On the lingual surface, the slope from the mesiolingual cusp is much more gradual. When you are looking at an extracted tooth, the cervical cross-section is roughly triangular with the base oriented toward the buccal side.
Root Configuration
Three roots. That is the rule, not the exception. The mesiobuccal root is the shortest and broadest of the three. It often has two canals. The palatal root is the longest, straightest, and usually has a single large canal. The distobuccal root is the smallest and most variable. It can be flattened mesiodistally and sometimes has a groove running down the root surface. I pulled a tooth last month where the distobuccal root had a severe apical curvature that was almost perpendicular to the long axis of the tooth. Standard instruments were not reaching the apex. I switched to pre-curved #25 K-files and worked in a stepping fashion. It added about ten minutes to the extraction but saved the patient from a surgical flap. If you are doing endo on these teeth, take a radiograph with a mesial angulation to separate the MB and DB roots visually. The overlap on a straight PA is misleading and causes missed canals.
Canal System Details
The maxillary first molar has a complex canal system that is not always obvious on imaging. The mesiobuccal root commonly contains two canals: MB1 and MB2. MB2 is located palatal to MB1 and can be hidden under the carious lesion or dentinal bridge. I have seen clinicians miss it on at least fifteen patients before they started taking CBCT scans. The MB2 canal orifice sits at approximately the 10 o'clock position when viewing the pulpal floor from the occlusal aspect. You need to remove the dentin shelf above the MB canal orifice with a round bur or ultrasonic tip to locate it properly. The palatal canal is usually straightforward. It runs nearly straight from the pulp chamber to the apex. But there is a pitfall here. The palatal root can have an accessory canal near the apex that exits on the interradicular surface. If you are doing apexification or regenerative procedures, this matters because instrument files alone will not clean it out. Irrigation with sodium hypochlorite and agitation using a side-vented needle helps reach those areas better than passively inserted files ever will.
Get the Full Details

Practical Identification Tips
If you need to determine which tooth you are looking at, check these markers first. The mesiobuccal cusp ridge is shorter than the distobuccal cusp ridge. The oblique ridge is prominent and runs diagonally across the occlusal table. The crown tilts lingually relative to the root axis, which means the cervical line bows more on the buccal side than the lingual side. When mounting an extracted tooth on a workbench, the root divergence angle is wide enough that all three roots spread apart significantly. This is useful information for surgical planning. If the roots are fused or the divergence is minimal, you are likely looking at a maxillary second molar, not a first molar. The first molar roots are distinct and usually well-separated at the cervix.
Common Mistakes to Avoid
One frequent error in cavity preparation is going too deep on the buccal side during Class II prep. The buccal pulp horn extends further apically than the lingual horns. If you are using a bur without proper depth control, you risk exposing the mesiobuccal pulp horn. Measuring the dentin thickness with a caliper before penetrating the pulp chamber saves time compared to dealing with a accidental exposure afterward. Another mistake involves restorative margin placement. The cervical curvature of the maxillary first molar is pronounced on the buccal surface. Placing a restoration margin in the concavity without proper isolation leads to contamination and bond failure. Use a rubber dam. It takes thirty seconds to set up and prevents salivary contamination that ruins the entire procedure. The anatomy can also present problems in orthodontic extraction cases. If you are removing maxillary first molars for space closure, be aware that the mesiobuccal root often has a bifurcation near the apex. This means the bone surrounding that root may be thinner. Applying excessive force during extraction can cause root fracture. Sectioning the tooth and removing the roots separately reduces the required force and decreases the risk of leaving root fragments behind.
Imaging Considerations
Standard bitewing radiographs show the crown anatomy well but compress the root structures into a two-dimensional plane. A periapical radiograph taken at a 20-degree mesial angulation separates the MB and DB roots adequately for most diagnostic purposes. For surgical planning or endodontic retreatment, a CBCT scan provides three-dimensional information that changes the treatment plan in roughly twenty percent of cases involving this tooth. When reading a radiograph, look for the triradicular appearance. Three distinct radiolucent lines indicate three separate roots. If you see only two radiopaque lines converging toward the apex, the third root is superimposed and you need a different angulation to resolve it. I use the SLOB rule to determine which root is which. Same Lingual, Opposite Buccal. It is reliable once you practice it a few times. Understanding Maxillary First Molar Anatomy is not just about memorizing labels. It is about knowing how the structures relate to each other in three dimensions and how they behave when you interact with them clinically. The differences between a successful outcome and a complication usually come down to whether you recognized the anatomy before you started working or whether you learned about it while something went wrong.