Getting a Business Plan For Assisted Living Facility Right
I spent three years running the financials for a 48-bed assisted living community in Ohio before handing it off to our operator. The first version I built had us projected at 82% occupancy in year one with room and board revenue that looked impressive on paper. It was wrong. We missed state-specific staffing ratios tied to census levels, underestimated the regulatory inspection timeline by six months, and didn't account for the fact that families don't move someone into assisted living during the first two weeks after a hospital discharge like we'd assumed. The revised model took us eight weeks to rebuild, but it actually matched reality. A business plan for this sector isn't really a pitch document. It's an operating manual that proves you understand how the money moves between residents, families, payers, and state regulators. Lenders care about one thing: can you cover debt service while you're breaking even on operations? Investors care about something different: what's the path to EBITDA that justifies their capital. The document has to serve both audiences without collapsing under contradictory assumptions.
What a Real Business Plan For Assisted Living Facility Actually Contains
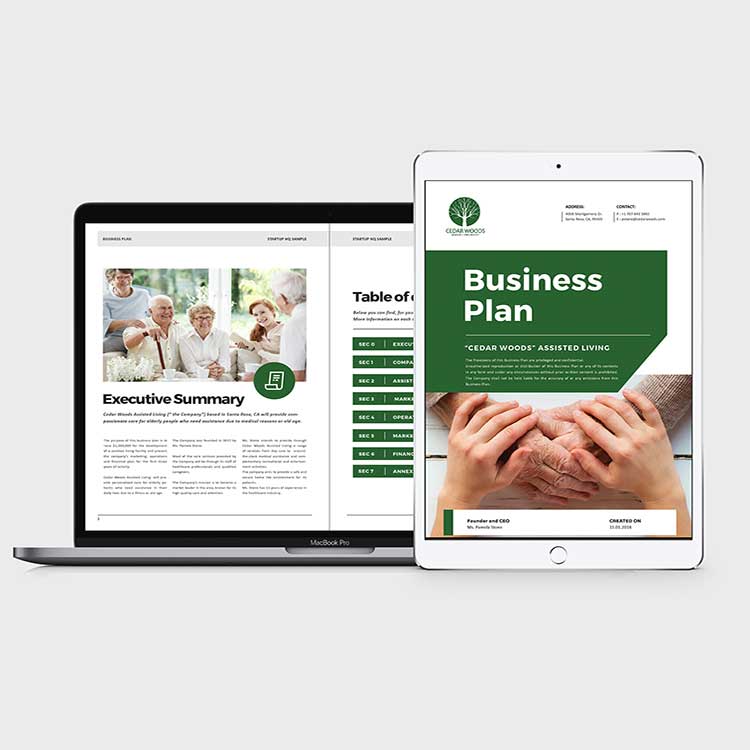
The core sections are fairly standard. Executive summary, market analysis, facility design and capacity, services and staffing model, regulatory compliance timeline, financial projections, and risk analysis. The trick is making each section specific enough that a bank underwriter or state licensing agency can't walk away confused. Market analysis needs more than county-level senior population data. You need sub-market analysis around transportation radius, competitor occupancy rates, and referral source density. Hospitals, rehab facilities, and adult protective services are where admissions come from, and mapping them within a 20-mile drive time is more useful than general demographic trends. One of my facilities sat two miles from a mid-size hospital but the referring case managers never sent anyone there. Turns out there was a road construction project that made the access route effectively impassable for ambulance transport during peak hours. We adjusted our marketing plan to target a different hospital system instead. Services and staffing model is where most plans fail. You can't just pick a number of nurses and call it done. Each state has its own minimum staffing requirements based on resident acuity and bed count. Florida requires different ratios than California. Minnesota ties staffing to census percentages. Your operating costs are 60 to 75 percent labor, and that percentage shifts as occupancy changes. I learned this the hard way when a client in Texas had us budget for a 24/7 RN presence that the state didn't require at 60 percent occupancy. That was $180,000 a year in unnecessary staffing cost that made the entire pro forma unbankable. We restructured to a licensed nurse on duty during core hours with an on-call RN arrangement, which brought the plan back into compliance with lender expectations.
Financial projections should run five to seven years. Year one through year three are the dangerous stretch. Start-up costs typically include license fees, construction or renovation, furniture and equipment, pre-opening marketing, working capital for payroll before admission revenue kicks in, and reserve funds for regulatory inspections. A 48-bed facility in a mid-cost market usually needs between $1.2 million and $2.5 million in total capital depending on whether you're building new or renovating an existing structure. You'll see lenders want a cash flow cushion of at least six months of operating expenses in the bank before they approve the loan.
Get the Full Details

The Operating Model Behind the Numbers
Revenue in assisted living comes from three buckets: private pay, long-term care insurance, and Veterans Affairs benefits. Medicare doesn't cover assisted living at all. Medicaid waiver programs vary wildly by state and often have waiting lists that run 18 to 36 months. A plan that assumes heavy Medicaid dependence in a state without robust waiver funding is going to fall apart fast. Most facilities charge a base rate covering room and meals, then tiered add-ons for levels of care based on activities of daily living assessments. The standard tiers are something like level one for minimal assistance, level two for moderate help with bathing and medication, and level three for extensive support. The assessment happens at move-in, but residents acuity changes. I've seen a facility lose 12 percent of its per-resident revenue in a single quarter because three long-term residents saw their care needs escalate and the billing system hadn't been updated to reflect the new level. Turnover is a silent revenue killer. The average stay in assisted living runs 20 to 30 months. When someone moves out, you're looking at 30 to 60 days of vacancy while the unit gets refreshed and a new admit goes through orientation. That's one month of lost revenue plus 20 percent of monthly operating costs for turn-and-burn preparation. Your pro forma needs to bake in a realistic vacancy assumption, usually 5 to 8 percent in year one climbing toward 4 percent by year three if operations are steady.
The exit strategy matters as much as the entry. Some operators sell to a REIT or management company after stabilizing occupancy. Others refinance once the property hits 85 percent for two consecutive quarters. A few keep it in the family. Whatever the path, the plan should show the trigger points and approximate valuation multiples so everyone knows what success looks like.
Where Plans Break Down
Assisted living business plans get rejected for a handful of repeat reasons. Overly optimistic occupancy ramps that assume full capacity by month four. Underestimating the time between groundbreaking and licensing, which in most states runs 14 to 22 months depending on jurisdiction and inspection backlog. Ignoring the capital expenditure reserve needed for roof replacements, HVAC overhauls, and life safety upgrades that happen around year five. And failing to factor in the actual cost of regulatory non-compliance, which can mean fines, mandated corrective action plans, and in worst cases suspension of admissions until the state clears the facility. One counter-intuitive point that nobody mentions: higher acuity residents aren't always better revenue. They cost more to staff and attract more scrutiny from inspectors. A facility that takes on a mix of 60 percent low-acuity and 40 percent high-acuity residents will have tighter margins and more operational complexity than one that stays at 80 percent low-to-moderate acuity with a smaller but more consistent staffing footprint. The acuity mix you choose affects everything from your staffing model to your insurance premiums to your inspection risk profile. If you're working with limited capital or a tight timeline, the alternative to a full build-out is acquiring an existing licensed facility with a stabilized resident base. The business plan shifts from development risk to transition risk, which is a different problem but usually easier to model because you have actual occupancy data to work from. It's also faster to generate revenue since you're not waiting on inspections and licensing.

The template I use starts with the market analysis, then locks in the licensing timeline, then builds staffing from the state minimums upward, then projects revenue based on conservative occupancy ramps, and finally runs the financing sensitivity analysis. That order matters. Reverse it and you'll spend weeks adjusting financials that were built on unrealistic staffing or licensing assumptions from the start.