Getting The Assessment Right When It's Not A Textbook Case
Most nursing students learn the classic migration of pain from periumbilical to right lower quadrant, then move on to fever, nausea, and rebound tenderness. In practice, you rarely see all of those together. I've assessed more appendicitis patients in hospital corridors at 2 AM than I care to count, and the presentation is almost never clean. A proper nursing assessment for appendicitis isn't about checking boxes. It's about pattern recognition across multiple data points, some of which will contradict each other.
Nursing Assessment For Appendicitis
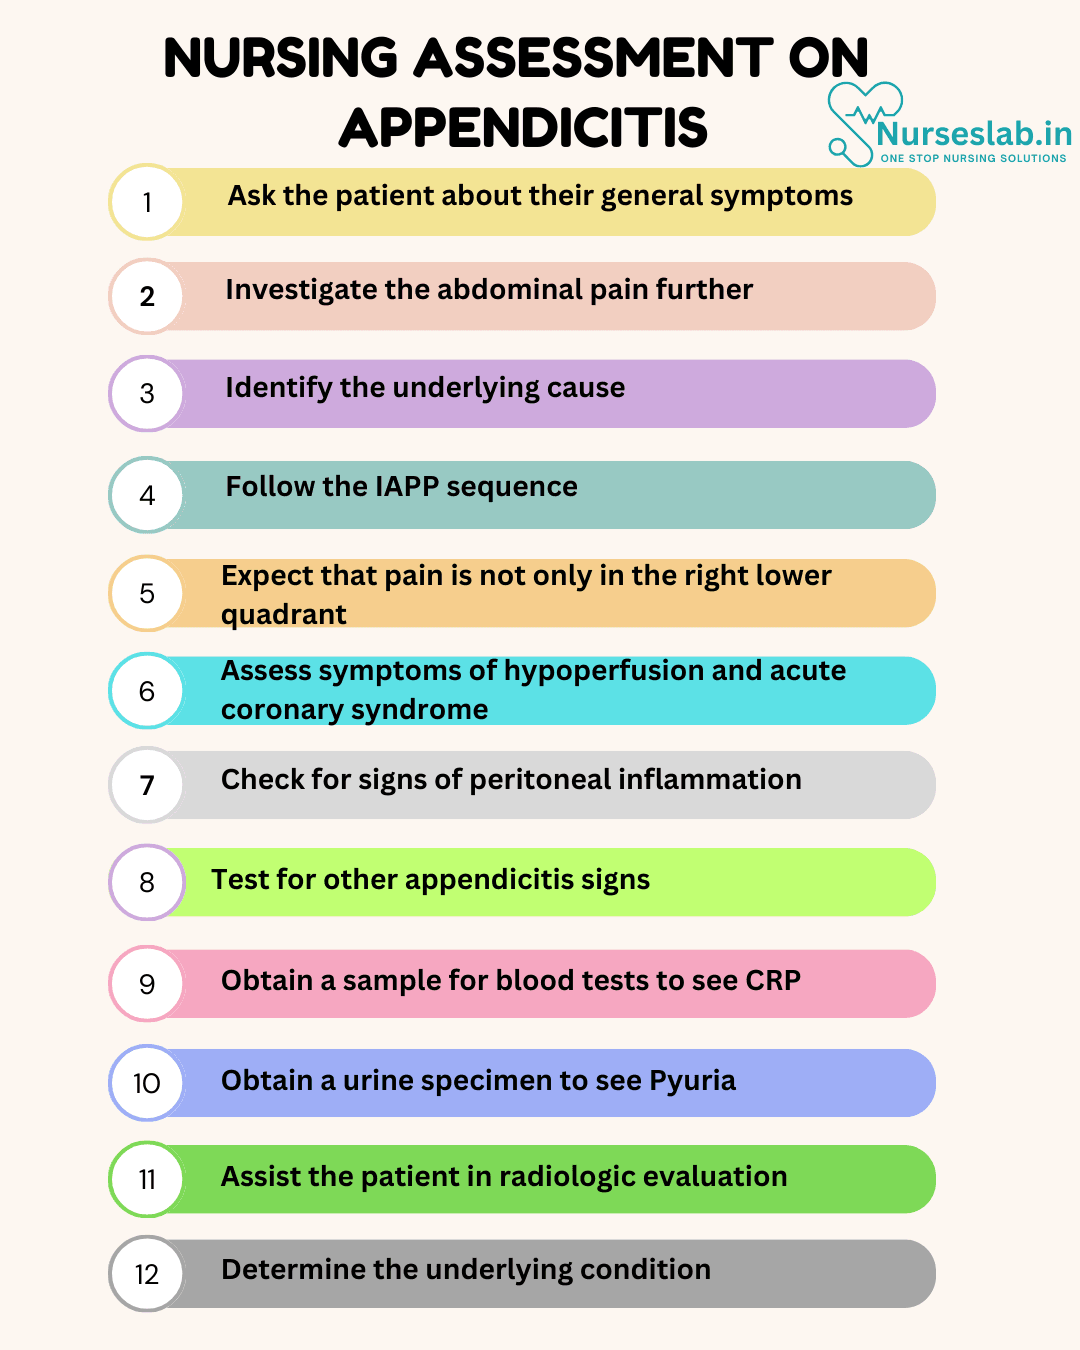
Start with pain characterization. Location is important but misleading. The classic McBurney's point tenderness assumes a normally positioned appendix. If the patient is pregnant, elderly, or has a retrocecal appendix, the pain might be in the flank, back, or even suprapubic. I had a patient last year who presented with left-sided pain because of situs inversus totalis. The appendix was on the wrong side. Without a careful abdominal exam and clinical suspicion, you'd send that person home with a stomach bug diagnosis. Pain migration tells a story. Visceral pain from early appendiceal distension is poorly localized. It's dull, crampy, and hard to pinpoint. As inflammation progresses and reaches the parietal peritoneum, the pain becomes sharp and localized. The transition usually takes four to six hours but can vary widely. Track when the patient first noticed symptoms, when the character changed, and where it moved. Patients often describe this shift themselves if you ask the right way. "It started somewhere around your belly button" and "now it's right down here" is a meaningful clinical clue. Rebound tenderness and guarding are standard exam findings. But here's what doesn't get emphasized enough: the patient's reaction to movement matters more than you'd think. Asking someone to roll over in bed, cough, or take a deep breath can provoke significant pain in appendicitis because every jarring motion irritates the inflamed peritoneum. I use a simple screening question early on: "Does it hurt when you walk to the bathroom?" If they say no and are walking fine, uncomplicated appendicitis becomes less likely. If they're barely able to take a step without wincing, that's useful information even before you touch their abdomen.
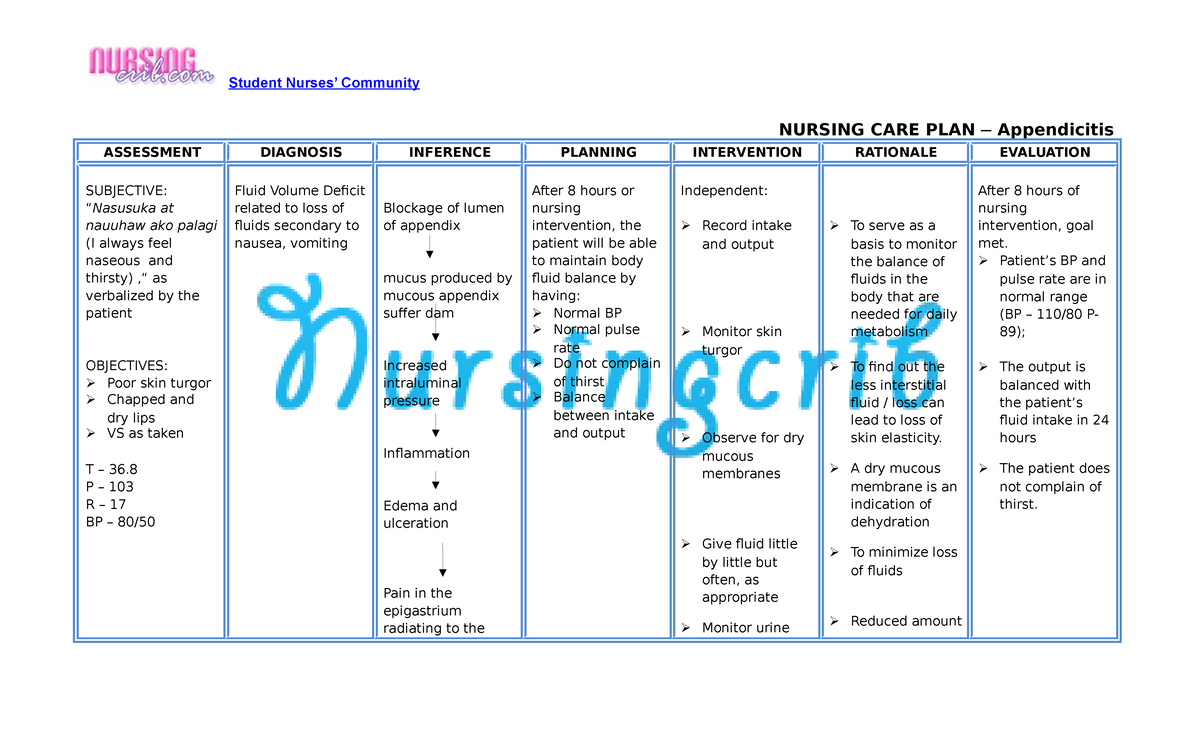
Temperature is another unreliable marker. Many patients with confirmed appendicitis run low-grade fevers or no fever at all during the first twelve hours. By the time a high fever appears, perforation is a real concern. Don't let a normal temperature rule out the diagnosis. In one case, a patient with a temperature of 37.1 C and only mild tenderness still turned out to have a gangrenous appendix. The white blood cell count told the real story, not the thermometer. Lab work and imaging supplement the clinical picture but don't replace it. A normal WBC doesn't appendicitis, and an elevated WBC could mean any number of inflammatory processes. The Alvarado score and ASCO are clinical decision tools that help stratify risk, but they have limitations. The Alvarado score underperforms in elderly patients and children. I've seen both populations slip through the cracks because their scores didn't meet the threshold for imaging. When in doubt, serial exams are your best tool. Assessing the abdomen every two to four hours and documenting changes gives you and the medical team something objective to track. A patient whose tenderness is moving, intensifying, or spreading suggests progression. Someone whose exam improves might not need surgery. Communication with the physician is critical here. I've written too many notes about evolving abdominal exams that deserved a faster response.
Get the Full Details

The biggest pitfall I see nurses fall into is anchoring bias. Once appendicitis is mentioned in the handoff or a lab result comes back abnormal, the entire assessment can become a confirmation exercise. You start looking for signs that fit and unconsciously minimizing signs that don't. Keep an open mind. Gastroenteritis, ovarian cysts, pelvic inflammatory disease, urinary tract infections, and mesenteric adenitis can all mimic appendicitis. Let the full assessment guide you rather than the leading diagnosis. Documentation should be specific. "Abdomen tender in RLQ" is not enough. Note the exact location, the type of tenderness, whether rebound is present, bowel sounds, distension, and the patient's pain score with interventions. Future providers reading your notes will rely on that information, sometimes during a handoff when they haven't examined the patient yet. Garbage in, garbage out. Finally, pay attention to the patient's overall appearance. Appendicitis patients often lie very still because movement worsens their pain. They may be diaphoretic, nauseated, and visibly uncomfortable. A patient who is comfortably chatting while complaining of abdominal pain is unlikely to have acute appendicitis. These behavioral cues are part of the assessment too, and they're easy to overlook when you're focused on checking off physical exam findings.