Ozone Therapy For Mast Cell Activation
The whole idea sounds backwards at first. You have people whose immune system keeps going haywire, mast cells releasing histamine and all those other chemicals over absolutely nothing, and you're telling them to introduce an oxidant into their system. Ozone is literally a powerful oxidant. By every normal logic, this should make things worse. And honestly, it often does, if you go in hot. I've been working with ozone therapy protocols for years, and MCA is one of those conditions where you learn quickly that the standard approach doesn't apply. The literature on this is sparse. Most of what exists comes from practitioners piecing together case reports and a handful of small studies, mostly from Germany and Mexico where ozone therapy has more clinical acceptance. There are no large randomized controlled trials. You're largely operating on mechanism plausibility and anecdotal evidence.
Ozone Therapy For Mast Cell Activation: The Mechanism
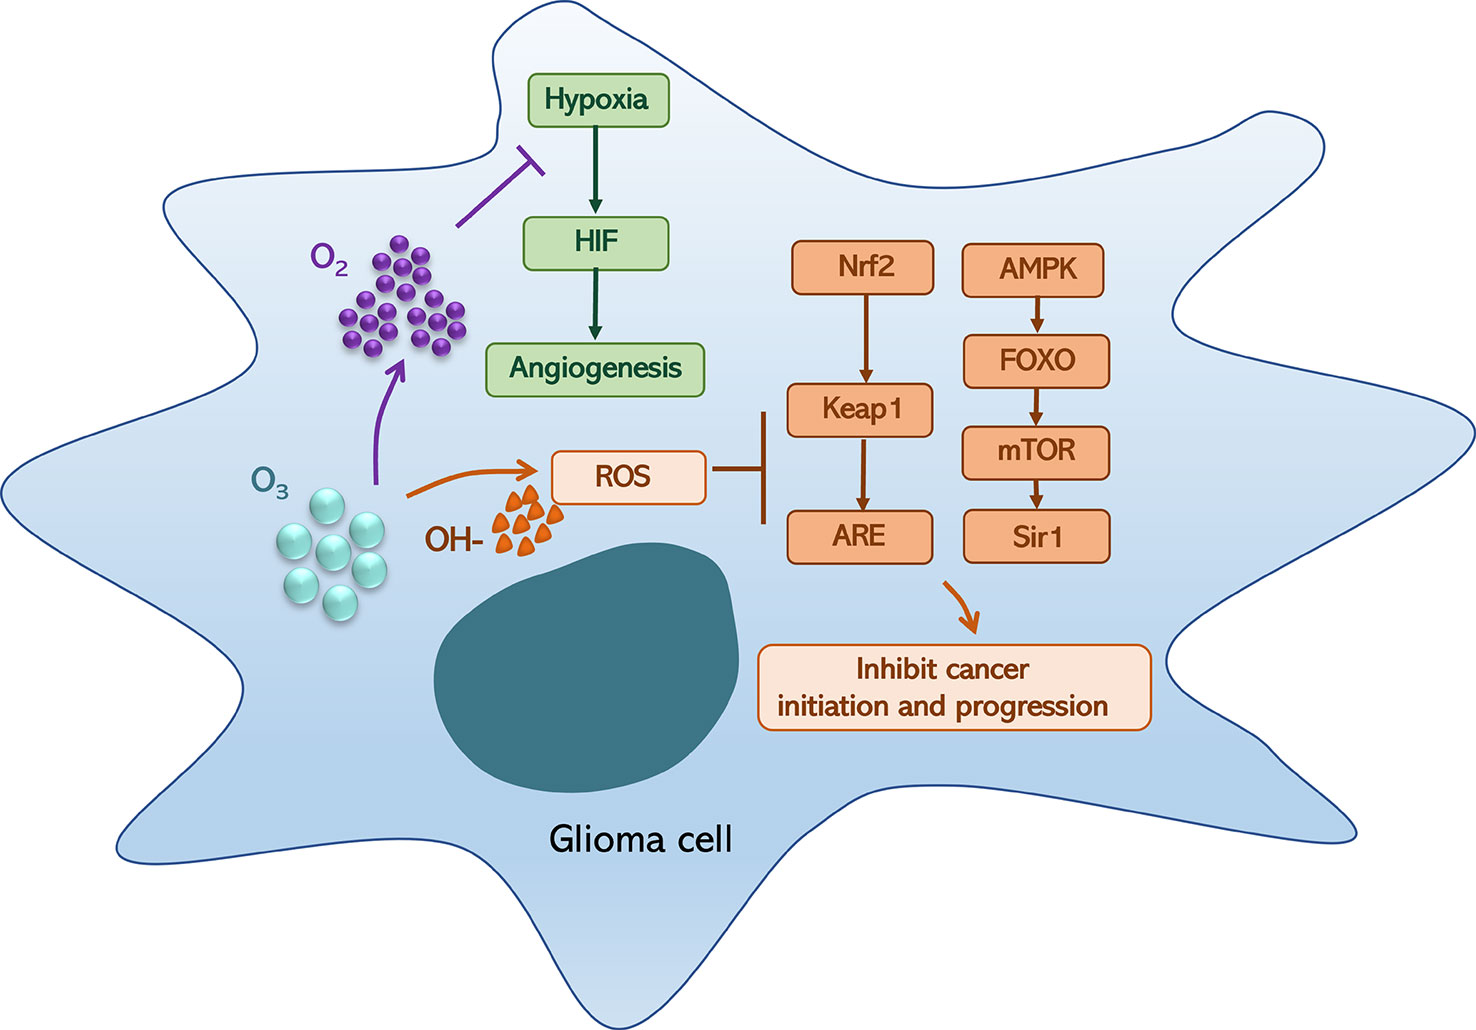
The theory behind using ozone for mast cell issues centers on what's called oxidative hormesis. The basic idea is that a controlled, mild oxidative stimulus triggers the body's own antioxidant defense systems, particularly the Nrf2 pathway. When Nrf2 gets activated, it upregulates glutathione production and other protective enzymes. The hypothesis is that over time, this strengthens the body's ability to handle oxidative stress, which in turn may reduce mast cell hyperreactivity. There's also the anti-inflammatory angle. Ozone modifies lipid peroxidation products in the blood and changes how certain cytokines behave. Some practitioners report a reduction in IL-6 and TNF-alpha after a course of ozone therapy, though the data is inconsistent. Here's the part most people miss. The effect isn't linear. Low doses may stimulate adaptive responses. Higher doses can actually overwhelm and worsen inflammation. With MCA patients, the therapeutic window is razor thin. A dose that works for someone with Lyme or chronic viral issues will likely trigger a significant flare in someone with mast cell activation.
The most commonly used methods for MCA are rectal insufflation and minor autohemotherapy. Rectal insufflation is generally the starting point because it's the least invasive and allows for very controlled dosing. You're looking at concentrations between 10 and 20 micrograms per milliliter, with gas flows of 2 to 5 liters per minute for about 10 to 15 minutes. Major AHT with 100 to 200 mL of blood ozonated at 30 to 40 mcg/mL and reinfused is another option, but most MCA patients can't tolerate that initially. I've seen practitioners start MCA patients at 10 mcg/mL via rectal insufflation, three times per week, and only increase the concentration by 5 mcg/mL increments every few weeks if the patient tolerates it well. It's slow. Frustratingly slow. But jumping ahead usually means bedridden flares lasting days.
Get the Full Details
What I Actually Saw In Practice
I had a patient with confirmed MCAS who also had significant histamine intolerance. We started rectal insufflation at 10 mcg/mL, twice weekly. The first two sessions were fine. On the third session, I bumped the concentration to 15 mcg/mL because symptoms had improved noticeably. That was a mistake. Within two hours of that third treatment, she was down for about 36 hours. Facial flushing, brain fog severe enough that she couldn't form coherent sentences, loose stools, and a blood pressure drop that put her in mild orthostatic territory. Not a full anaphylactic event, but close enough to be alarming. What made it tricky was that her tryptase levels drawn immediately before that session were completely normal. So you'd think, great, the tank is empty, no active degranulation happening. But clearly something was primed and ready to go, and the ozone pushed it over the edge. The workaround was straightforward but required restraint. We dropped back to 10 mcg/mL and reduced frequency to once weekly for three weeks. I also had her take stabilized curcumin and N-acetylcysteine before each session, both of which have some evidence for mast cell stabilization. After that, we tried 12.5 mcg/mL instead of jumping to 15. That tolerated better. The key insight was that her tolerance wasn't just about the dose of ozone itself. It was about the cumulative oxidative load from everything else she was dealing with, and cutting back between sessions gave her system room to recover.
Pitfalls And What Nobody Warns You About
The biggest pitfall is assuming that because a patient tolerates ozone for one condition, they'll tolerate it for MCA. They won't. The dosing philosophy has to change completely. With chronic infections, you can often go harder and faster because the goal is direct antimicrobial effect. With MCA, the goal is immune modulation, which requires gentler, more consistent dosing over a longer period. Another thing people don't tell you: ozone can cause a temporary increase in histamine release as a non-specific stress response. This isn't an allergic reaction to ozone. It's just mast cells being mast cells. If you're not prepared for it, you'll think the therapy is failing when really it's a normal early response that may settle as the patient adjusts. I've seen good practitioners stop treatments prematurely because of this. There's also the issue of ozone generators. Not all of them are created equal. You need a machine that produces ozone without significant NOx byproducts. Cheap units produce nitric oxide and nitrogen dioxide as byproducts, and inhaling or absorbing those can irritate mucous membranes directly. For rectal insufflation, NOx contamination means you're adding a local irritant on top of the ozone, which is counterproductive. I always test my output with a proper ozone analyzer and check for NOx contamination regularly. A good tube ozonator with medical-grade oxygen feed is the minimum setup.
The Limitations
Ozone therapy is not going to fix mast cell activation. At best, it's a supportive modality that some patients respond well to and others don't. The evidence base is weak. Individual response varies enormously. Some people see genuine improvement in their baseline symptoms after a few months. Others see nothing. A smaller subset gets worse and has to stop entirely. If someone has primary mastocytosis or systemic mast cell leukemia, ozone therapy isn't going to help and could potentially be harmful. The oxidant stress in those conditions adds fuel to an already dysregulated system. Anyone pursuing this should have a confirmed diagnosis and be under the care of someone who understands both MCA and ozone therapy, ideally someone who has actually treated MCA patients with it before. The more established interventions for MCA remain mast cell stabilizers like ketotifen and cromolyn sodium, H1 and H2 antihistamines, and leukotriene modifiers. Ozone should be viewed as something you add later if standard treatments don't fully control symptoms, not as a first-line approach.

The practical reality is that if you're going to try ozone for MCA, you start very low, go very slow, track your symptoms meticulously, and have a plan for backing off immediately if things worsen. There's no shortcut around that. The patients who do well on this protocol are the ones who had the discipline to stay conservative. The ones who push too hard learn the hard way.