
What actually happens when pain management goes wrong
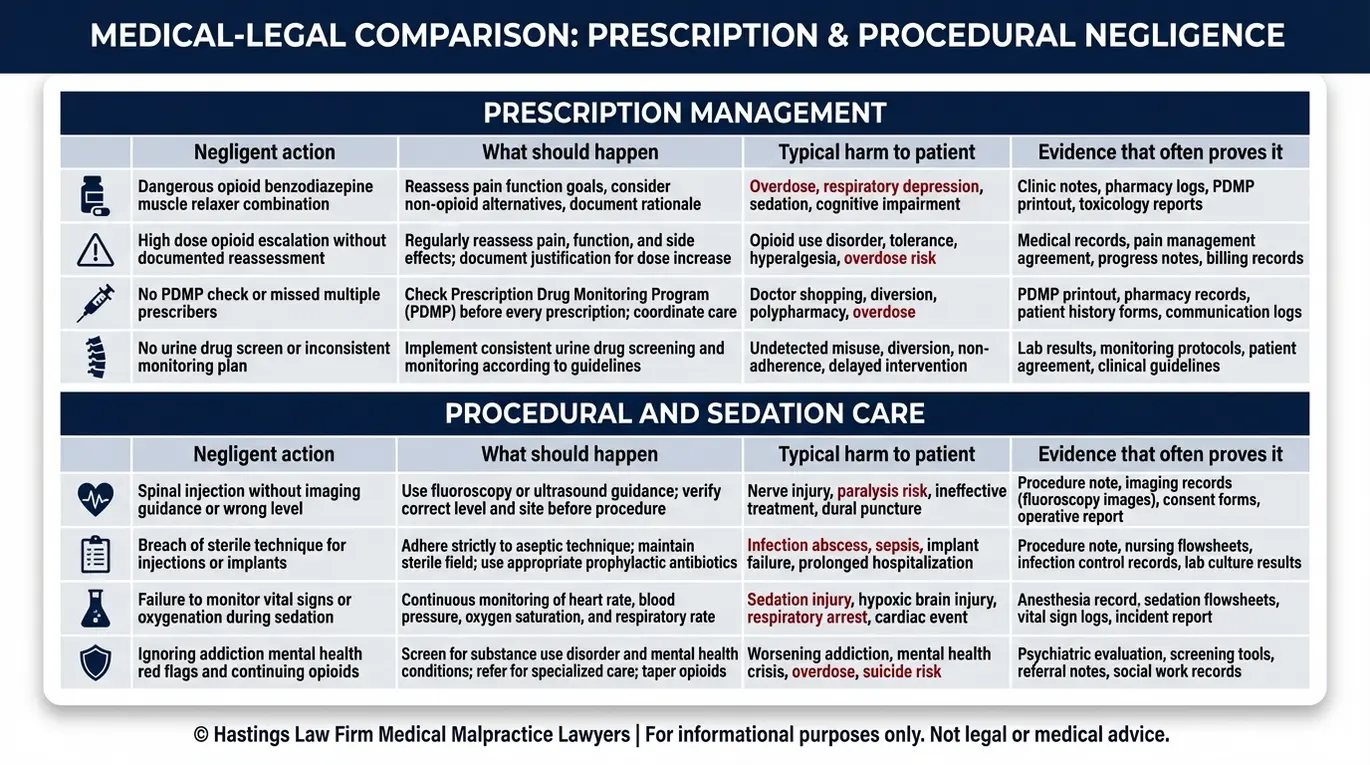
Pain management malpractice is one of those practice areas that sounds straightforward until you are sitting across from a plaintiff's attorney at 11pm reviewing operative reports from three different specialists. The cases are not simple. They involve medications, injections, surgeries, and a lot of chronic pain patients who were already receiving questionable treatment before anything went wrong. The core allegation is usually that a provider deviated from the standard of care in diagnosing, treating, or monitoring a patient receiving interventional or pharmacological pain therapy. That is the textbook version. The reality is messier because chronic pain patients are often on high-dose opioids, multiple adjunct medications, and have undergone repeated procedures over years. The medical record alone rarely tells a clear story about causation. I handled a case where a physician administered an epidural steroid injection using a paramedian approach instead of the midline approach. The patient developed a spinal hematoma and was left with partial paralysis. The physician argued that the paramedian approach is an acceptable variant taught in fellowship. It is, technically. The problem was that the attending physician had never used that approach before, had not reviewed the patient's coagulation profile pre-procedure despite the patient being on warfarin for atrial fibrillation, and obtained no informed consent about the alternative approaches available. The case settled for a six-figure amount after I pulled the physician's privileging records from the hospital and showed the peer review committee minutes where they had previously flagged the same approach as inappropriate for that specific patient population.
The key takeaway from that case is that standard of care in pain management is not just about what techniques exist. It is about whether the provider actually used the technique appropriately for that specific patient. Fellowship training does not create a blanket shield. Prior adverse outcomes do matter if they were documented and the physician continued the same practice anyway.
The documentation problem most attorneys miss
Before you even think about expert testimony or damages, you need to understand the documentation gaps that make or break these cases. Pain management providers are notoriously bad at charting informed consent. The procedure might be documented. The consent form might be signed. But the specific risks discussed, the alternatives offered, and the patient's understanding are almost never recorded in any meaningful way. In my experience, the single most valuable document in these cases is the pre-procedure medication reconciliation. I have seen cases dismissed because the medical record showed the provider verified the patient's anticoagulant status, and cases won because it showed they skipped that step entirely. Look at the pharmacy fill records too. If the chart says the patient was off anticoagulants for five days but the pharmacy data shows continuous filling, that discrepancy is a discovery goldmine.
Get the Full Details
How causation becomes the real fight
Here is something counter-intuitive that beginners in this area often overlook: the worst defendants in pain management malpractice cases are sometimes the ones with the cleanest reputations. A well-known pain specialist with perfect malpractice insurance, favorable peer reviews, and a strong academic profile can be far more dangerous to your case than a provider who has made procedural errors before. Juries like competent people. They trust them. When a respected physician makes a mistake, the jury instinctively wants to rationalize it as an unavoidable complication rather than negligence. The workaround is to establish that the complication was foreseeable and preventable with basic precautions. This means you need a defense that does not rely on the jury understanding the medical details perfectly. It relies on showing that the standard protocol existed, was violated, and that the violation directly caused the harm. Document the protocol. Show the deviation. Connect the two. Another counter-intuitive point: dosing errors in pain management are rarely the proximate cause of catastrophic outcomes unless there is a clear documentation trail showing the dose was administered and the monitoring was inadequate. A medication error that results in mild respiratory depression but the patient recovers fully on its own will not sustain a strong malpractice claim. You need to prove actual harm that would not have occurred with proper care. That means focusing on cases where the error caused permanent damage, prolonged treatment, or death.
The expert witness bottleneck
Finding a qualified expert in pain management is harder than most attorneys realize. Many fellowship-trained pain physicians will not testify against colleagues. The specialty is small, hierarchical, and insular. The physicians who are willing to testify are often either retired, in private practice without institutional ties, or have already testified before and attracted unwanted attention in their own community. I typically build my expert pool by starting with university-affiliated physicians who have publications on procedural complications, then working outward to those who have testified in depositions before. You want someone who has published on the exact procedure in question and has experience treating the specific complication. A general anesthesiologist can opine on sedation-related harm, but they may not be credible on whether an epidural needle placement met the standard of care for interventional pain management specifically. Cost is another factor. Expect to pay $3,000 to $5,000 per day for a qualified pain management expert, plus a retention fee that often runs $10,000 or more. Some experts charge hourly review fees of $400 to $600 per hour. Budget accordingly, or the case will die on the expert budget before it ever reaches trial.
Settlement dynamics you should know about
Pain management cases settle differently than general negligence cases. Insurance carriers for pain management providers often have very high policy limits because the procedures involved carry significant risk. A single adverse outcome from a spinal cord stimulator implant or a vertebroplasty can easily exceed $2 million in lifetime care costs for a young patient who was rendered disabled. That said, many carriers aggressively defend these cases because the medical community is already under scrutiny for overprescribing and overproceduring. There is a perception among some carriers that juries are sympathetic to pain patients but skeptical of defendants who appear to be part of the pain management industry that contributed to the opioid crisis. This makes carriers more willing to settle early, especially when the medical record shows clear documentation gaps. The downside is that early settlement offers are often low because the carrier is testing your preparation. Do not accept the first offer. Build your file thoroughly before making any demands. A well-prepared demand package with imaging, timeline, and expert support can increase the settlement range by 40 to 60 percent compared to a bare-bones demand letter.

When these cases should not be brought
Not every bad outcome is malpractice. Known complications of epidural injections include headache, infection, and nerve irritation. These occur at predictable rates even when the procedure is performed correctly. If your client had a known complication with no documentation suggesting the provider deviated from standard technique, the case will not survive a motion for summary judgment. The defendant will produce peer-reviewed literature showing the complication rate, and your expert will struggle to establish that the outcome was preventable. Similarly, cases involving patients with complex psychiatric histories and polypharmacy regimens are difficult. When the patient was already on twelve medications, had a history of substance use disorder, and was seeing five different providers, establishing that a single provider's negligence caused the harm becomes nearly impossible. The defense will argue multiple alternative causes and contributory negligence. These cases are better suited for settlement negotiation if the liability evidence is weak, but they should not go to trial without a very strong causation theory.
The timeline you need to track
Statute of limitations varies by jurisdiction but is typically two to three years from the date of the alleged negligence or from when the injury should have been discovered. In pain management cases, the discovery rule often applies because complications from procedures like nerve ablations or spinal implants may not manifest for weeks or months. However, you cannot wait indefinitely. Statutes of repose in some states cut off claims after a fixed number of years regardless of when the injury was discovered, which means a patient who receives a spinal cord stimulator and develops complications five years later may still be time-barred depending on the jurisdiction. I always recommend pulling the initial procedure consent forms immediately. The date on that form can anchor your statute analysis and help you determine whether you are working with a discovery rule claim or a straightforward negligence claim. It also helps identify whether the provider discussed the specific complication your client experienced during the informed consent process.
Electronic health records and spoliation risks
Pain management providers increasingly use electronic health record systems that auto-delete or archive older notes after a certain period. Some systems are configured to overwrite previous entries during revision, which creates spoliation issues if the original entry is lost. I have seen cases where the initial nursing note documenting a patient's adverse reaction to a medication was replaced by a later note that downplayed the severity, and the original entry was no longer recoverable from the EHR audit log because the provider had not requested preservation. The workaround is to send a litigation hold letter immediately upon retaining counsel. This should be sent to both the provider and the EHR vendor if possible. Some jurisdictions require the hold letter to be sent within a specific timeframe after filing, so do not delay. The letter should specifically identify the procedure date, the patient's name, and the types of records to preserve, including EHR audit logs, nurse flow sheets, and pharmacy administration records.

Damage calculation specifics
Pain management malpractice damages are different from most other medical malpractice cases because the patients are already suffering from chronic pain before the negligent act. This creates a complication in damage calculation. The defendant will argue that the plaintiff's current condition is attributable to the underlying pain disorder, not the negligence. You need to isolate the additional harm caused by the negligent act. This means you need a thorough pre-injury functional assessment. Obtain records from all providers who treated the patient before the alleged negligence occurred. You need to establish baseline function, baseline medication requirements, and baseline quality of life. Then compare that to the post-injury status. The difference is your compensable damage. Without this baseline, the jury will likely attribute all current symptoms to the original condition, and your damages number will collapse. Lifetime care costs in these cases are substantial. A patient rendered paraplegic after a botched epidural will require lifelong nursing care, adaptive equipment, and repeat hospitalizations. Economic damages alone can exceed $3 million. Non-economic damages for chronic pain that was worsened by the negligence are harder to quantify but juries in pain management cases have awarded significant amounts, particularly when the provider's conduct was egregious, such as operating while impaired or performing procedures without proper consent.
A practical workflow for handling these cases
Start with the medical records. Request them from every provider involved, not just the defendant. Chronologically organize them. Create a timeline that maps every procedure, every medication change, every documented adverse event, and every referral. This timeline will reveal patterns that are invisible when you are reading individual documents in isolation. Next, identify the specific deviation from standard of care. This should be narrow and defensible. Do not list every possible error in the medical record. Pick the strongest one, the one with the clearest documentation, and build your case around it. Multiple weaker allegations dilute the impact of one strong one. Then secure expert consultation before filing. Most jurisdictions require a certificate of merit or expert affidavit at the time of filing. You need the expert to review the records, agree on the standard of care, identify the breach, and opine on causation. Without this, the case will be dismissed on a technicality before it ever gets to discovery.
Finally, consider alternative dispute resolution. Arbitration clauses in pain management consent forms are common and often enforceable. Check the consent documents your client signed. If there is a binding arbitration clause, you may be forced into arbitration rather than court. Arbitration can be faster but also less favorable for plaintiffs because arbitrators tend to split the difference rather than award full damages. Knowing this upfront changes your settlement strategy significantly.


