Understanding the Palmar Fascial Architecture
The palm is not one simple plane. It is a layered system of septa, fat pads, and specialized fascia that keeps you from dislocating your own grip when you're lifting something heavy. Most people look at a diagram of the hand and think they understand it until they try to work on palmar releases or palpate for ganglion cysts. The surface anatomy misleads you because the important structures sit deep to the palmar aponeurosis, and they do not move the way you expect them to move. I spent years doing hand therapy and surgical assisting before I stopped guessing where things were and started paying attention to what I actually felt under my fingers during procedures. One thing that always caught people off guard is how thin the skin gets over the distal palmar crease as you age. I had a patient with a recurrent flexor tendon nodularity right under the A1 pulley region, and every time we debulked it superficially, it came back because we kept missing the deeper fibrotic band anchored to the overlying dermis. The fix was simple once you understand the anatomy: work from the radial side first, release the septa between the thenar and central compartments before touching the lesion itself. Otherwise you just stretch tissue and hope for the best.
Palm Of The Hand Anatomy That Actually Matters
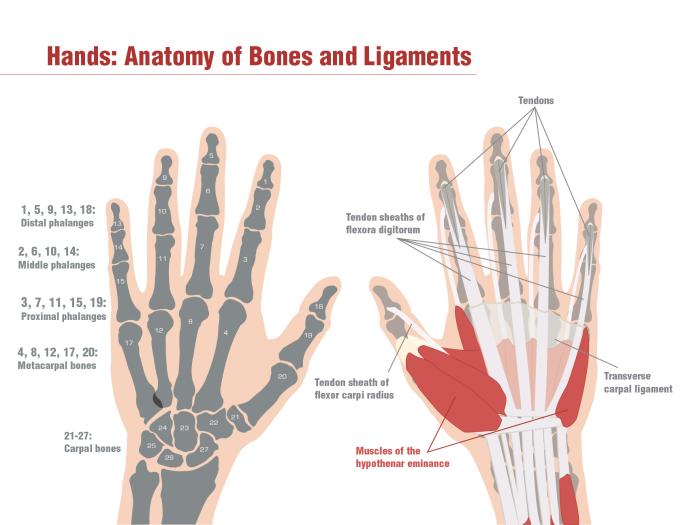
The palmar aponeurosis is the structural centerpiece here. It sits directly deep to the subcutaneous fat of the central palm and attaches proximally to the flexor retinaculum and distally into the long digital fibrous sheaths. This means any force transmitted through the palm — a hard landing on an outstretched hand, repeated gripping, chronic friction from tools — creates stress that funnels right through that aponeurotic sheet. Dupuytren's contracture starts there. Not in the tendons. Not in the bones. In that fascial plane. The thenar and hypothenar compartments are separated by the superficial palmar aponeurosis and the intermuscular septa. Beginners often miss that the abductor digiti minimi sits against the pisiform with almost no protective subcutaneous tissue, which is why repeated compression there — think handle grip pressure, hammer vibration, even aggressive massage — can cause isolated thenar or hypothenar atrophy without any obvious trauma history. I've seen violinists and machinists develop what looked like ulnar nerve palsy but was actually compartment fatigue from chronic pressure on the hook of the hamate. The neurovascular structures run in a predictable but vulnerable arrangement. The median nerve lies radial to the palmaris longus tendon when that muscle is present, and ulnar to it when the tendon is absent. About fifteen percent of the population lacks a Palmaris Longus entirely, and if you're doing any procedure blind or relying solely on surface landmarks, you will place your incision or needle one centimeter too radial and miss the nerve or hit it accidentally. Ultrasound changes the game significantly here, but not everyone has access to one in the field.
The common digital nerves branch from the median and ulnar nerves at the level of the distal palmar crease and travel with the proper digital arteries along the lateral aspects of each finger. There is no safety zone. These nerves sit immediately superficial to the flexor tendons and the digital sheaths, wrapped only by the deep palmar fascia and a thin layer of subcutaneous tissue. Palpating a tender nodule along the course of a digital nerve without imaging can be dangerous if you press hard enough to cause hemorrhage into the nerve sheath. I learned this the hard way during residency when a resident I was supervising massaged a suspected ganglion in the palm with enough force to cause temporary paresthesia that lasted three weeks. The deep palmar arch sits against the metacarpal bones and the interosseous muscles, covered only by the flexor tendons and the lumbricals. This is why direct trauma to the palm — a fall onto a closed fist, a sharp impact — can lacerate the deep palmar arterial network without tearing the overlying skin. The wound looks minor. The bleeding is not. Surgical control of a deep palmar arch injury requires proximal and distal clamping, and you need to know exactly which side of the flexor tendons you are working on. Anterior to the tendons and you are in the midpalmar space. Posterior to them and you are near the interossei and the metacarpal shafts. If you are studying this for clinical or surgical purposes, stop looking at static cross-sections and start feeling cadaver hands. The difference between what a diagram shows and what tissue actually feels like under your fingers is massive. The palmar fat pads are lobulated and separate easily along natural cleavage planes, which means blunt dissection follows fascial boundaries more reliably than you might expect. But the septa between the thenar central and minimal compartments are dense and resistant. You will tear through them if you pull too hard, and once you do, you lose your anatomical landmark for where the abductor digiti minimi originates versus where the flexor digiti minimi brevis begins.
Get the Full Details
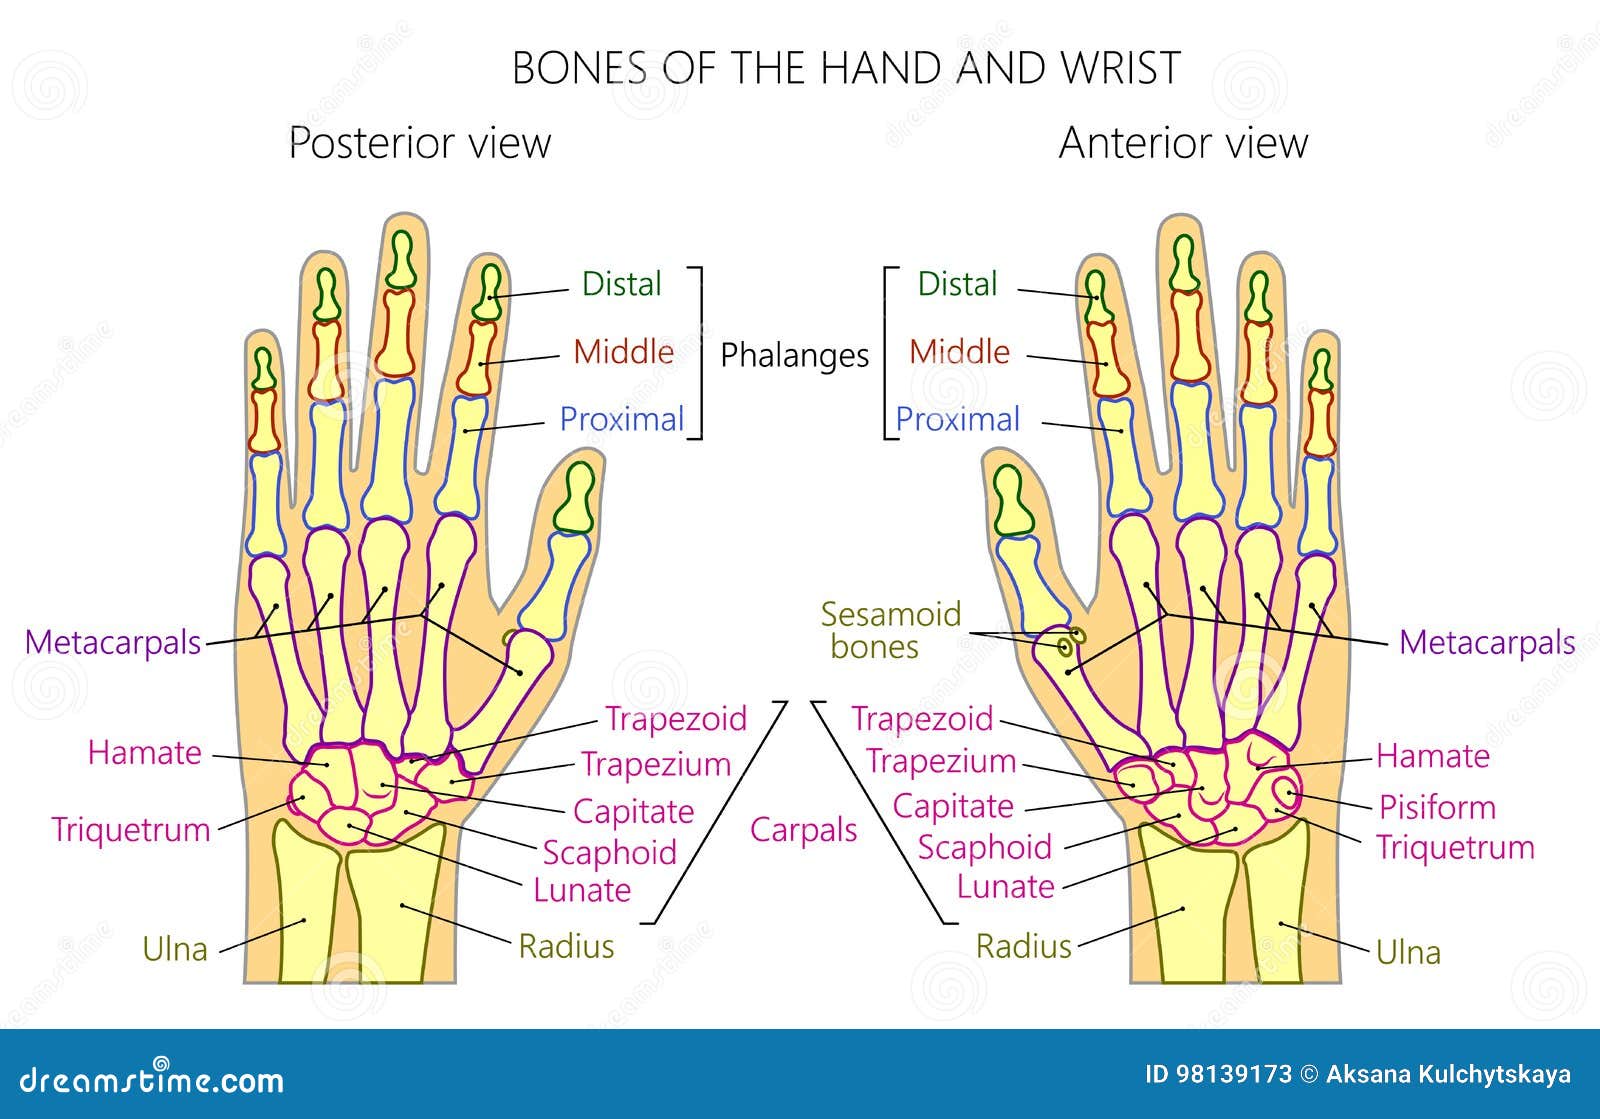
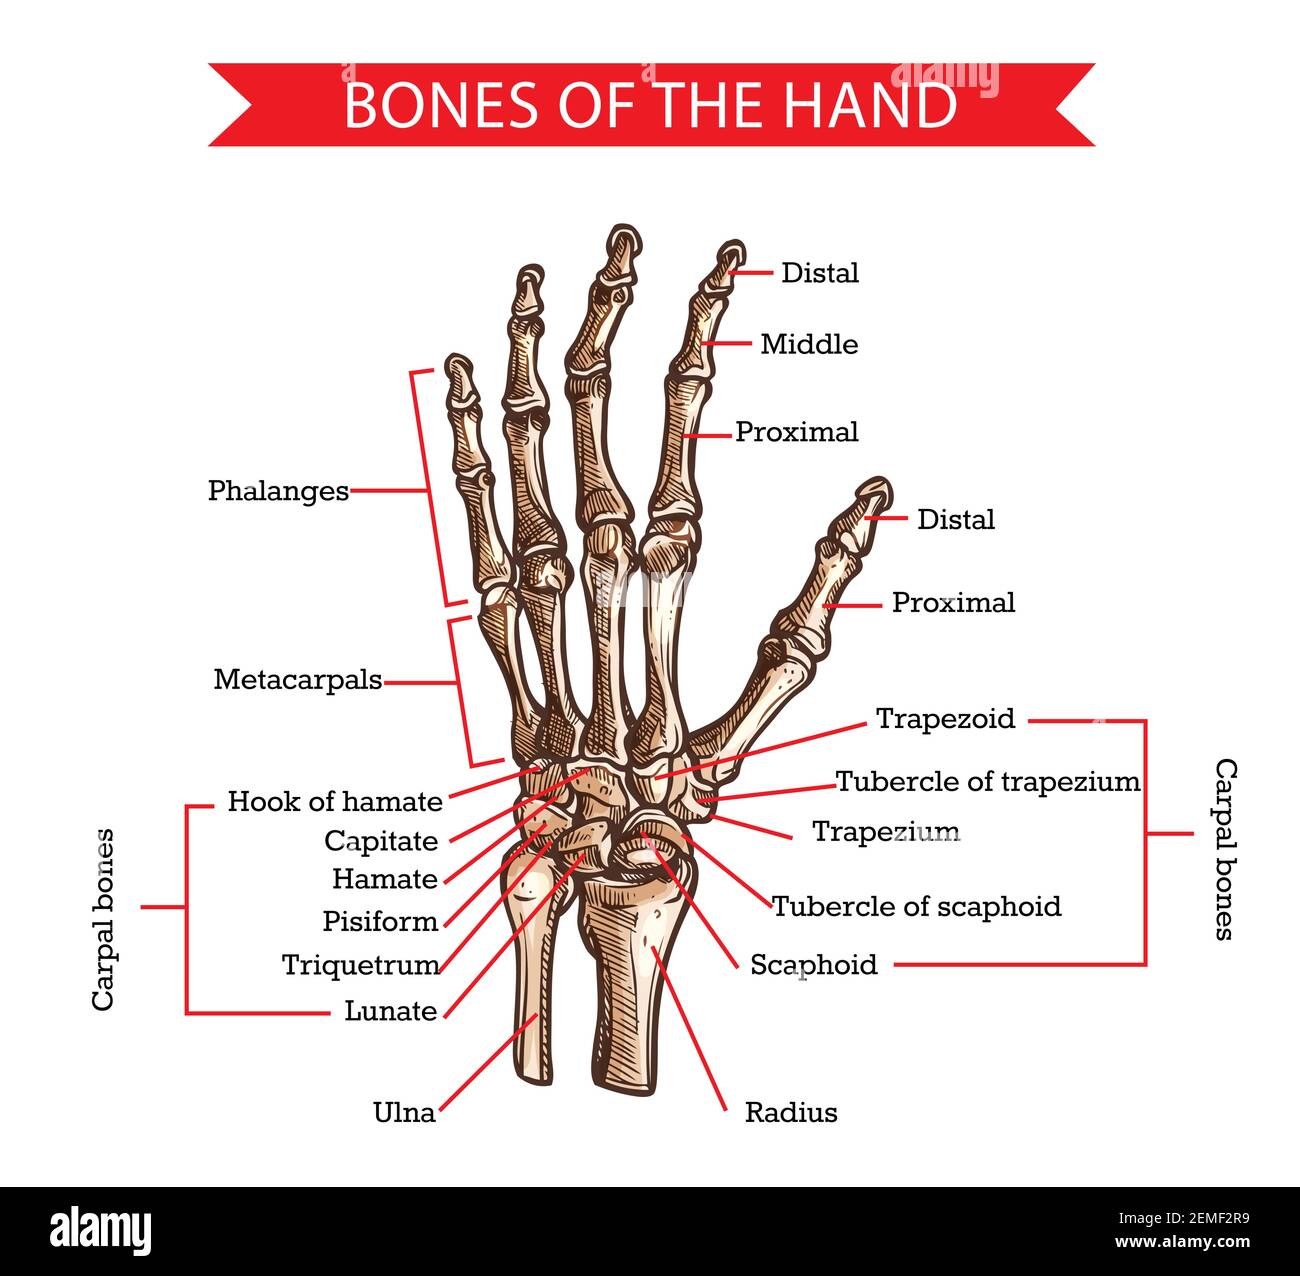
The ulnar tunnel at the wrist deserves special attention because the palm anatomy cannot be understood without it. The canal formed by the hook of the hamate and the pisiform transmits the ulnar artery and nerve. Compression here causes Guyon's canal syndrome, and the differential diagnosis between proximal ulnar nerve lesions and distal ones depends entirely on knowing which branches have already peeled off before the canal. The dorsal cutaneous branch exits proximal to the wrist. If sensation is preserved on the dorsal ulnar hand, the lesion is at or distal to Guyon's canal. If that sensation is lost too, the problem is closer to the elbow. This is not trivia. This is the difference between operating at the wrist versus tracing the nerve up the forearm. One practical note that nobody emphasizes enough: the palmar skin has different dermatomal supply than you might assume. The lateral palm is C6, the central palm is C7, and the medial palm is C8. But the actual boundary between C6 and C7 is not a clean line and it varies between individuals. If you are testing sensory deficits after trauma or surgery, map the entire palmar surface and note exactly where the transition occurs rather than assuming textbook boundaries hold true for the person in front of you. There is no shortcut around understanding this anatomy. Diagrams help, textbooks help, but the real understanding comes from repeatedly palpating live hands and correlating surface landmarks with deep structures. A ganglion on the volar wrist is not the same as a ganglion in the midpalm, even though they both present as a small lump. The surgical approach, the risk to adjacent nerves, and the recurrence rate are all different because the underlying anatomy is different. Pay attention to that distinction and it will save you from making avoidable mistakes.