What You Actually Need to Know About Peripheral Vascular Assessment Nursing
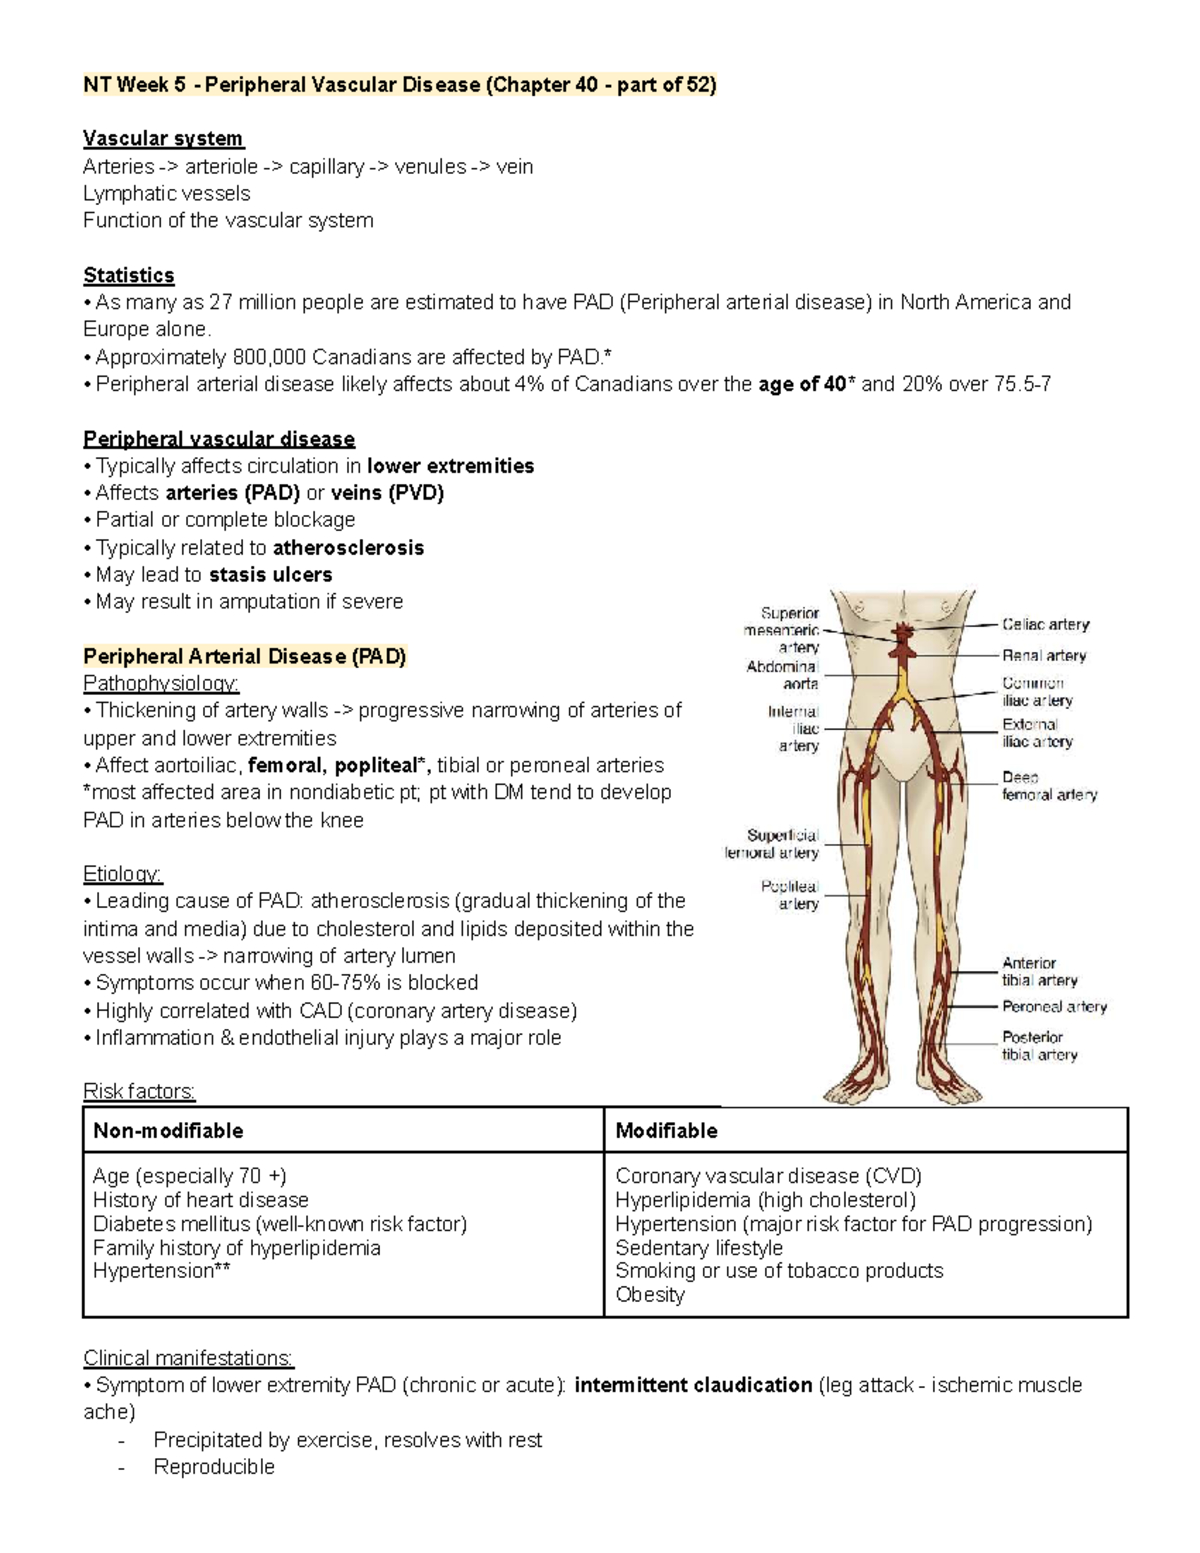
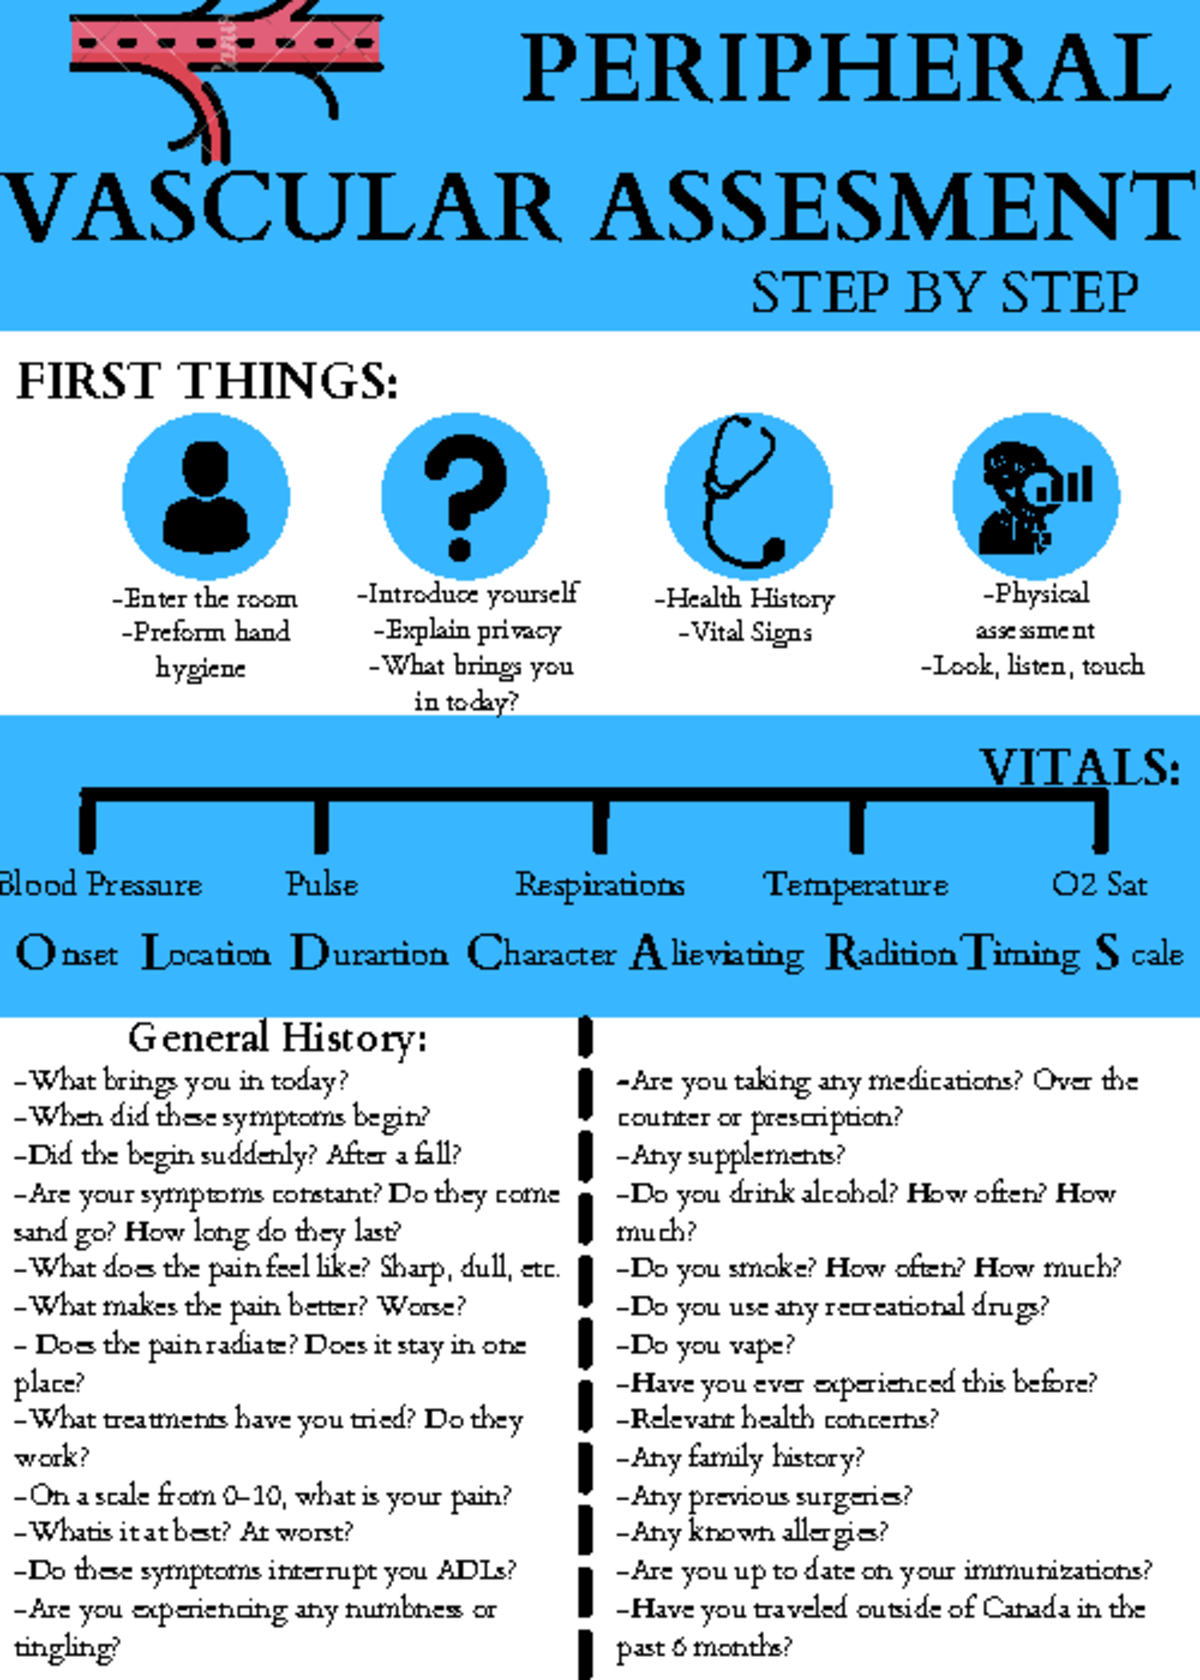
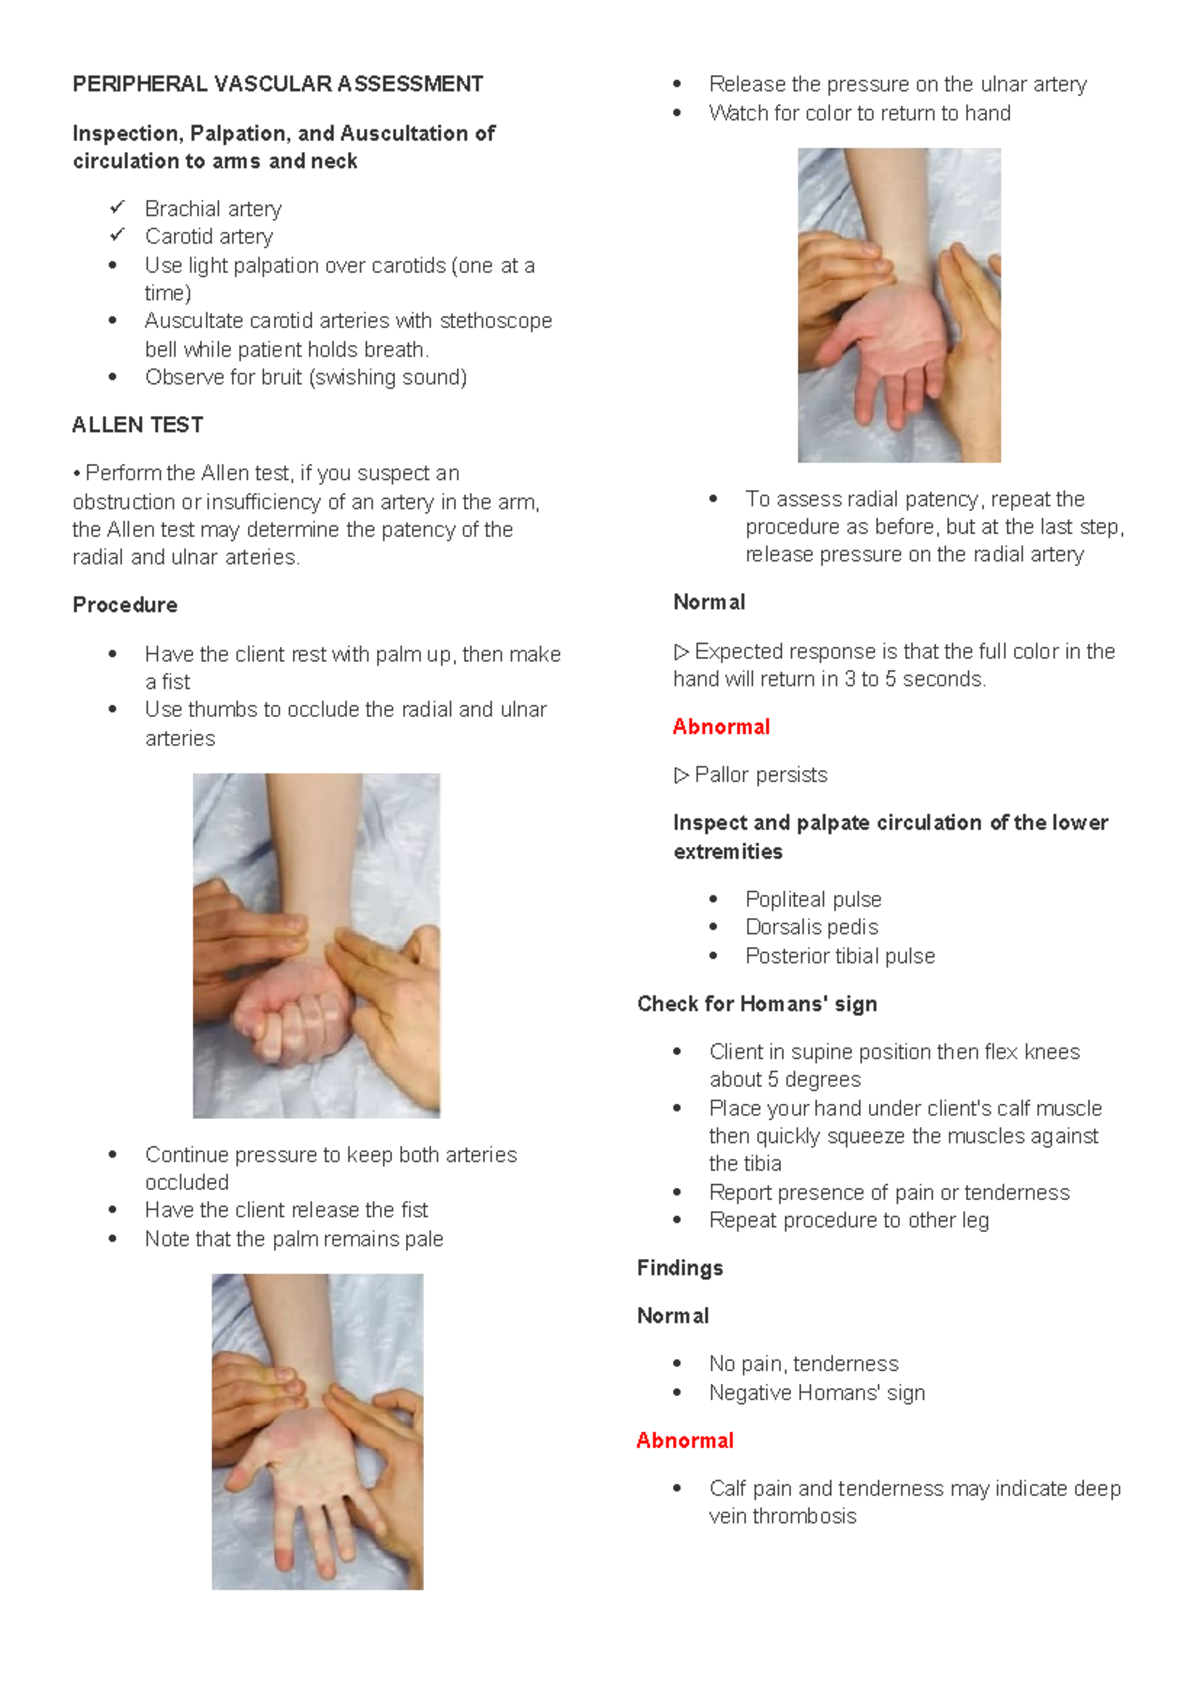
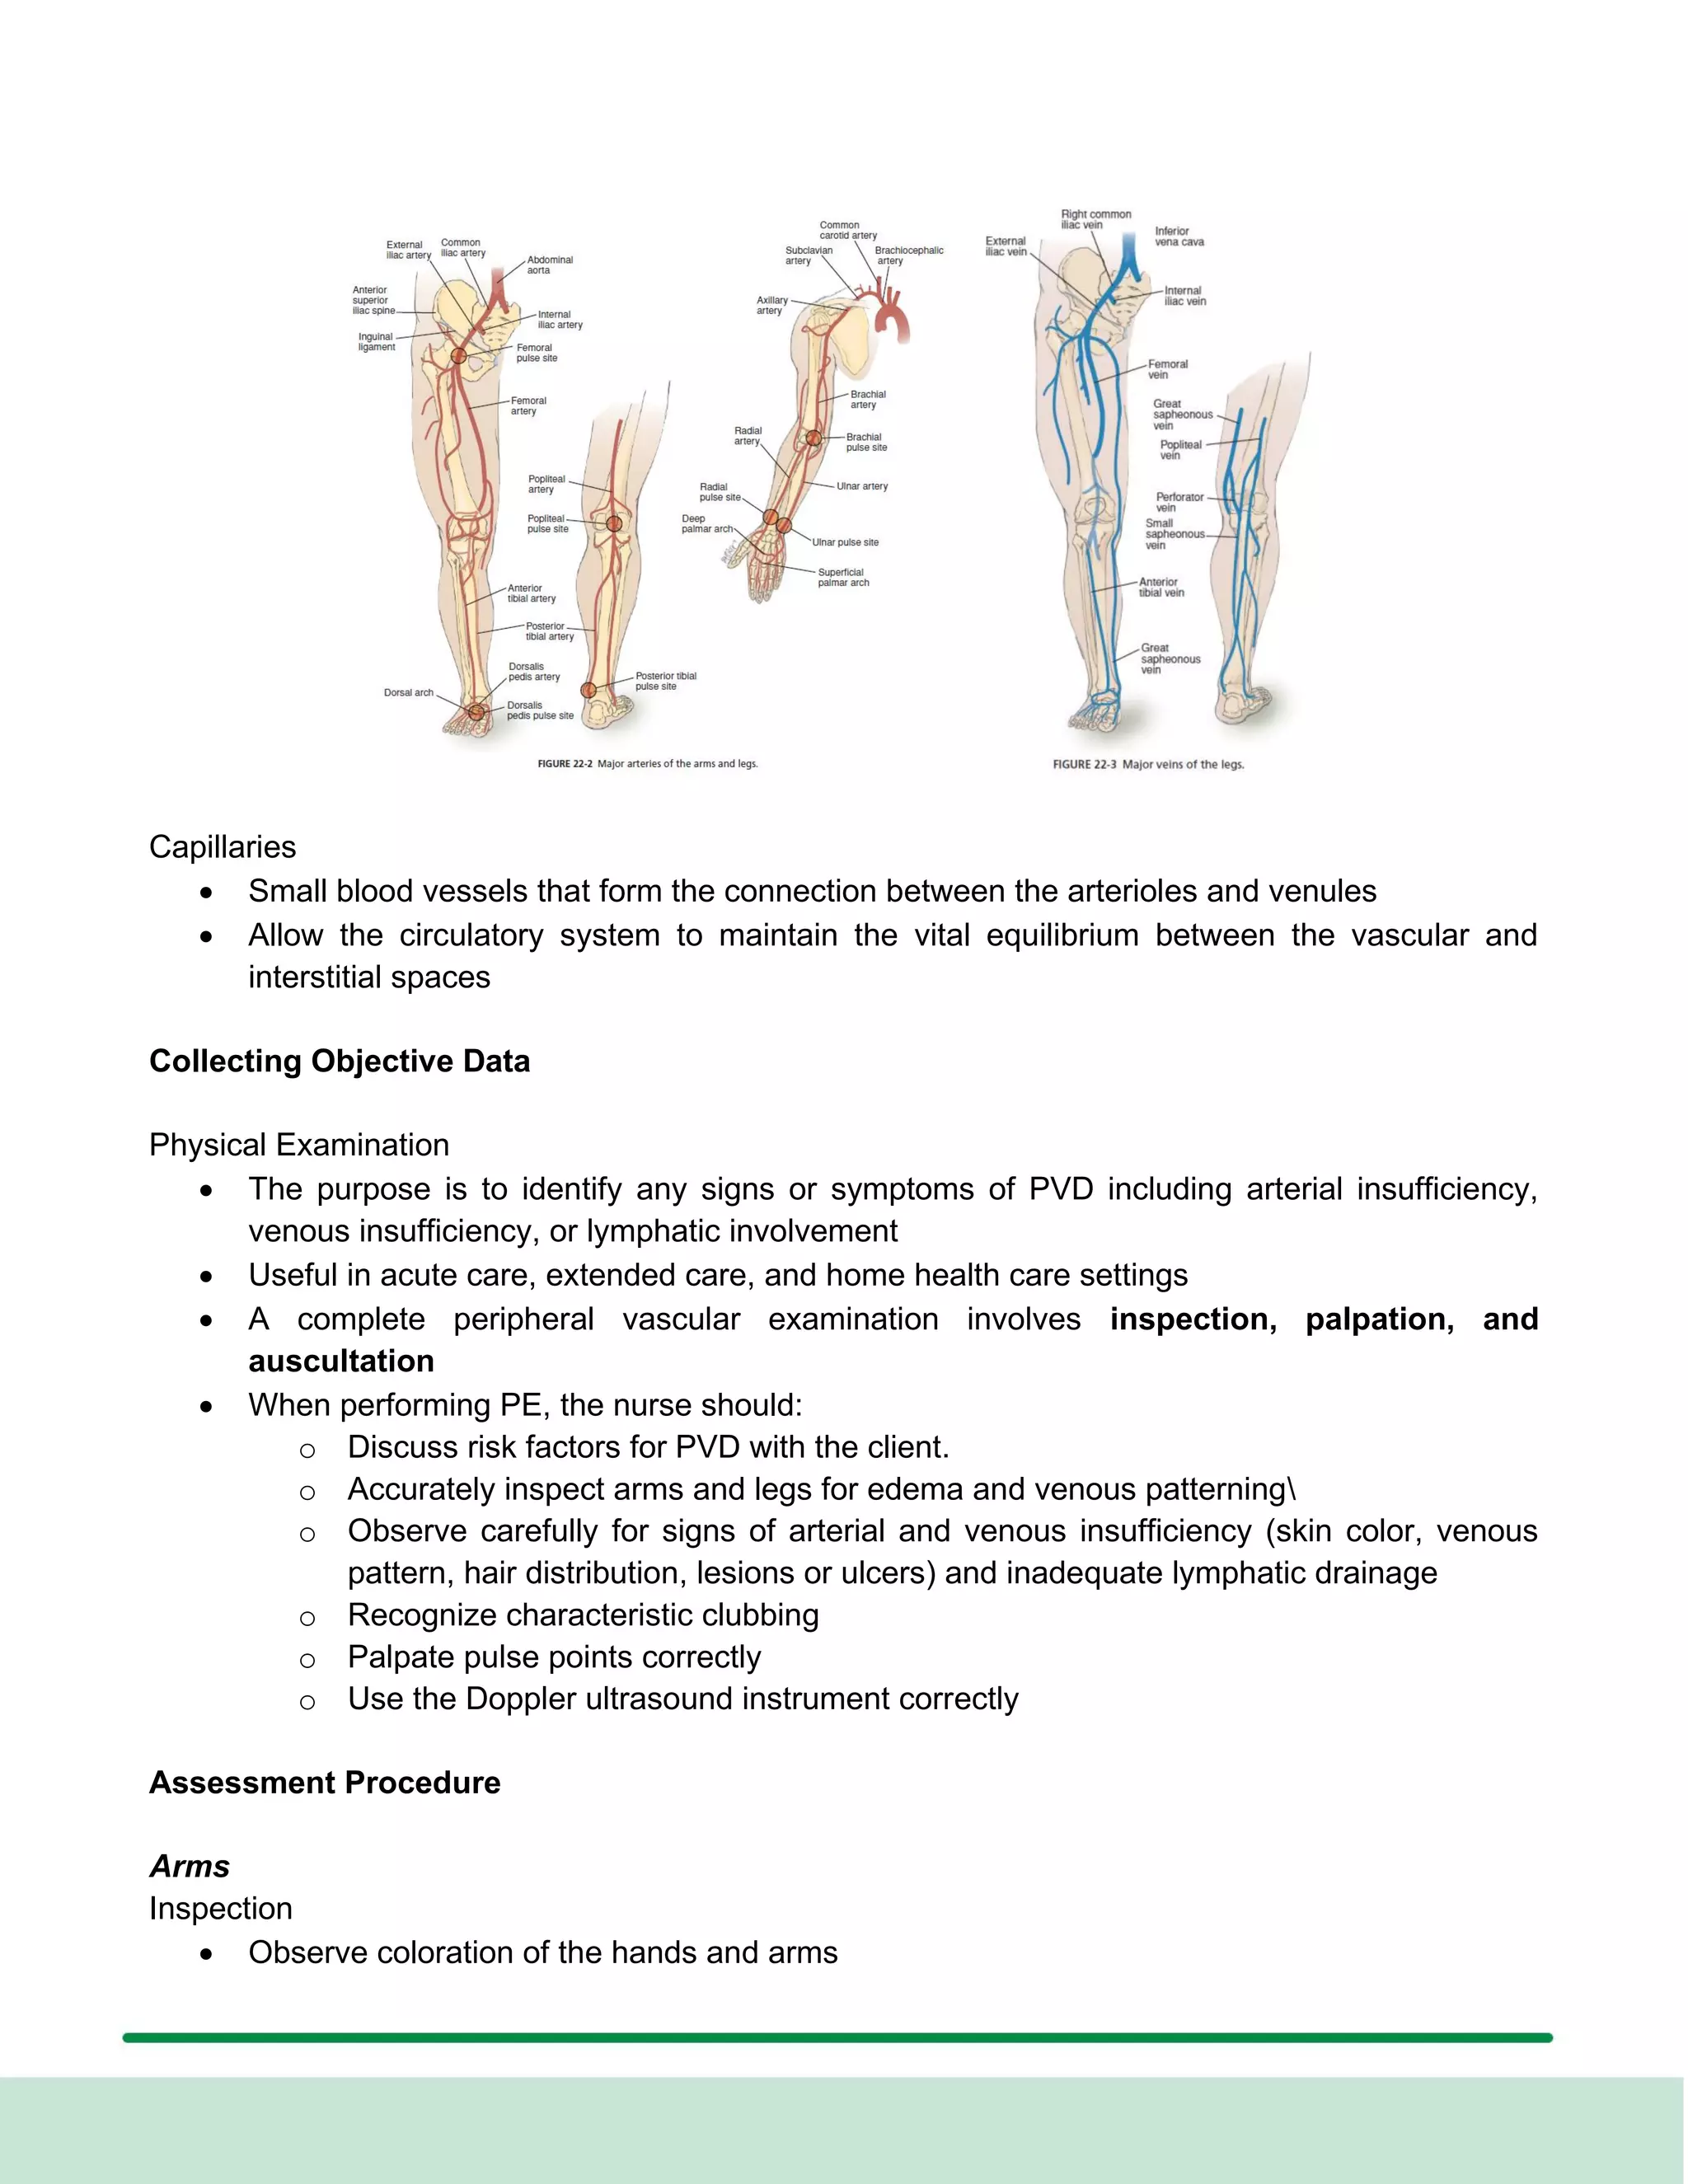
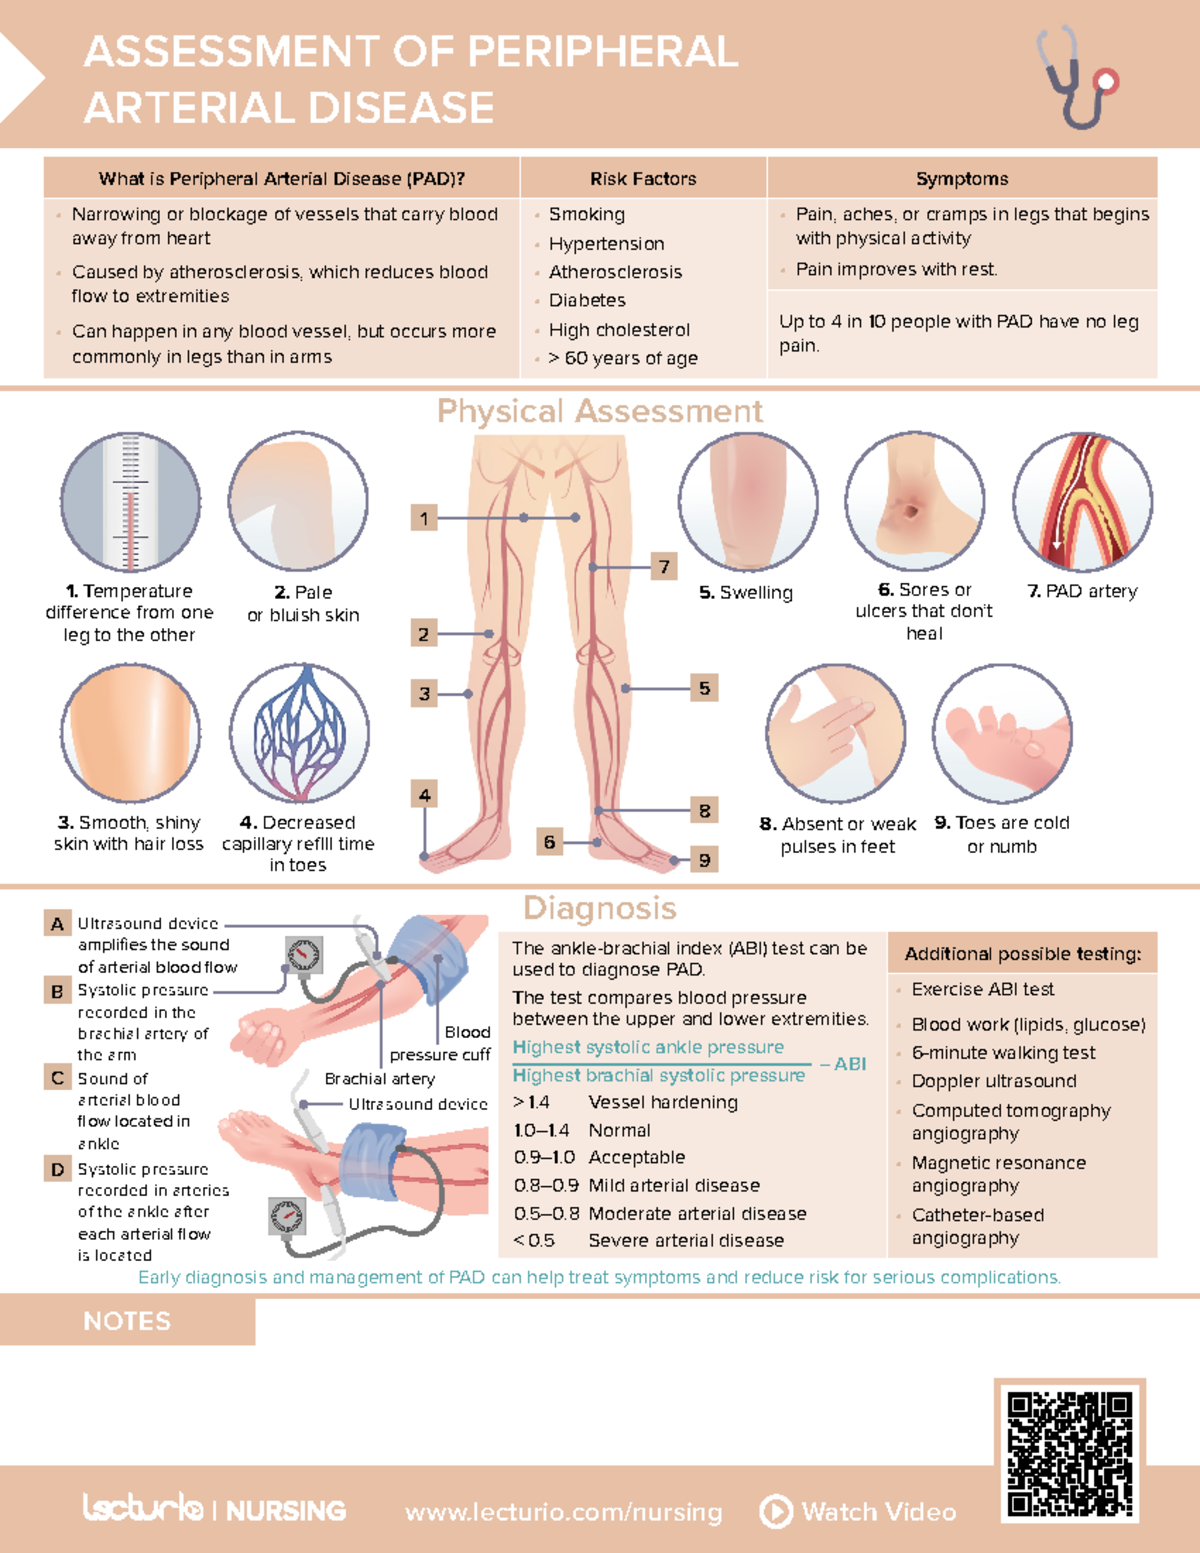
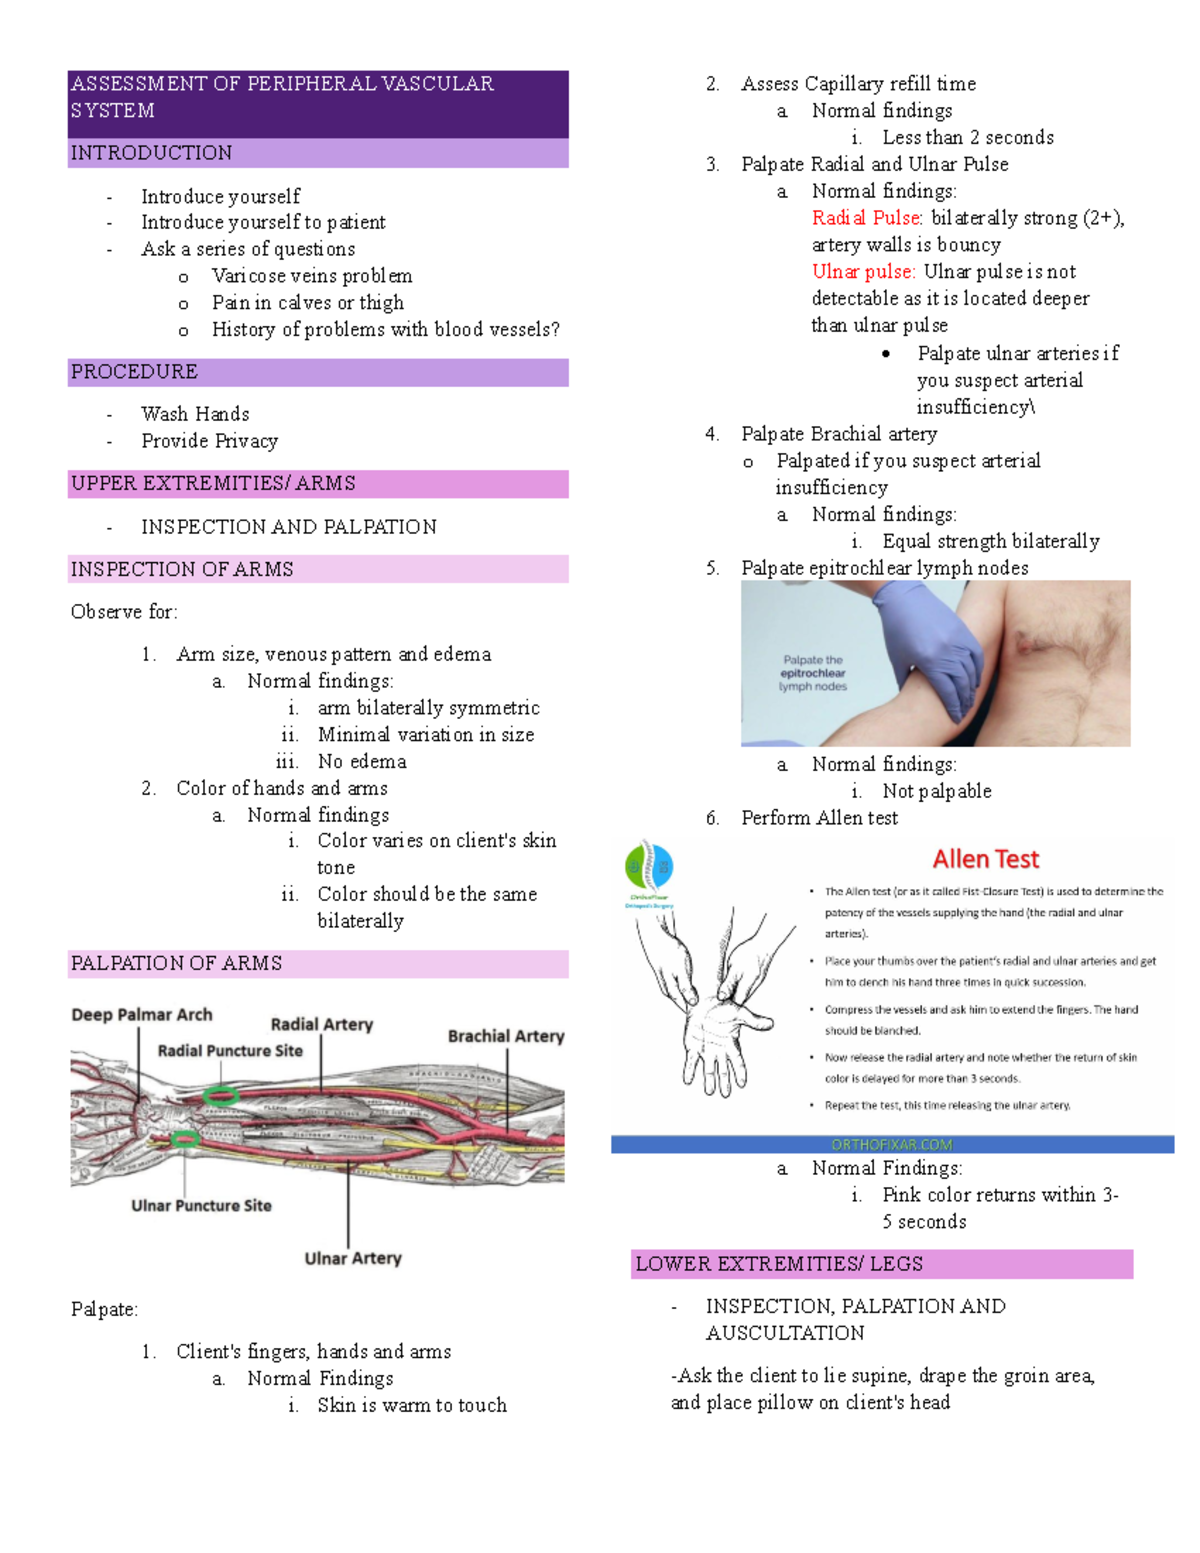
Peripheral Vascular Assessment Nursing involves checking blood flow in the extremities through observation, palpation, and sometimes basic testing. Most nurses can handle the core skills during routine patient assessments. The tricky part is knowing when findings don't match what you expect and what to do about it. I've done thousands of these assessments across different units. Vascular assessment starts with looking at skin color, temperature, and any visible swelling or lesions. Then you move to pulse checks at the radial, brachial, femoral, popliteal, dorsalis pedis, and posterior tibial sites. You're documenting strength from 0 to 4 plus symmetry between sides. Capillary refill testing is standard practice but most people overestimate its reliability. A normal refill takes under two seconds in warm conditions. When patients are cold or have poor perfusion, that number changes completely. I learned this the hard way during a winter shift when multiple patients showed prolonged refill times that turned out to be environmental, not pathological. I warmed their hands with gloves and rechecked before flagging anything abnormal.
Edema assessment uses a grading scale from one to four. One plus means slight indentation that disappears quickly. Four plus indicates deep pitting that doesn't resolve for several minutes. You're pressing over the tibia or ankle for five seconds and watching what happens. Documentation needs to include the grade, location, and whether it's unilateral or bilateral.
The Pulse Grading System
Most nursing programs teach a standard pulse scale. Zero means no detectable pulse. One plus is faint and thready. Two plus is normal. Three plus is full and bounding. Four plus is hyperdynamic. When I worked in cardiac care, I saw how crucial accurate grading becomes when tracking medication effects on hemodynamics. Radial pulses are usually the easiest to find but also the most commonly missed when patients have thick forearms or hair. Turn your head slightly and use two fingers, not your thumb. Your thumb has its own pulse that interferes with what you're trying to feel. Take three to five seconds per site before moving on. Dorsalis pedis pulses disappear in about ten to fifteen percent of healthy adults. Finding them can require positioning the foot in slight dorsiflexion. If you can't locate a dorsalis pedis pulse, check the posterior tibial pulse behind the medial malleolus. Both serve similar vascular territory and either one being present provides acceptable perfusion information for most clinical purposes.
Get the Full Details
When Standard Assessment Falls Short
Sometimes peripheral vascular assessment gives incomplete information. Patients with diabetes often have medial arterial calcification making vessels feel rigid and non-compressible. The ankle-brachial index becomes unreliable in these cases. I had a patient with a history of diabetes where the ABI read above one point four, which normally suggests patent arteries. Duplex ultrasound later showed significant stenosis that the standard assessment missed entirely. Obese patients present different challenges. Subcutaneous tissue dampens pulse signals and makes visualization difficult. Temperature changes affect vessel diameter more dramatically in patients with peripheral artery disease. I've seen pulses that were barely palpable at rest become stronger after passive range of motion exercises. Movement warms the extremities and causes reactive hyperemia. Blood pressure measurement in the legs requires proper cuff size and positioning. The patient should be supine with the leg relaxed. Measuring popliteal pressure while the patient is sitting gives different results than when lying down. Documentation should note position and cuff size used for reproducibility.
Documentation Standards
Proper documentation includes date, time, patient position, and specific findings at each assessment site. Compare left to right and note any asymmetry. Temperature comparison works best using the dorsal hand against the patient's extremity. Document skin integrity including any breaks, discoloration, or changes from baseline. Assessment findings that warrant immediate provider notification include absent pulses, sudden color changes, severe pain with pallor, or capillary refill greater than three seconds in warm conditions. These suggest acute ischemia requiring urgent intervention. Time matters significantly in these scenarios with tissue viability declining rapidly after four to six hours of compromised circulation. Routine reassessment frequency depends on acuity. Stable patients typically need vascular checks every four to eight hours. Post-procedure patients require more frequent monitoring, sometimes hourly initially. Document trends over time rather than single measurements. A gradual decrease in pulse strength matters more than one isolated finding below expectation.
Equipment and Resources
A handheld Doppler unit proves essential when pulses are difficult to palpate. I keep mine stocked and checked monthly because batteries fail unexpectedly. Doppler waveforms provide additional information beyond presence or absence of flow. Triphasic patterns indicate normal arterial function. Monophasic waveforms suggest distal obstruction. Measuring tape for circumference assessment helps track edema progression or resolution. Record measurements at consistent anatomical landmarks, typically ten centimeters above and below the patella for thighs and ten centimeters above the medial malleolus for calves. Same time of day produces most reliable comparisons. Some facilities use infrared thermometers for temperature mapping across extremity regions. This provides objective data when visual assessment feels insufficient. The tool costs more upfront but saves time during complex vascular evaluations.
Common Mistakes to Avoid
Nurses frequently compare pulses between their own hands and the patient instead of comparing patient left to patient right. Your hands vary in sensitivity and warmth. Hold both extremities simultaneously when possible to reduce this error. Another frequent issue involves assessing edema without noting whether pitting is present. Non-pitting edema indicates lymphatic or thyroid issues rather than cardiac or venous problems. The distinction affects treatment pathways significantly. Failure to assess distal pulses in patients with hypertension, diabetes, or smoking history represents a serious oversight. These patients carry elevated risk for peripheral artery disease even without presenting symptoms. Including vascular assessment in routine physical exams catches problems earlier.
Skipping temperature assessment assumes all extremities feel normal by inspection alone. Hands and feet look different from their actual temperature. Contact assessment with the back of your hand against each extremity reveals discrepancies that visual inspection misses.
When to Escalate
Clinical judgment matters significantly in vascular assessment. Not every abnormal finding requires immediate intervention, but certain patterns demand prompt attention. Sudden unilateral swelling with pain and warmth suggests deep vein thrombosis until proven otherwise. Bilateral symmetric edema points toward systemic causes like heart failure or renal disease. Pulse deficits detected during routine screening often indicate underlying pathology requiring further workup. I once identified a diminished femoral pulse during a standard admission assessment. Vascular studies revealed iliac artery stenosis that eventually required intervention before it progressed to critical limb ischemia. Post-operative patients need aggressive vascular monitoring. Surgical positioning can compromise circulation, and anesthesia affects autonomic regulation of vessel tone. Documenting baseline findings before surgery provides reference points for post-operative comparisons.
Practical Workflow
Efficient vascular assessment follows a systematic approach. Start with general observation of all four extremities. Note skin color, visible lesions, and obvious deformities. Move to temperature assessment using tactile comparison. Palpate pulses in a consistent sequence, always comparing symmetrical sites. Check capillary refill in nails and skin. Assess for edema with grading notation. Measure circumference if tracking swelling. This complete assessment typically takes three to five minutes for a stable patient. Rushing through it wastes time later when requires clarification. Taking extra minutes upfront prevents documentation gaps that complicate continuity of care. Teaching students emphasizes that vascular assessment combines multiple data points. No single finding determines clinical decisions. Pulse strength, skin temperature, color, capillary refill, and edema grading all contribute to the overall picture. Discrepancies between findings prompt deeper investigation rather than dismissal.
Special Populations
Elderly patients often show age-related changes in vascular assessment findings. Arterial walls stiffen with calcification, making pulses feel more prominent but less compressible. Skin becomes thinner and more fragile. Edema may be chronic rather than acute. Recognizing normal age-related changes prevents overcalling pathology while still catching genuine problems. Pregnant patients experience increased blood volume affecting peripheral circulation. Mild bilateral edema in dependent positions represents physiological change rather than pathology. Positioning with lateral tilt improves venous return and reduces assessment artifacts from aortocaval compression. Critically ill patients present assessment challenges. Vasopressors cause peripheral vasoconstriction making distal pulses difficult to palpate. Hypothermia slows metabolism and affects pulse character. Core temperature monitoring alongside peripheral assessment provides context for extremity findings.
Patients with peripheral artery disease demonstrate exercise-induced symptoms. Rest pulses may be adequate but walking triggers pain and pulse changes. Asking about claudication distance helps identify functional limitations beyond what static assessment reveals.
Budget Considerations
Basic vascular assessment requires minimal equipment beyond what most nursing stations already maintain. Stethoscopes, measuring tapes, and hand-held Dopplers represent the core toolkit. Some facilities invest in portable duplex systems forPoint-of-care screening. These provide detailed anatomical information but require specialized training to operate and interpret results appropriately. Training costs vary by institution. Basic vascular assessment skills typically integrate into existing clinical rotation curricula. Advanced Doppler interpretation courses run one to two days depending on depth of content. Continuing education credits through professional organizations provide additional learning opportunities.
Final Notes
Peripheral vascular assessment nursing remains a fundamental clinical skill that improves with practice. The techniques described here cover routine assessment scenarios encountered in general nursing practice. Advanced vascular medicine and interventional procedures exist outside standard nursing scope but understanding baseline assessment facilitates appropriate referral and collaboration with vascular specialists. Documentation accuracy directly impacts patient safety. Vague descriptions like "poor pulses" lack clinical utility. Specific notation of grade, location, and comparison to baseline creates meaningful records that support clinical decision-making across care transitions.