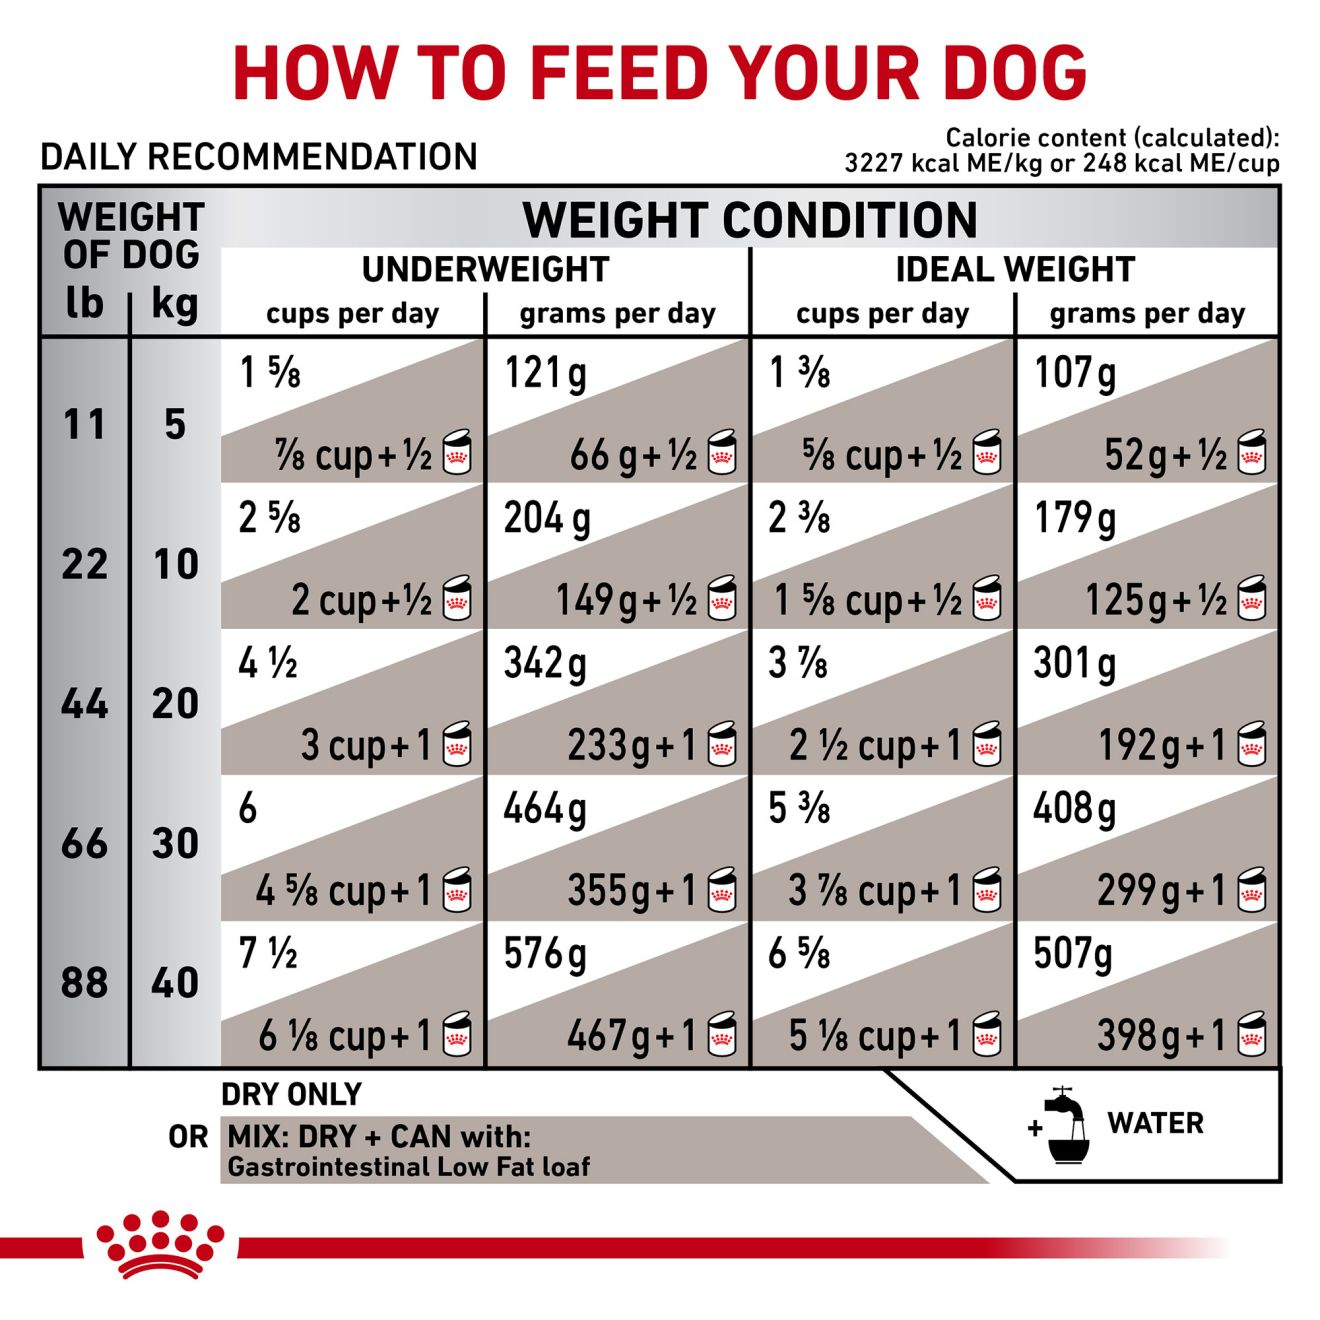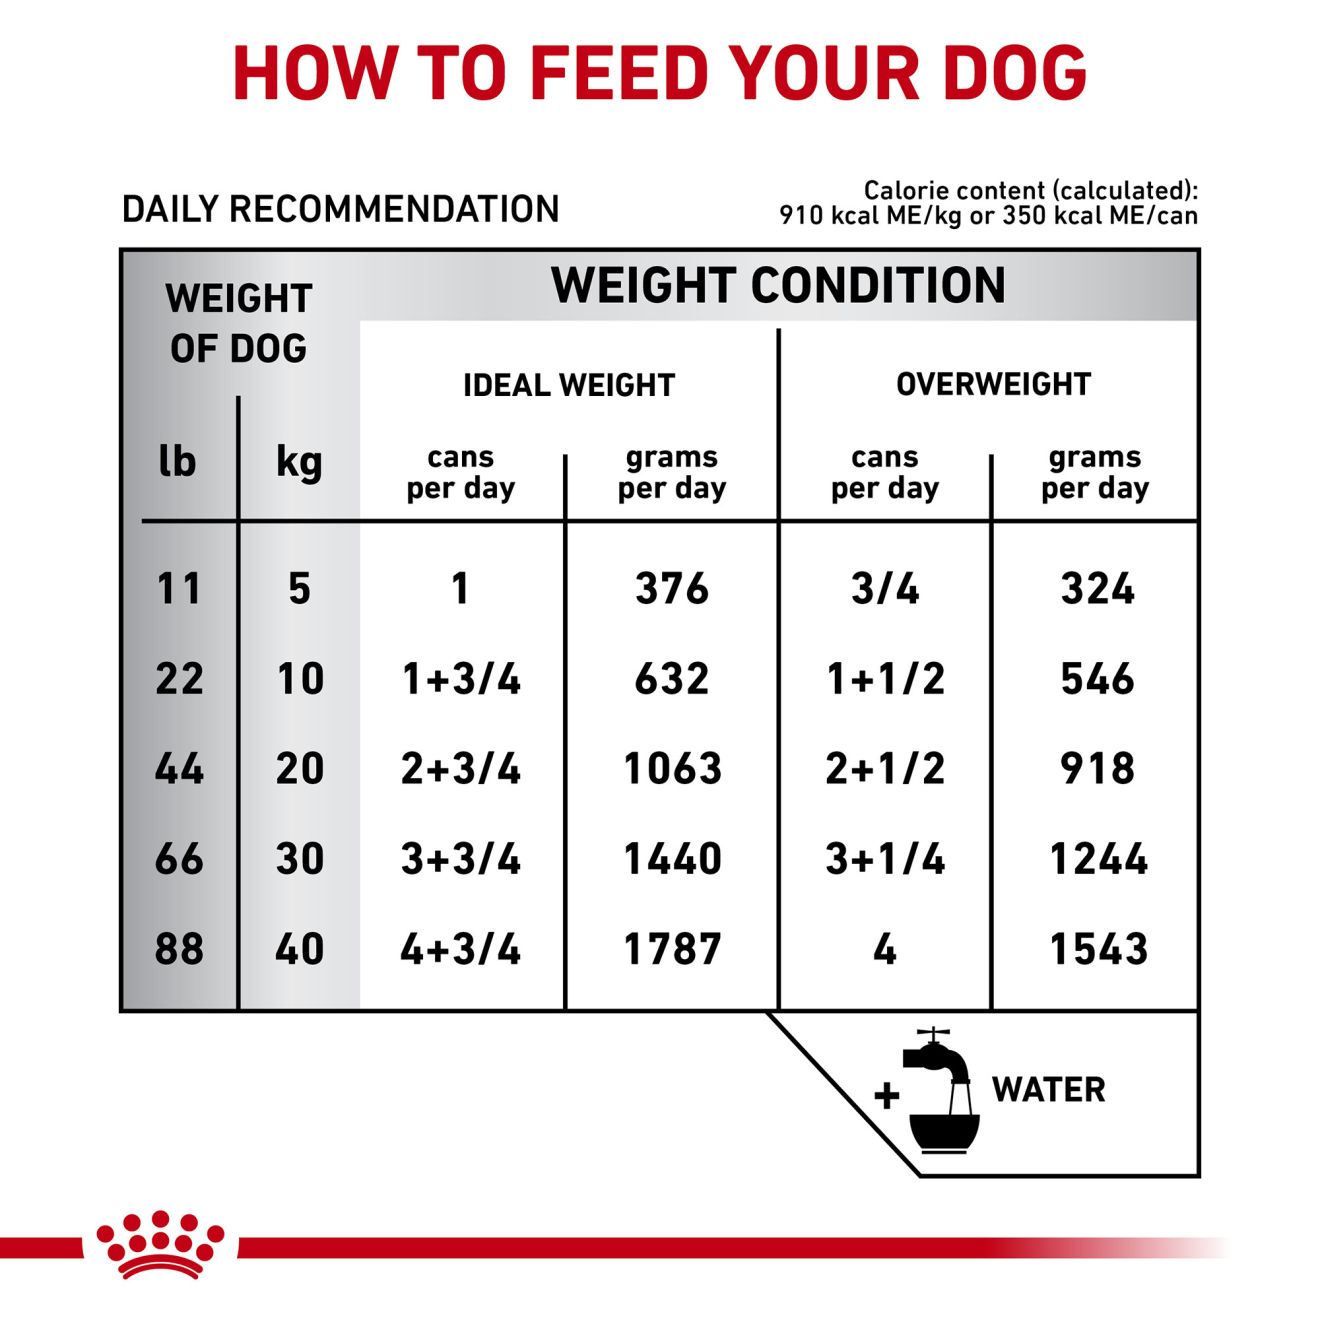
Putting together a feeding plan from Royal Canin Gastrointestinal Low Fat Feeding Guide
I spent years wrestling with gastrointestinal cases in small animal practice, and honestly, the low fat formulations are where most people stumble. You pick up the bag, look at the back, and suddenly you need a spreadsheet just to figure out how much to feed. The Royal Canin Gastrointestinal Low Fat Feeding Guide exists to cut through that confusion, but it still requires you to do actual work rather than plugging a number into a calculator and walking away. The guide is built around ideal body weight, not current body weight. That distinction matters more than people realize. A 30 kg dog who is overweight will be fed to somewhere closer to 24 or 25 kg in caloric terms if the target is gastrointestinal recovery. The chart gives you a daily amount in grams based on weight brackets, but you need to convert that to cups or scoops because most people don't weigh their food every single day. Here's the part nobody warns you about: the calorie density of Gastrointestinal Low Fat is approximately 3,300 kcal per kilogram on a dry matter basis, which is lower than many standard maintenance diets. That means the volume you're feeding is going to be noticeably larger than what the dog was eating before. Some owners mistake that for overfeeding. It isn't. It's just the reality of a restricted fat formula delivering adequate calories through carbohydrate and protein sources.
I had a case last year with a pancreatitis recovery German Shepherd named Barnaby. His owner was using the guide correctly by weight, but she was also giving treats. Two dental chews a day added roughly 300 extra kcal, which pushed him out of the therapeutic window. We ended up calculating the entire daily caloric budget and deducting treat calories first, then adjusting the food amount downward to compensate. Barnaby's triglycerides came down and his stool quality improved within three weeks. The guide didn't account for the treats, and neither did the owner.
The practical mechanics of transitioning
Switching to a low fat gastrointestinal diet requires a slow transition, usually over 7 to 10 days, because the fat reduction alone can cause soft stools if introduced too quickly. I recommend mixing 25% new food with 75% old food for days one and two, 50-50 for days three and four, 75-25 for days five and six, and full transition by day seven. If diarrhea appears at any stage, hold at the current ratio until the stool firmness normalizes, then resume the transition. Rushing this process is the most common mistake I see, and it completely undermines the therapeutic benefit. The food itself has a different texture and mouthfeel compared to regular formulas. The kibble is slightly harder and the fat coating on the outside is minimal. Some dogs refuse it initially. I've found that warming the food slightly with warm water for about ten minutes can help release aromas and improve palatability without significantly changing the macronutrient profile. Just make sure the water is removed or consumed within 30 minutes to avoid bacterial growth.
Get the Full Details
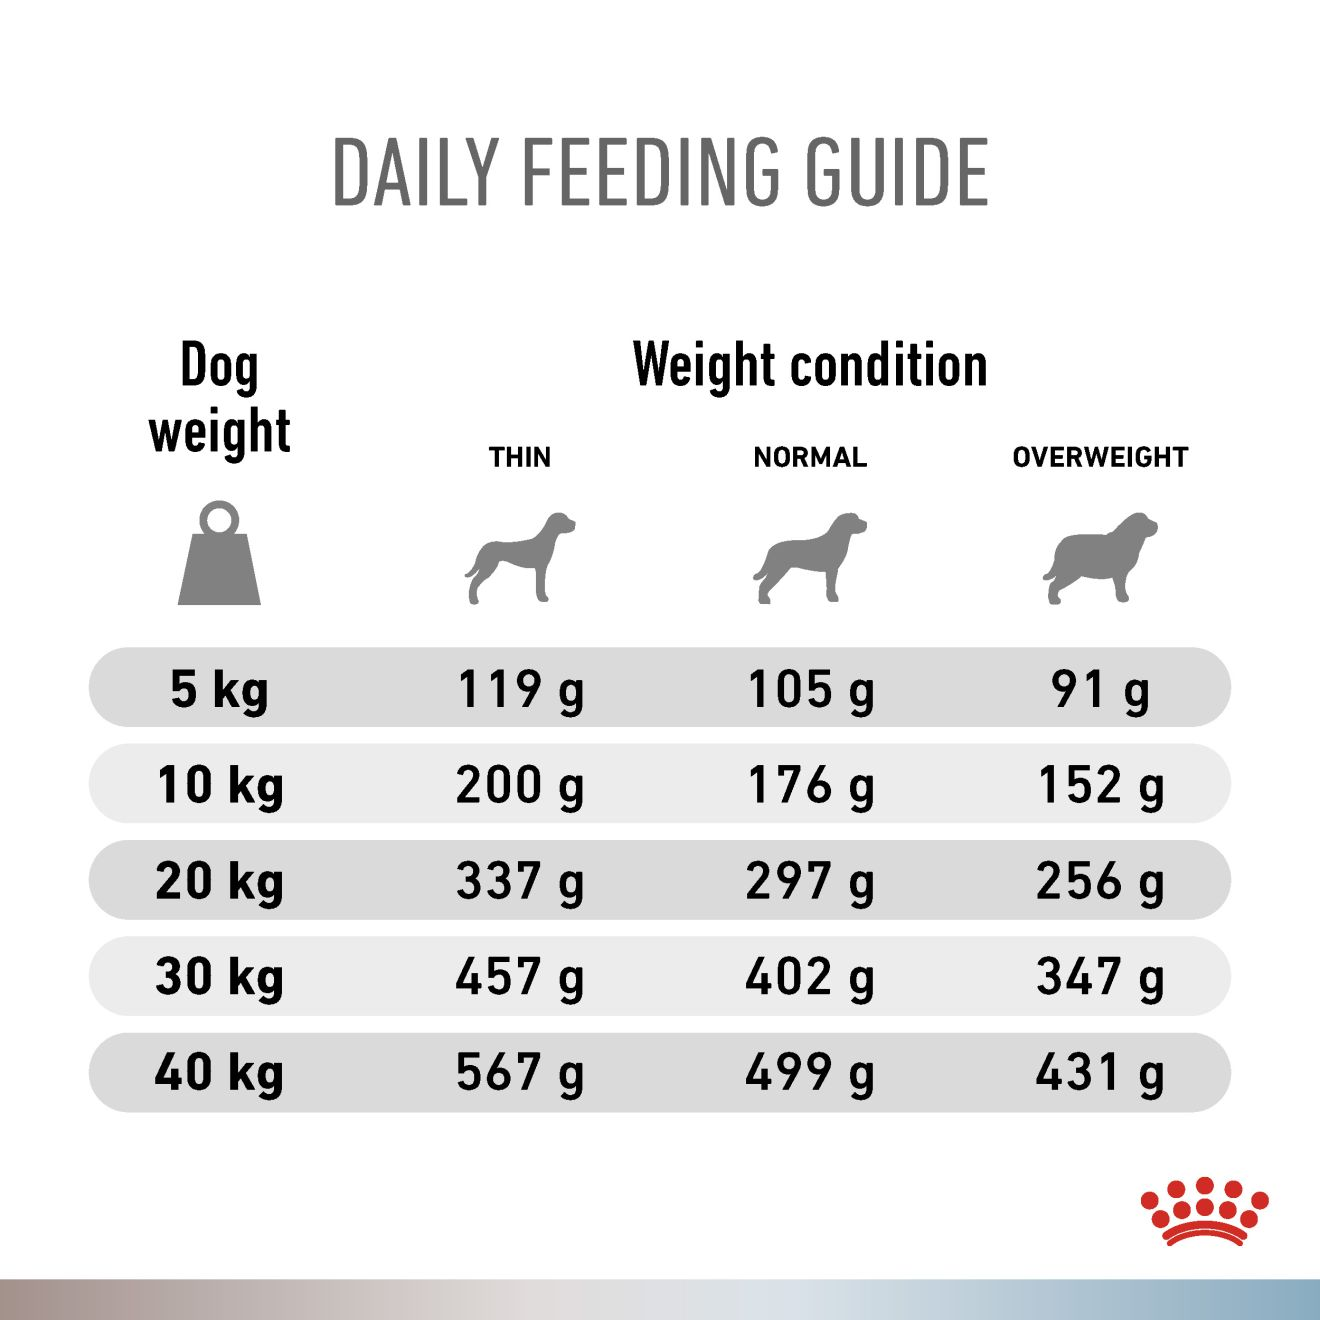
Portion calculation in practice
Let me walk through a real example. A 20 kg neutered adult Labrador with a history of chronic pancreatitis is being transitioned to Gastrointestinal Low Fat. The dog's ideal weight is estimated at 19 kg due to a slightly leaner frame. According to the guide, a 19 kg dog requires approximately 340 grams of the diet per day. That divides into two meals of 170 grams each. If you're using the measuring cup provided in the bag, which holds roughly 113 grams per level cup, you're looking at about 1.5 cups per meal. Weight your food. A kitchen scale costs about fifteen dollars and eliminates the guesswork. The measuring cup on the bag is a starting point, not a precision instrument. Small variations in how you pack the cup can shift the daily intake by 20 or 30 grams, which over a week adds up to meaningful caloric differences in a dog that needs tight management.
Monitoring and adjustment protocols
Body condition scoring should happen weekly during the first month. Feel along the ribs. You should be able to palpate them easily with a thin layer of fat over them. If you can't feel the ribs at all, the dog is gaining too much. If the ribs are prominently visible, the feeding amount needs to increase. The guide provides a starting point, but individual metabolism varies enough that adjustments are almost always necessary within the first two to three weeks. Blood work is the objective measure. Triglycerides are the primary marker we track in pancreatitis cases. Baseline measurement before the diet change, then recheck at 4 to 6 weeks. Most dogs show a significant drop in triglyceride concentration within that window if the diet is being fed accurately and no extra calories are sneaking in through table scraps or high fat treats. I also check albumin and globulin levels because chronic gastrointestinal disease can affect protein status. Low fat doesn't mean low protein, but dogs with long standing intestinal inflammation sometimes present with borderline hypoalbuminemia. The Gastrointestinal Low Fat formula maintains adequate protein levels for most cases, but it's worth monitoring if the clinical picture suggests malabsorption beyond what the diet can address alone.
When this approach hits its limits
Low fat diets are not a universal solution for every gastrointestinal problem. Dogs with exocrine pancreatic insufficiency still require pancreatic enzyme supplementation alongside dietary management. The low fat content helps reduce the workload on the pancreas, but it won't replace enzymes. Dogs with bile acid malabsorption or inflammatory bowel disease may need additional interventions such as budesonide or dietary fiber adjustments that go beyond what the standard feeding guide addresses. There's also the cost factor. Gastrointestinal Low Fat is priced higher than many standard maintenance diets, sometimes 30 to 40 percent more per kilogram. For chronic cases requiring 6 to 12 months of feeding, that adds up. Some owners negotiate with their veterinarians for sample bags or promotional pricing during the initial transition period. It's worth asking because the cost of untreated dietary noncompliance far exceeds the price difference. Another limitation is palatability over time. Dogs that eat this formula long term sometimes show signs of food fatigue, which manifests as decreased appetite or increased begging behavior at mealtimes. Rotating to a different therapeutic formula under veterinary guidance after several months, or incorporating controlled flavor variation, can help maintain compliance without compromising the therapeutic goal.
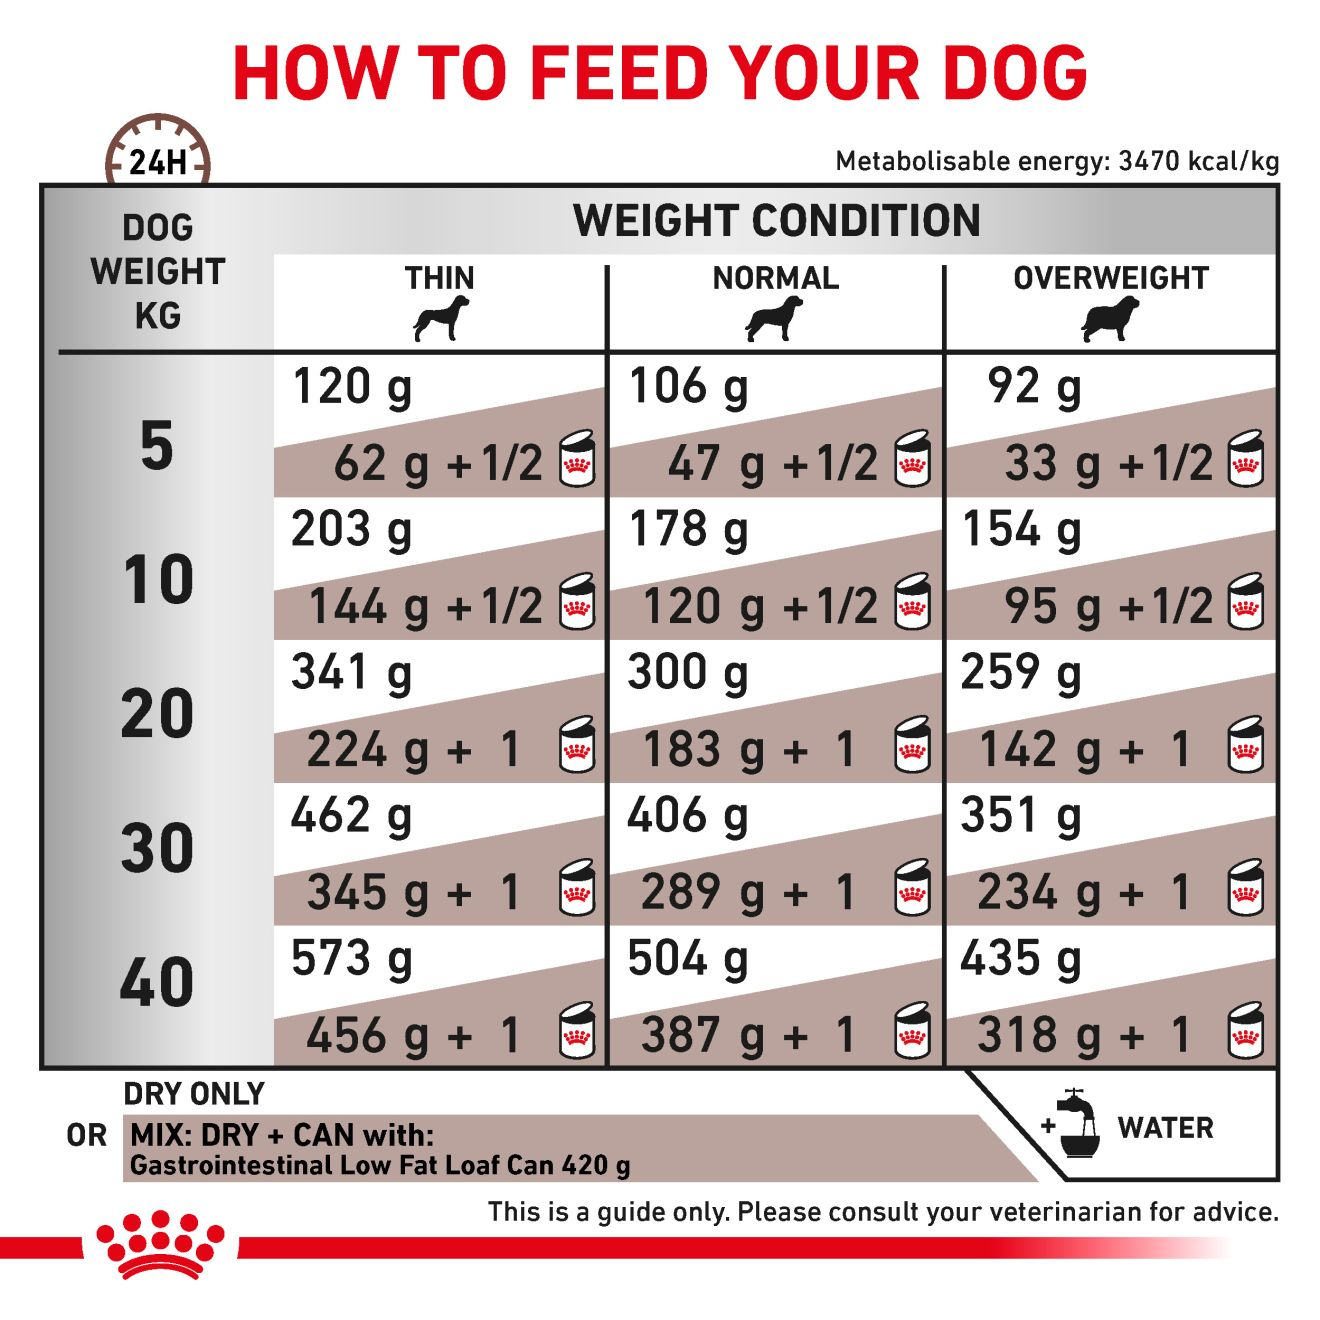
The Royal Canin Gastrointestinal Low Fat Feeding Guide is a solid foundation, but it's a foundation, not a complete treatment plan. The numbers in the chart assume perfect compliance, consistent body weight, and no external caloric input. None of those assumptions hold in real practice without active management from the owner and follow-up from the veterinarian. Get the baseline weight right, weigh the food, monitor the bloodwork, and adjust based on actual response rather than the chart alone.