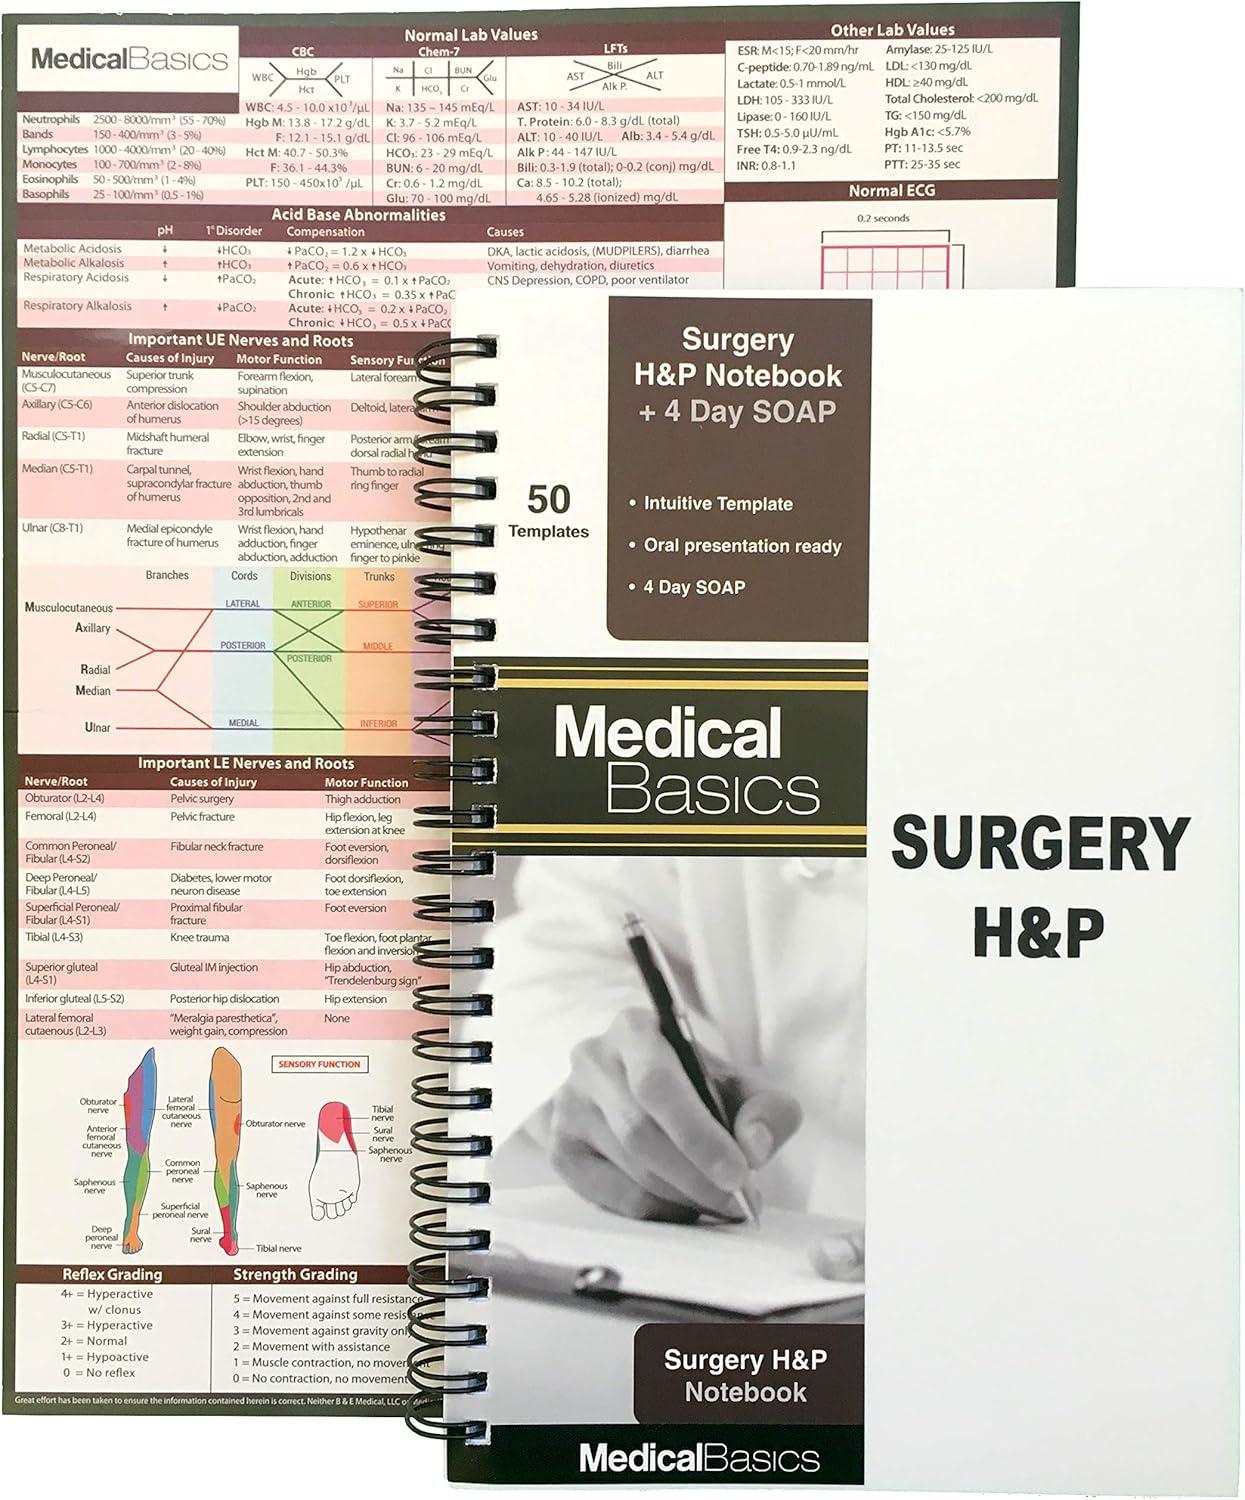
Getting the Most Out of a Surgery Pocket Notebook
You probably already know why you bought one. You wanted something slim you could pull out during a procedure or while rounding without carrying half a textbook. The reality is a bit different. These notebooks work well for quick lookup under time pressure, but they are not designed to teach you a topic from scratch. I learned that pretty quickly during my first year on call. The Surgery Pocket Notebook Series covers the main topics you encounter on surgical rotations: pre-op assessment, perioperative management, common operative procedures, wound care, drain management, and post-op complications. Each entry is structured around bullet points, tables, and short algorithmic flows rather than long prose. That design choice matters because it means the books are optimized for scanning, not deep reading. I tend to keep mine in my white coat pocket for the entire rotation, then switch to a heavier reference once the busy season settles. During the first six weeks, though, the pocket book is basically your only option. The page count stays low enough that it does not weigh down your pocket, and the spiral or lay-flat binding actually survives being tossed into a bag full of pens, a stethoscope, and half-eaten gum wrappers.
What Actually Works in Practice
The most useful feature is the compact drug dosing tables and the post-op order templates. When you are writing admission orders at 11 pm and the attending asks you to include DVT prophylaxis adjustments for renal impairment, flipping through three chapters takes longer than you want to admit. The pocket version usually has a single two-page spread for that. It is not exhaustive, but it gets you started. Another practical detail is the page edges. Some editions leave the outer edge blank, which makes tabbing almost impossible. I stopped trying and instead mark key sections with a fine-line pen directly on the margin. I use red for medication tables and blue for procedural steps. It looks messy to anyone else, but it cuts my search time down to maybe ten seconds per lookup instead of thirty to forty. The complication algorithms are also better than they get credit for. The one on post-thyroidectomy hemorrhage, for example, follows a realistic sequence: assess airway, open the wound at the bedside if the patient is destabilizing, call for help, then proceed to the OR. That last part is important because residents sometimes hesitate before opening a neck wound in the recovery room. The book does not moralize about it. It just lists the steps.
Where These Books Fall Short
The biggest limitation is the depth trade-off. If you need to understand the embryology behind an esophageal atresia repair, this is not the place to find it. The entries assume you already studied the topic elsewhere and just need a memory jog or a quick protocol check. Trying to learn laparoscopic cholecystectomy from a pocket notebook will leave you with a list of indications and a diagram that looks impressive until you actually have to identify Calot triangle anatomy on live tissue. Another issue is the publication lag. Surgical guidelines shift, especially around antibiotic prophylaxis and enhanced recovery pathways. Some editions of this series have not updated their ERAS recommendations in over two years. I noticed the discrepancy when a attending asked me to cite a specific post-op mobilization protocol that contradicted what was printed in the section on colorectal resections. The book still said day-of-surgery mobilization was acceptable in low-risk cases, but the hospital had moved to a standardized early mobilization bundle. I flagged the older edition to the library and kept a current protocol sheet in the back cover pocket instead.
Get the Full Details

How to Choose and Use One Without Wasting Money
Check the copyright date before buying anything secondhand. I once picked up a well-loved copy from a senior resident and realized halfway through the trauma chapter that the damage control resuscitation guidelines were based on an older formulation. That did not make it useless, but it meant I had to verify every transfusion ratio against a current source anyway, which defeats the purpose of carrying a quick reference. If you are deciding between formats, the hardcover spiral versions hold up better than the softcover mass-market ones, but they are also heavier. For actual pocket use, the smaller trim sizes are worth the tradeoff in durability. I have gone through two softcovers on a single rotation before. The spines crack, the pages curl, and the tabs peel off. Buy a cheap plastic sleeve or a clear document pocket to slide over the front cover. It adds about four grams and extends the life by a full rotation. Another small habit that helps is keeping a separate index card in the back with your own personal shortcuts. I write down the local anesthesia volumes I actually use, the phone numbers for radiology and blood bank, and the specific order set template our institution prefers. The printed book gives you the framework. Your card makes it usable in your actual environment.
These notebooks are not the primary learning tool they are sometimes sold as. They are field guides. Use them for lookup, not for learning, and they will save you time on rounds. If you try to build your surgical knowledge around them instead of atlases, guidelines, and case experience, you will run into gaps during exams and eventually during actual cases too. I made that mistake once when I skipped the full chapter on hernia repairs because I thought the pocket summary was enough. It was not. If you want a single starting point, pick an edition that is no more than three years old, check that the appendices include post-op order sets and drug dosing tables, and verify that the local hospital formulary matches the recommendations inside. Everything else is secondary.