What Ovarian Cancer Therapy Actually Looks Like in Practice
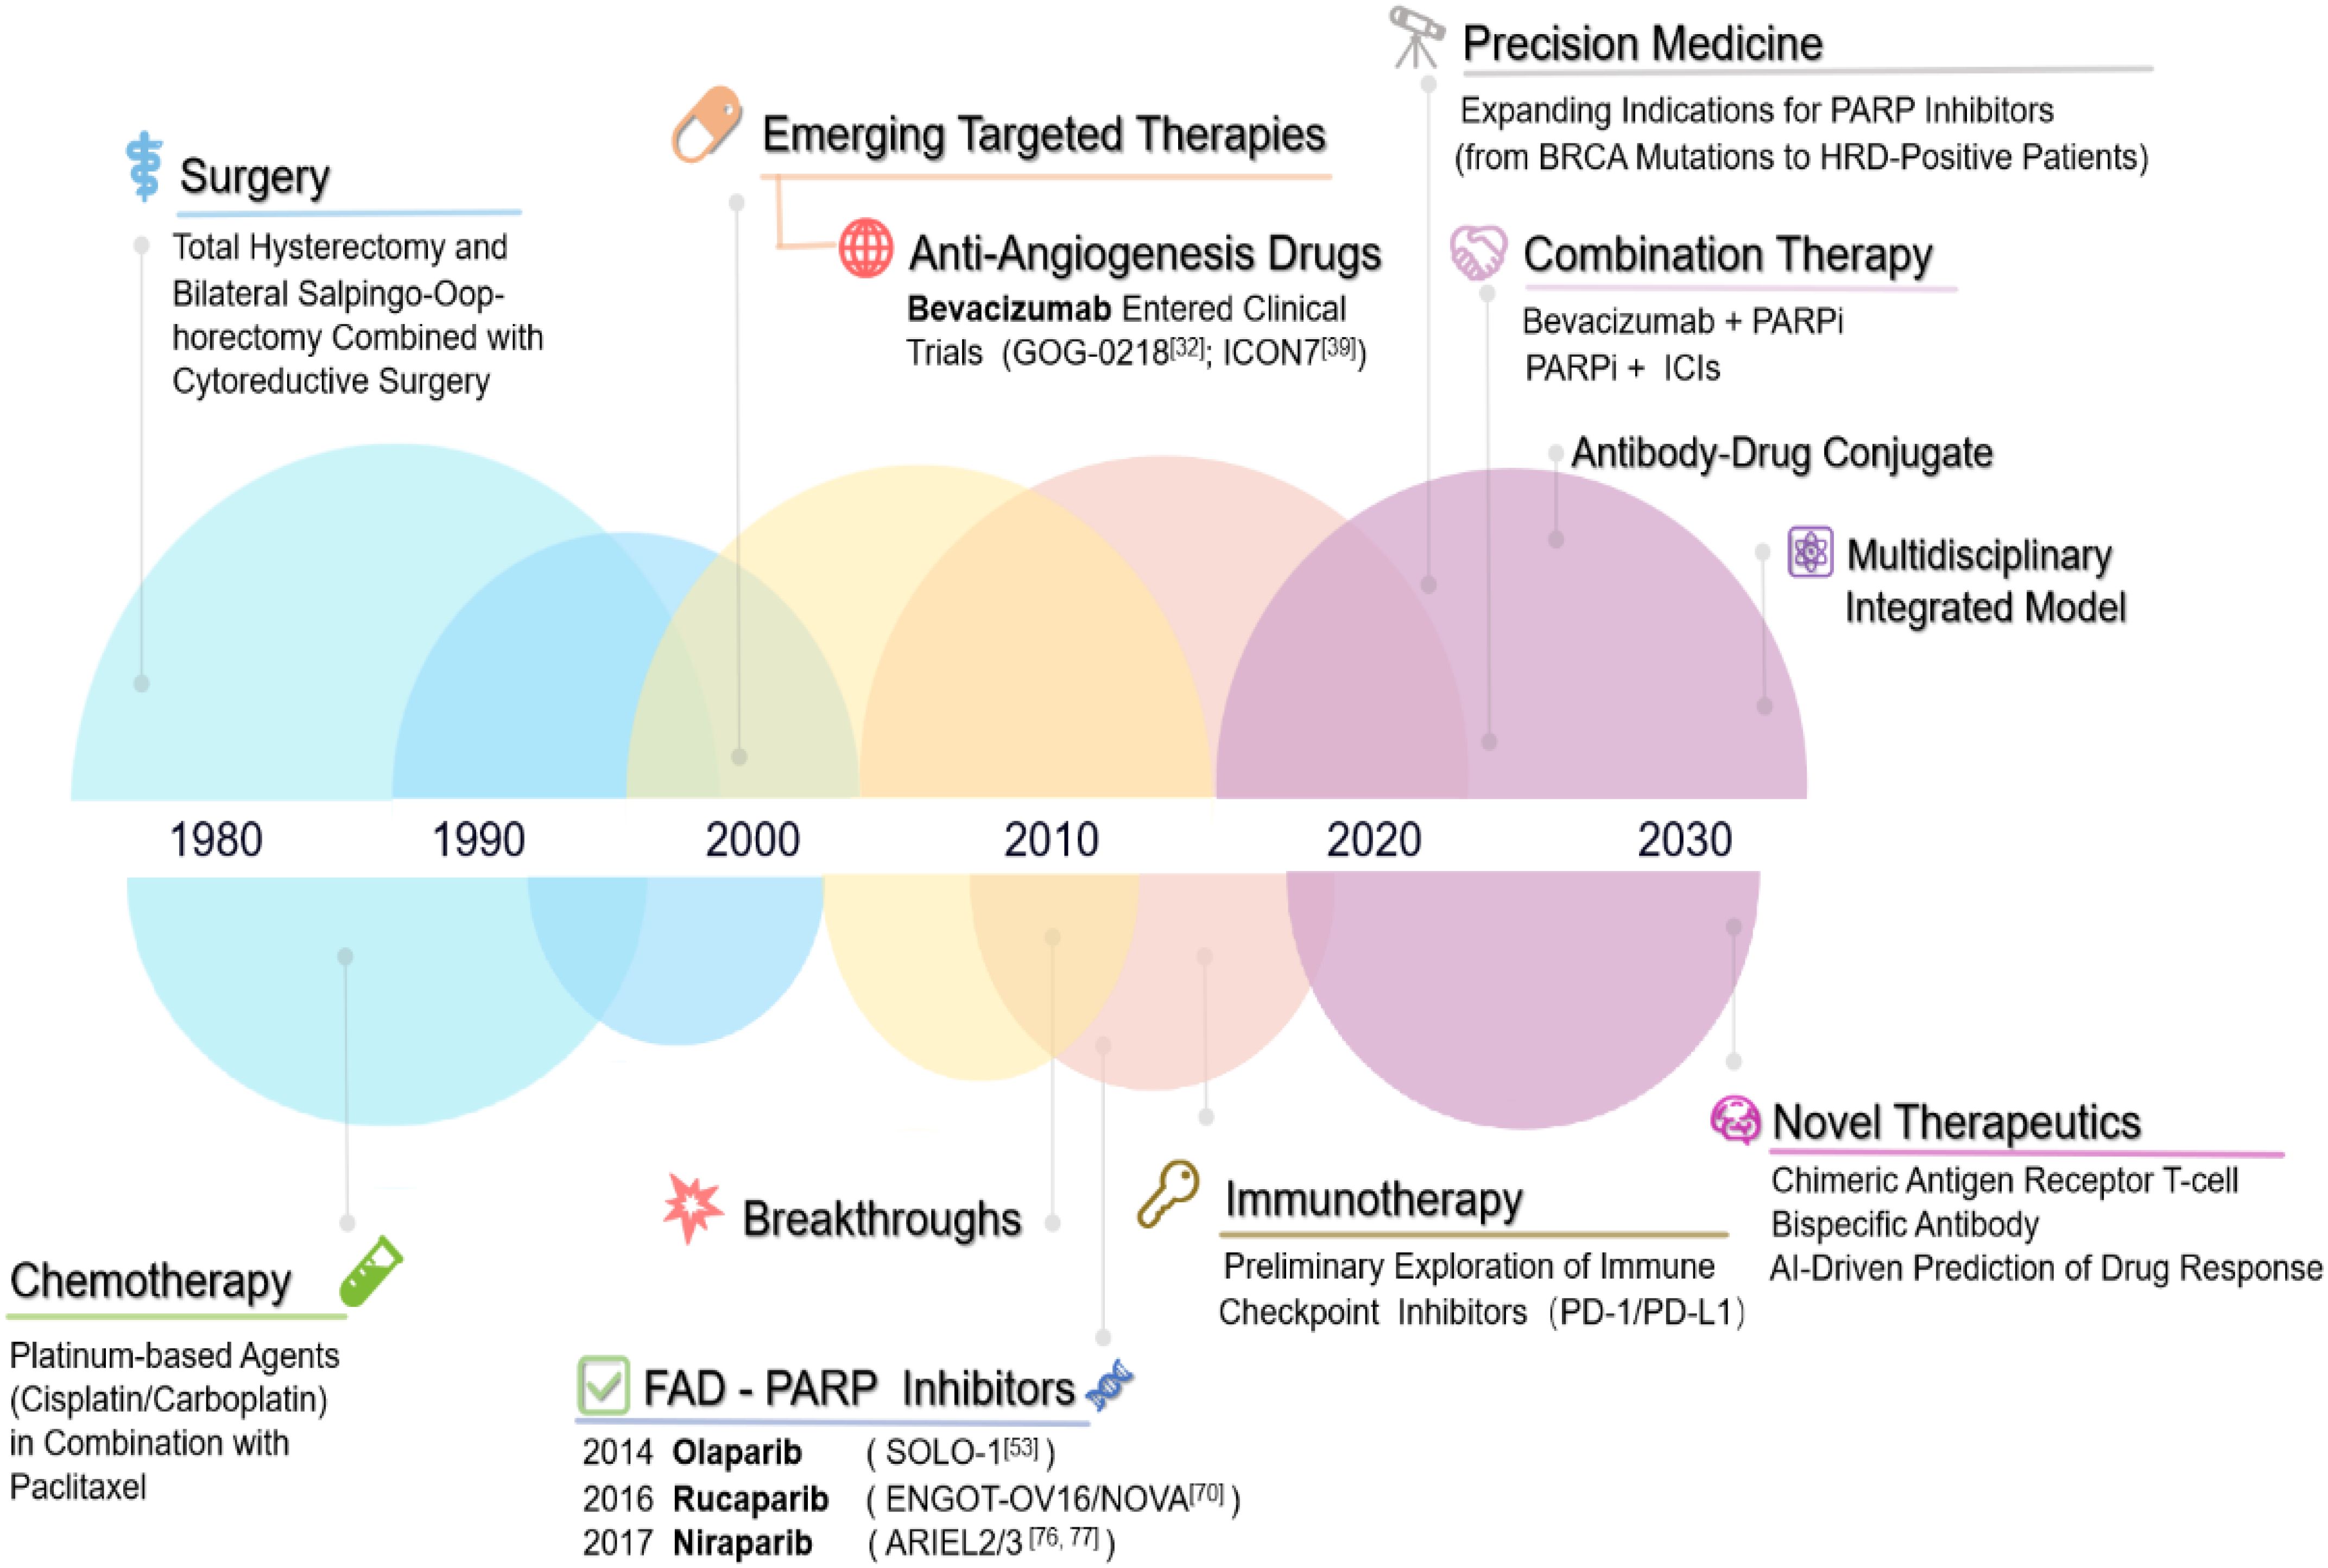
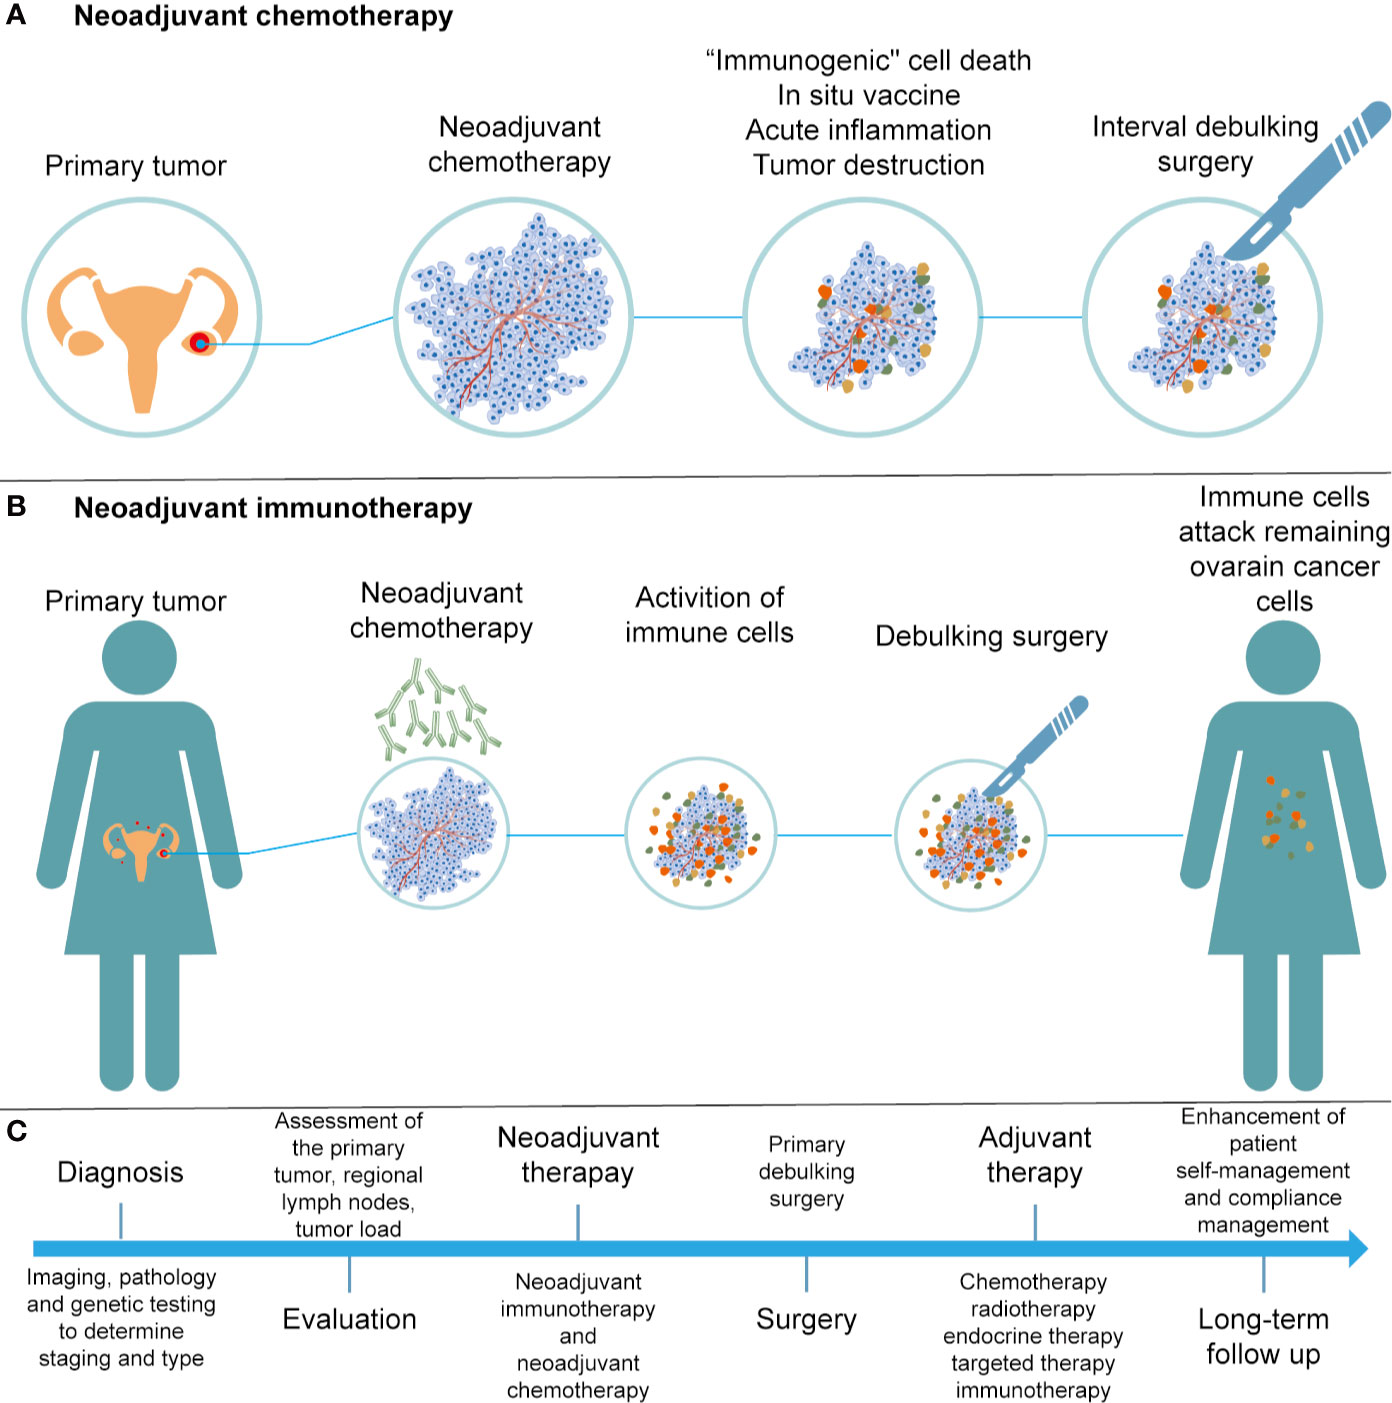
Ovarian cancer isn't one disease. It's several, and the treatment changes dramatically depending on which subtype you're dealing with. I've watched too many people get handed a generic plan that doesn't fit because nobody bothered to check the histology first. Here's how the actual decision-making works. Most patients with epithelial ovarian cancer (that's about 90% of cases) get debulking surgery followed by platinum-based chemotherapy. The carboplatin plus paclitaxel combo is still the backbone, given every three weeks for six cycles. That's been the standard since the late 1990s. It hasn't changed as much as people think. Where it gets complicated is the debulking part. Residual disease after surgery is the single biggest prognostic factor. If your surgeon leaves more than a centimeter of tumor behind, your outcomes drop significantly. I've seen cases where patients were sent to general gynecologic oncologists who weren't comfortable doing radical cytoreduction, and the difference in survival between optimal and suboptimal debulking is measured in months, not weeks. Get to a high-volume center if you can. Really. This isn't motivational language. It's data.
Things Nobody Tells You About Treatment
Here's what the pamphlets don't cover. BRCA mutation testing isn't optional anymore. It should be done on every ovarian cancer patient regardless of family history, and I mean every single one. A positive BRCA result opens up PARP inhibitor maintenance therapy, which has become a game-changer for progression-free survival. Olaparib, rucaparib, niraparib — these aren't theoretical anymore. They're standard of care for BRCA-mutant patients after response to platinum chemo. But here's the catch that trips people up: PARP inhibitors only work if you've actually responded to platinum first. If your disease is platinum-resistant, throwing olaparib at it won't help. You need to be platinum-sensitive, meaning your cancer came back more than six months after finishing chemo. That window matters. A lot. I had a patient last year — Stage IIIc, high-grade serous carcinoma, BRCA2 positive. She did well on surgery and six cycles of carboplatin/paclitaxel. Perfect response on scans. We started her on olaparib maintenance. Eight months in, her CA-125 started creeping up. Not dramatically, just from single digits to the high teens. She panicked. I panicked a little too, honestly, because this is exactly when you wonder if the drug stopped working or if it's just noise.
Here's what we learned from that situation: CA-125 fluctuations of that magnitude during PARP inhibitor maintenance don't necessarily mean progression. We repeated the scan at four weeks instead of waiting two months, and it was stable. The workaround was simple — don't overreact to small CA-125 moves while on maintenance therapy. Establish your own baseline after the first few months, and look for sustained upward trends, not isolated bumps. This is something most patients aren't told explicitly enough.
Get the Full Details

Platinum-Resistant Disease: Where It Gets Messy
If your cancer comes back within six months of finishing platinum chemotherapy, you're in the platinum-resistant category. This is where treatment options thin out fast. Re-challenging with the same platinum regimen rarely works. The tumor has already shown it can handle it. The usual go-to is single-agent chemotherapy: pegylated liposomal doxorubicin, gemcitabine, topotecan, or docetaxel. Response rates are modest, maybe 15 to 25%. You pick based on your prior toxicity profile. If paclitaxel gave you bad neuropathy, you probably don't want more taxanes. If your kidneys are shot, topotecan is out. These decisions are more art than science. Bevacizumab (Avastin) can be added to chemotherapy in the recurrent setting and improves progression-free survival by a few months on average. But it doesn't touch overall survival, and it has its own problems — hypertension, proteinuria, rare but serious bowel perforations. I've seen two cases of bowel perforation in patients on bevacizumab who also had significant residual disease near the bowel. It's a real risk, not just a box on the side effects list.
The Immunotherapy Question
Immunotherapy in ovarian cancer has been disappointing so far. Checkpoint inhibitors like pembrolizumab show activity only in the tiny subset of patients with MSI-H or TMB-high tumors, which is maybe 3 to 5% of ovarian cancers. If your tumor isn't in that category, you're basically gambling with no guaranteed payoff and real side effects to manage. I mentioned this to a patient last spring who was desperate for anything new after two lines of chemo failed. She'd been reading about immunotherapy trials online. I was honest with her: the odds aren't in her favor for standard ovarian cancer. She asked if she should try anyway. I told her to consider a clinical trial instead, where she'd at least get close monitoring and access to combinations that aren't available through standard channels. That's the better move most of the time.
Maintenance and Monitoring
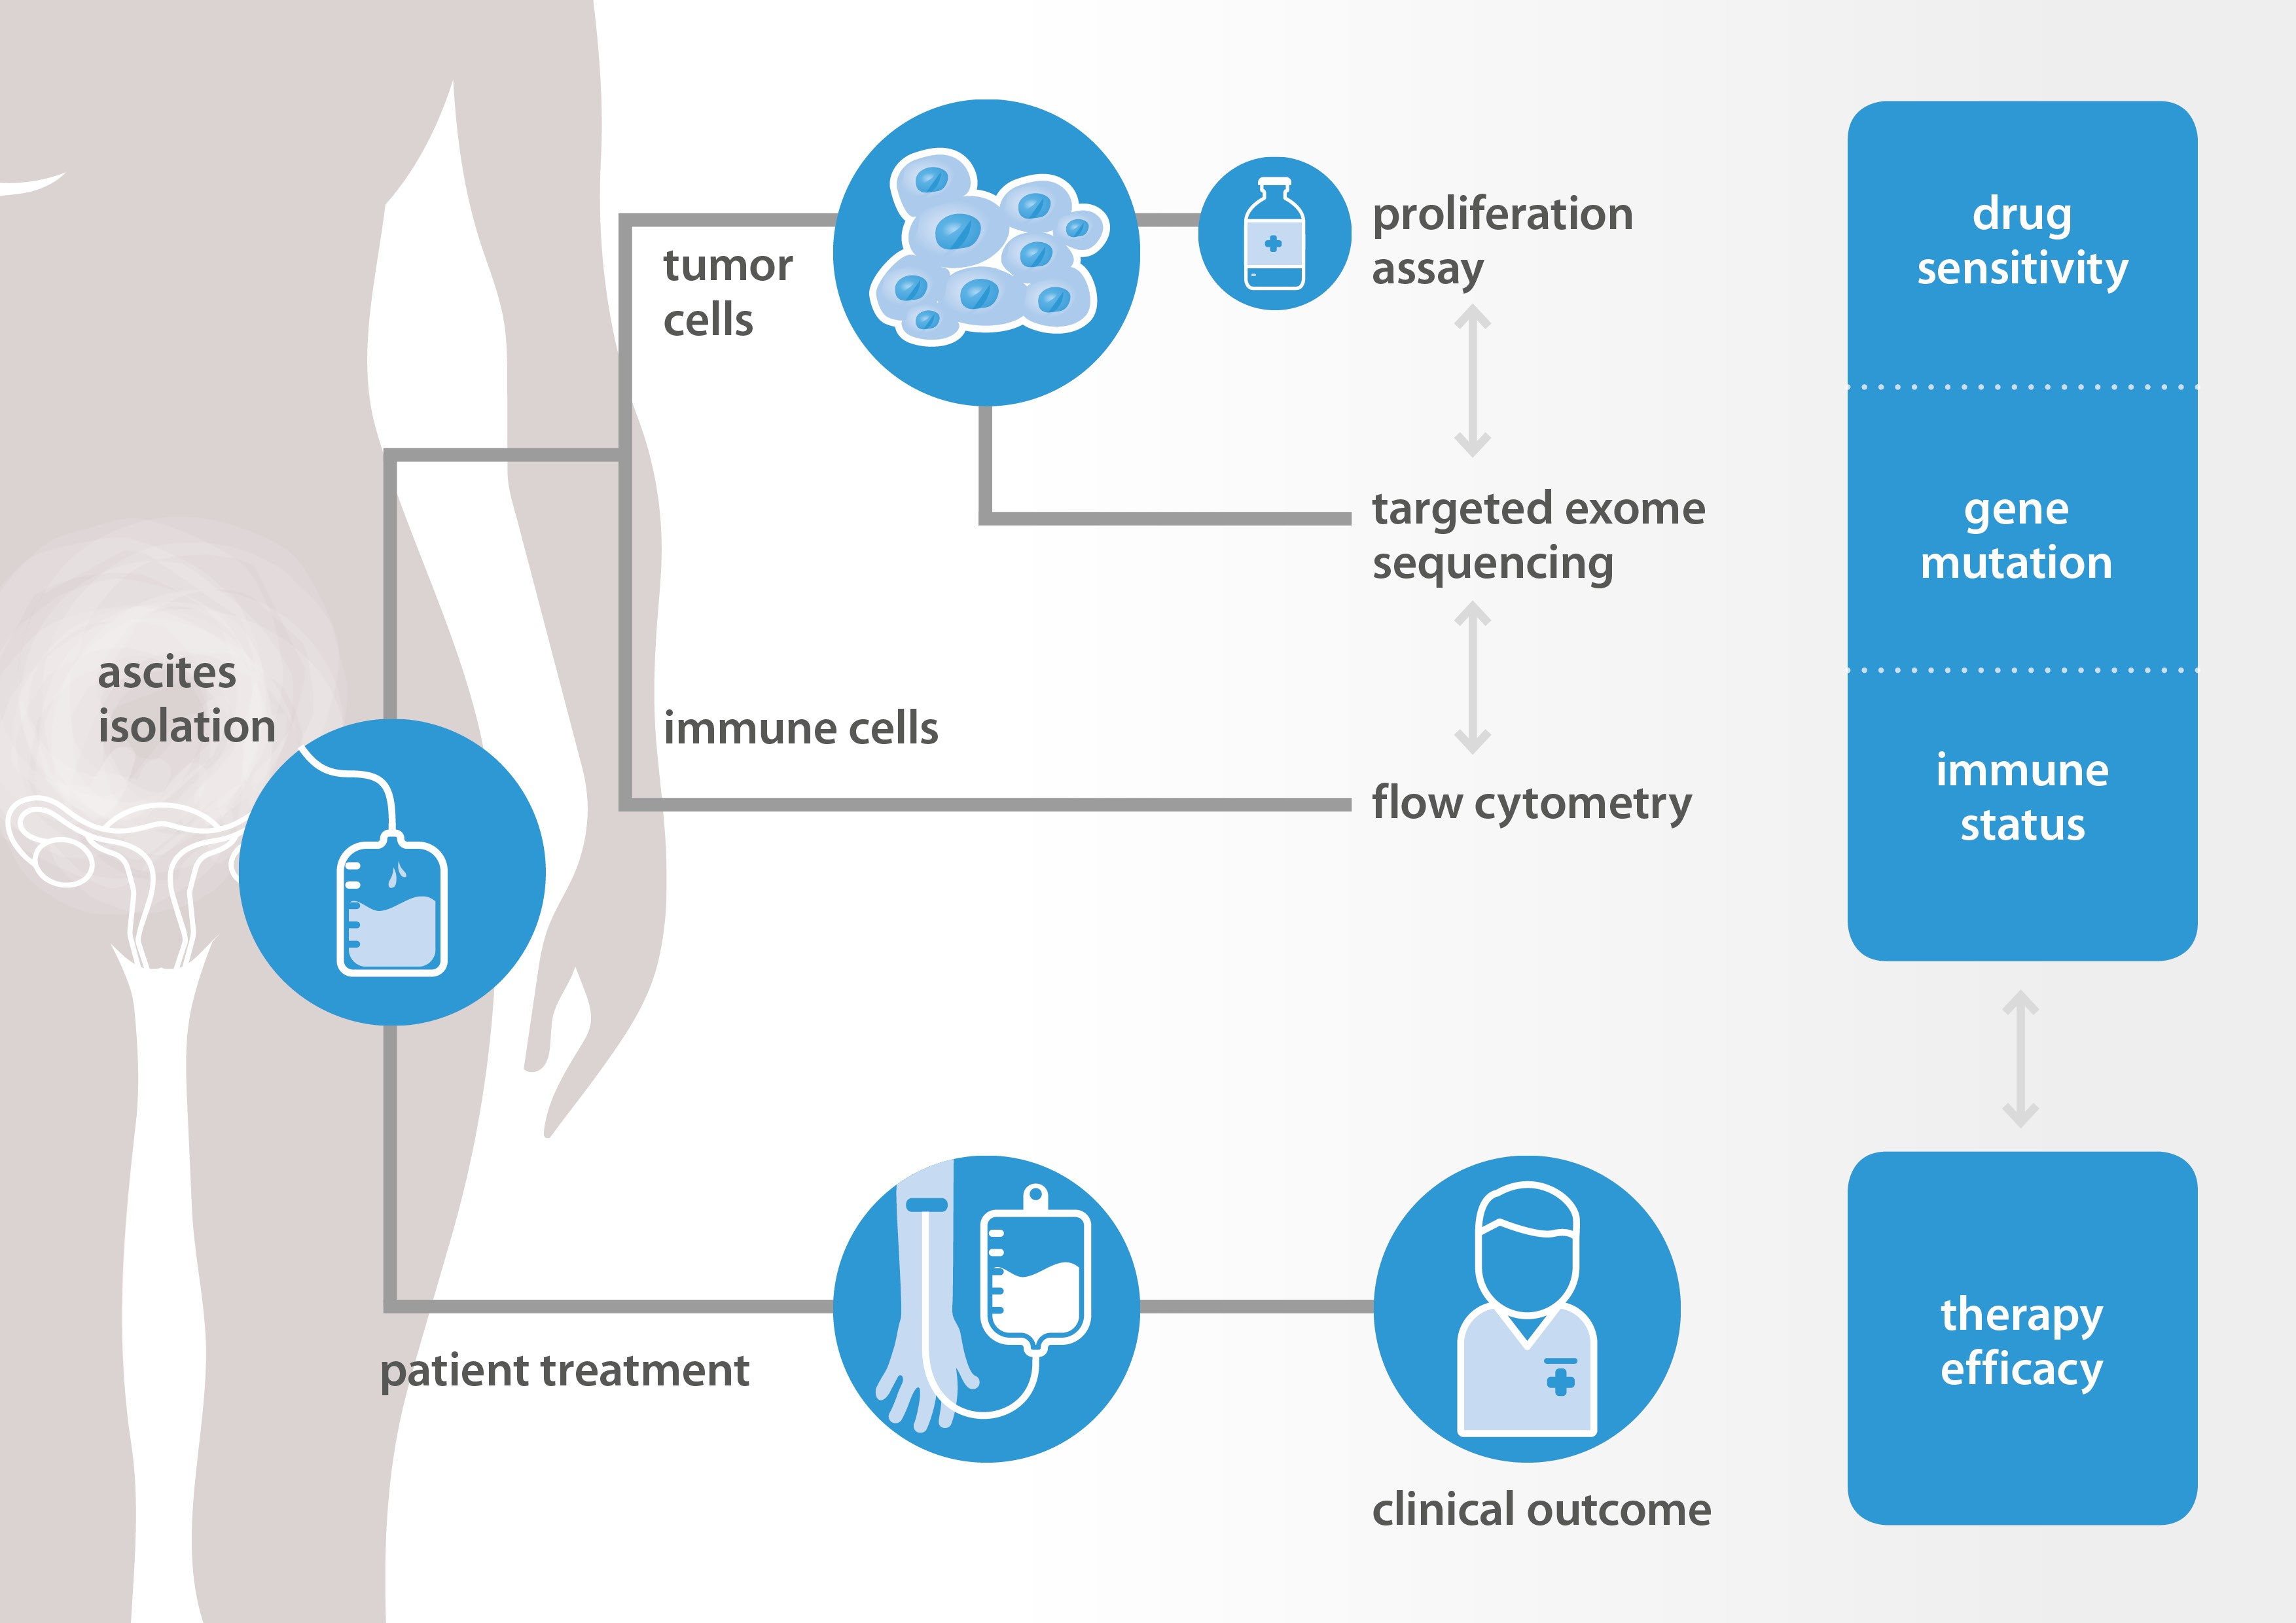
After active treatment ends, you're on surveillance. Every two to three months for the first two years, then every three to six months until year five, then annually. CA-125 at every visit, physical exams, and imaging only if symptoms or marker elevations suggest recurrence. Don't get excessive CT scans just because you want to know. The data doesn't support earlier detection improving outcomes in asymptomatic recurrence. And yes, recurrence is likely. Even with optimal treatment, about 70 to 80% of Stage III patients will recur. That's not something you hear in the initial conversation with your oncologist, but it's worth knowing going in. It changes how you think about treatment decisions — whether you're aggressive upfront or conservative, whether you're a candidate for clinical trials at diagnosis rather than waiting until recurrence. If you're newly diagnosed and want to discuss PARP inhibitor options or clinical trial availability, make sure your oncologist runs comprehensive genomic profiling, not just BRCA1 and BRCA2. Homologous recombination deficiency testing matters too, and it's becoming increasingly relevant for treatment decisions beyond just BRCA-mutant patients.