Reading thumb radiographs isn't as straightforward as most people think
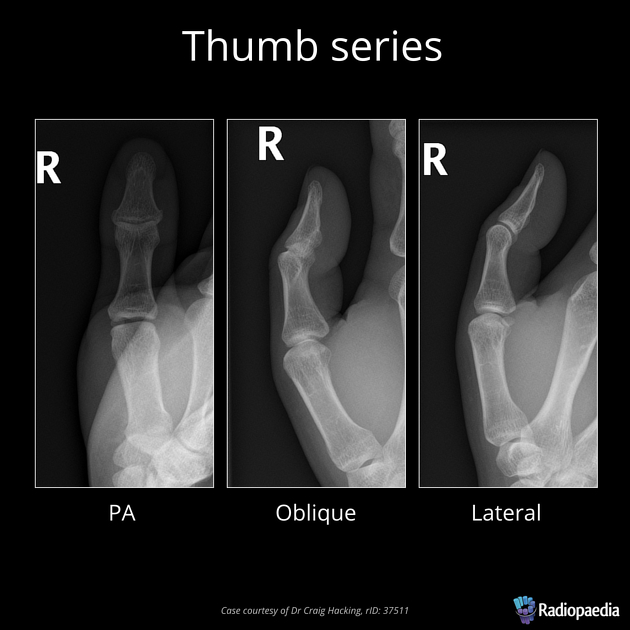
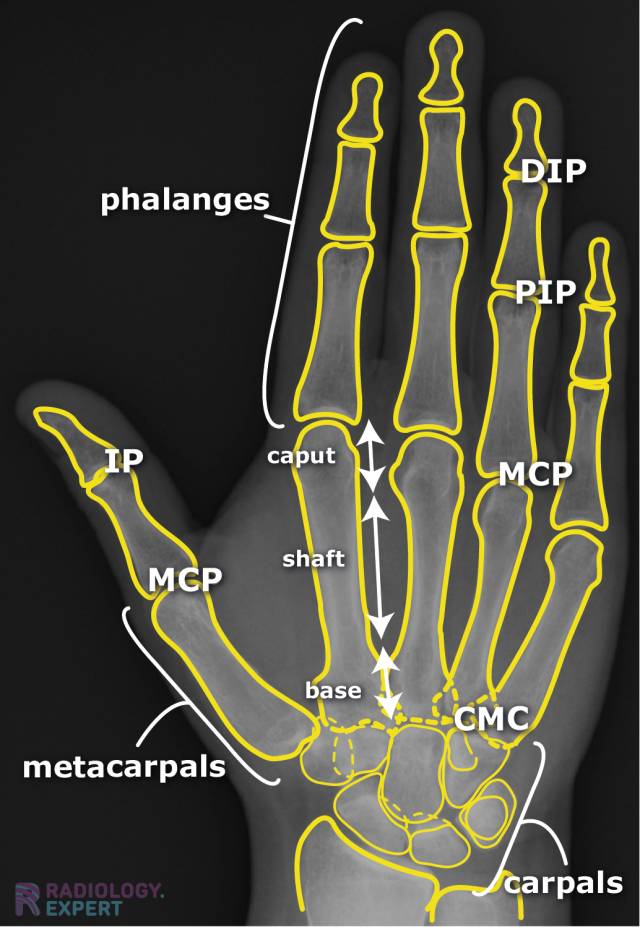
The first ray of the hand gets way more attention than it should because it's clinically important, not because it's particularly interesting anatomically. When you're learning to interpret thumb x-rays, you'll probably waste a few weeks memorizing the phalanges and metacarpal like they're some grand puzzle. They're not. There are really only two phalanges in the thumb, the proximal and distal, plus the first metacarpal and then the trapezium which forms the saddle joint. That's basically it for bones that matter on a routine study. Most people starting out mess up the AP view because they position the hand wrong. Lay the palm flat, spread the thumb away from the fingers, and make sure the beam is perpendicular to the metacarpophalangeal joint. If the patient can't abduct the thumb due to pain, don't force it. Just rotate the hand slightly and accept a mildly oblique image rather than a non-diagnostic one. I've seen too many missed scaphoid fractures because someone was too rigid about positioning. The lateral view is where things get interesting. The proximal phalanx should overlap the metacarpal head about halfway. If it's completely lateralized, you're looking at a rotated image that will mislead you. In practice, I usually just look for three things: alignment of the joint surfaces, cortical continuity along the volar and dorsal lines, and the shape of the trapezium. Everything else is detail work.
Here's something beginners miss. The sesamoid bones at the MCP joint of the thumb are almost always present bilaterally, and they're frequently mistaken for fragmentation or avulsion fractures. I had a case last year where a resident called me at 11pm because a film showed what looked like a distal phalanx fracture. We looked at it together and it was just hypertrophic sesamoids. The trick is checking the contralateral side. If it's there on both thumbs, it's normal anatomy. Simple but not always obvious under time pressure. The first dorsal interosseous muscle bulk creates a soft tissue shadow that can obscure the ulnar aspect of the metacarpal. On poor quality images or in obese patients, you might miss a subtle buckle fracture along the radial border of the first metacarpal. I learned this the hard way when a six-year-old presented with tenderness over the radial thumb after a fall and the initial reading came back negative. I repositioned the thumb in a true AP with the beam angled slightly caudal and spotted a non-displaced fracture through the metaphysis. The initial radiographer had centered the beam too medially.
Common pitfalls and practical workarounds
Benign cheiromegaly or thick soft tissue at the thenar eminence can make the first metacarpal shaft appear wider than it actually is. This is normal. Don't report pseudo-fractures based on soft tissue prominence alone. The cortex should be smooth and continuous regardless of how much fat surrounds it. Stiedke's disease involves an os styloideum, which is a small accessory ossicle at the base of the proximal phalanx. It appears in roughly 1-3% of the population and sits right next to the trapeziometacarpal joint. On a routine PA view it looks suspiciously like a fracture fragment. The workaround is a dedicated bone window on the digital viewer and comparison with the other thumb if available. When in doubt, a single oblique view will separate the accessory bone from the underlying cortex. Roentgenograms have real limitations. You cannot reliably assess ligamentous injury on plain films unless there's an associated avulsion. Scapholunate ligament tears, for example, won't show up on x-ray unless you do stress views. Even then, sedation or analgesia often prevents adequate stress. MRI or ultrasound is the appropriate next step when clinical suspicion is high and the films are unremarkable. I tell people this upfront because it saves everyone time. Ordering an MRI immediately after a negative x-ray when a ligament tear is suspected is standard practice, not over-testing.
Get the Full Details
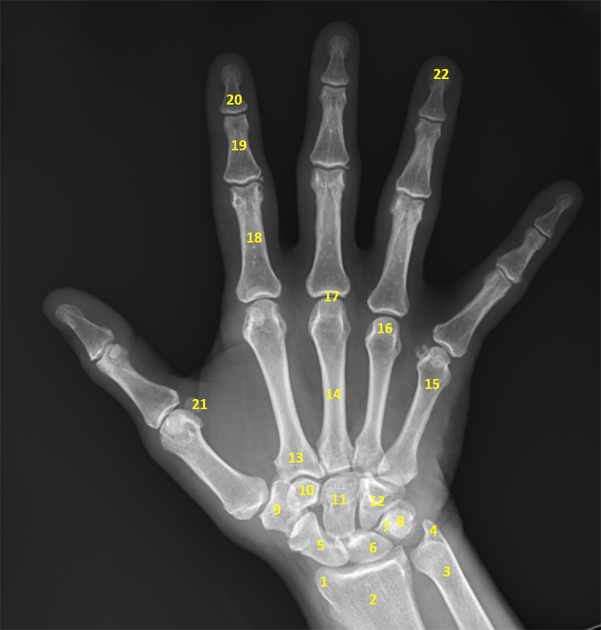
The trapezium is easy to miss on routine imaging because it sits behind the first and second metacarpal bases. A dedicated trapezial view with the hand pronated and the beam angled 15 degrees cephalad will open that space. I use this routinely when evaluating carpometacarpal osteoarthritis in older patients. The joint space narrowing is best appreciated on that projection. Standard PA views compress the trapezium into the metacarpal shadows and make assessment nearly impossible.
When imaging doesn't tell the whole story
Cortical bone shows up well on x-ray. Trabecular bone does not, not reliably at least. Early osteomyelitis or a stress reaction in the proximal phalanx may not alter the cortical outline for 10 to 14 days. If you have a patient with localized tenderness and a normal initial film, repeating the x-ray in two weeks or getting an early MRI will catch what the plain film misses. This is well established but still underutilized in urgent care settings where the incentive is discharge, not thoroughness. For pediatric patients, the carpals are largely cartilaginous until around age six. The trapezium and trapezoid ossification centers appear at different ages, which means a child's thumb x-ray looks dramatically different at age four than at age eight. Don't confuse delayed ossification with dislocation. Reference charts exist for this, but the practical approach is to look for symmetry. Asymmetric findings warrant further investigation regardless of what the chart says about expected age of appearance. I keep a pocket reference with the key measurements for the first dorsal interosseous space and the thenar eminence thickness because these landmarks come up more often than you'd expect in trauma evaluations. Knowing normal variants prevents unnecessary follow-up imaging and keeps the reading time reasonable. Most thumb x-rays turn out fine. The ones that don't are the ones worth spending extra time on.