Getting The Tinetti Done Right
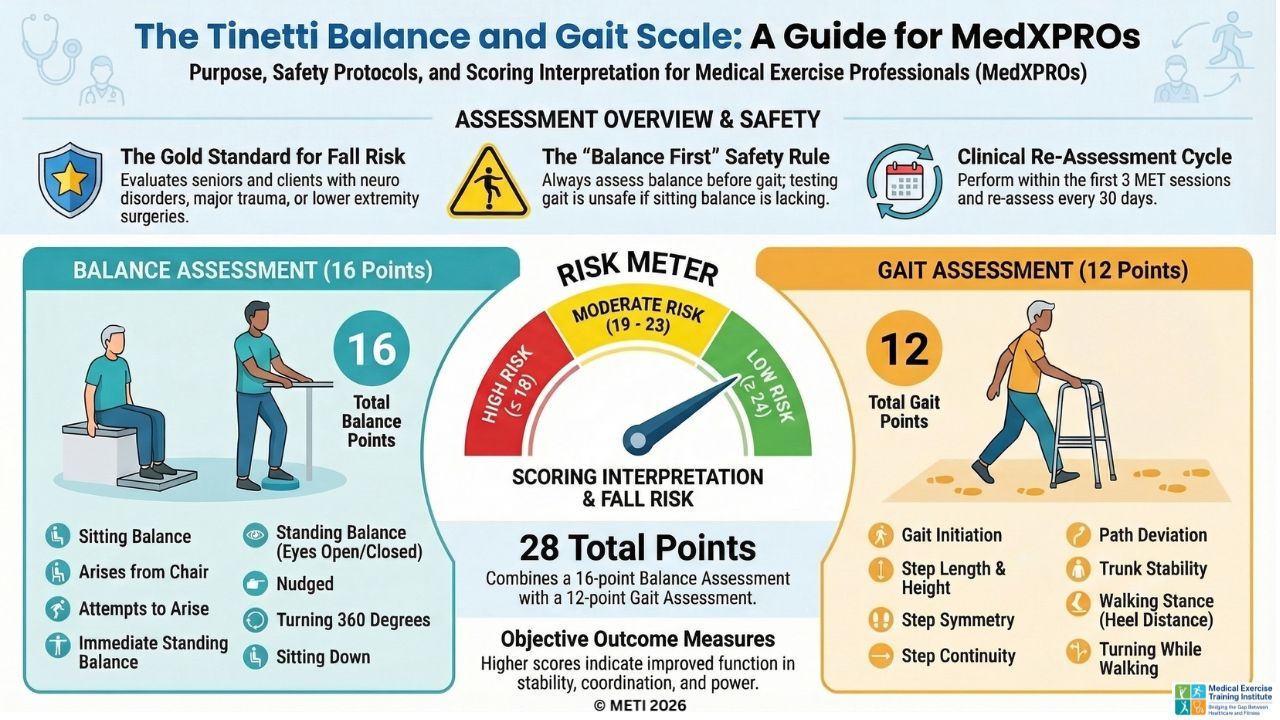
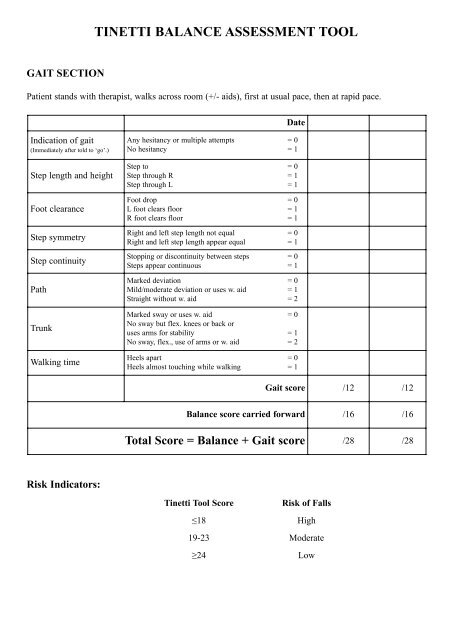
The Tinetti Balance And Gait Assessment is one of those tools that looks simple on paper and drives you slightly insane in practice. It measures fall risk in older adults through a series of balance and gait tasks, scored out of 16 for balance and 12 for gait, with a total possible score of 28. Scores below 19 indicate high fall risk, between 19 and 24 suggest moderate risk, and 25 to 28 is generally considered low risk. That part is standard textbook knowledge. The actual administration is where things get messy. You need a quiet corridor or clinical space, a standard chair, a tape measure, and a stopwatch. The patient should be wearing appropriate footwear and clothing that allows free movement. You do not need any specialized equipment beyond basic clinic supplies. Here is how the balance section works: you observe the patient through a series of tasks including sitting to standing, transitioning from sitting to standing without using their arms, reaching forward while seated, turning 360 degrees, placing an object on a shelf, and picking up a shoe from the floor. Each task is scored 0 to 2 based on independent performance, safety, and quality of movement. The gait section evaluates stance width, initiation of gait, step length and height, continuity of stride, path deviation, and trunk posture while walking. Again, each item scores 0, 1, or 2. The whole assessment takes roughly 15 to 20 minutes if the patient cooperates and has no major mobility limitations. If the patient is fatigued, anxious, or confused, plan for 30 minutes minimum. Rushing through it defeats the purpose entirely. You are looking for qualitative movement patterns, not just ticking boxes.
I ran into a specific problem recently with a patient who scored unexpectedly high on the balance portion but walked with a wide base and shuffling gait during the gait section. Her balance score was 14 out of 16, which would normally signal low risk. Her gait score was 7 out of 12. The discrepancy confused the initial read. What I discovered was that she had learned to use compensatory strategies specifically for the static and supported tasks — she gripped the chair edge tightly during transfers and used her arms heavily to push up. The scoring sheet allowed this because it technically permitted arm assistance in one sub-item, but the compensation masked underlying weakness. I adjusted my observation by having her repeat the sit-to-stand without arm use, which dropped her score on that item and gave a more honest picture. The lesson is straightforward: watch for learned compensations. Patients will often perform better than they actually can when they sense what you want to see.
Common Pitfalls That Skew Results
The biggest mistake people make is scoring based on what the patient attempts rather than what they actually accomplish. If a patient tries to turn 360 degrees but grabs the wall mid-turn and completes it slowly with three separate steps, that is a 1, not a 2. Beginners routinely give full credit for partial performance because they want to be encouraging or they are simply not watching closely enough. Another issue is the environment. A slippery floor, uneven surface, or nearby obstacles will artificially depress scores. I once had a patient score a 12 on the balance section in a narrow hallway with oxygen tubing running along the ground. When we repeated the assessment in the empty therapy gym with the tubing removed, her score jumped to 15. The environment alone accounted for a three-point difference, which is clinically significant. Always document the testing conditions. Cognitive impairment is a third confounding factor. The Tinetti relies on the patient understanding and following instructions. A patient with early dementia may perform the physical tasks adequately but fail to follow directions, resulting in an artificially low score that reflects cognition rather than true motor ability. In these cases, the assessment loses discriminative validity. I have started noting cognitive status alongside the score whenever a patient has a known diagnosis, and I occasionally supplement with the Mini-Cog or MoCA when the discrepancy between cognitive and motor performance seems large.
Get the Full Details

Tinetti Balance And Gait Assessment Scoring Nuances
The scoring criteria for gait are particularly finicky. Stance width, for example, is scored as normal (1) if the feet are shoulder-width apart during standing and walking, wide (2) if the patient holds a consistently wide base, and unsteady (0) if the stance is irregular or the patient appears unstable. Most clinicians default to scoring "wide" when they see a wide base, but the distinction between wide and unsteady matters. A wide base that is stable and controlled scores differently from one that wobbles. You have to actually watch the patient stand still for a few seconds before asking them to walk to make this call. Initiation of gait is another tricky item. A delay of more than five seconds between "start walking" and the first foot movement scores 0. A brief hesitation of one to five seconds scores 1. Immediate stepping scores 2. The five-second cutoff is arbitrary but clinically useful. I have seen patients who hesitate just under five seconds score a 1 and those who take five point one seconds score a 0, which makes the boundary feel almost meaningless in borderline cases. Still, it is the standard, and you apply it consistently. One counter-intuitive thing most people miss is that a lower score does not always mean worse function. The Tinetti is norm-referenced within specific populations, and a score of 20 in a frail nursing home population may carry different prognostic weight than a score of 20 in a community-dwelling older adult. The absolute number matters less than the trajectory and the context. I track scores over time for my regular patients. A drop of two points between visits is more meaningful than a single isolated assessment.
Limitations You Should Know About
The Tinetti has well-documented limitations. It is insensitive to subtle changes in patients with Parkinson's disease because the gait items do not capture freezing, postural instability specifics, or the fluctuating nature of PD mobility. These patients often score in the moderate risk range despite experiencing frequent falls that the assessment does not predict well. For Parkinson's patients, I supplement with the Parkinson's Disease Falls Scale or the Timed Up and Go test, which captures dynamic stability better. It is also limited in patients with significant lower extremity amputations or prosthetic users. The balance items assume bilateral lower limb function, and prosthetic users may compensate in ways the scoring system does not account for. I flag these cases and interpret scores cautiously, often relying more on functional mobility measures than on the absolute Tinetti number. The assessment assumes a certain level of verbal comprehension. Non-English-speaking patients, patients with hearing loss, and patients with aphasia require modified instruction techniques, and the reliability drops in these populations. I use visual demonstration and simplified language, sometimes involving a family member or interpreter, but I acknowledge that the standard norms may not apply.
Where To Get The Official Form
The original Tinetti Performance-Oriented Mobility Assessment was published by Mary Tinetti in 1986 and the materials are distributed through various clinical resource sites. You can find the scoring sheet and instruction manual through the Tinetti Assessment Instruments website or through professional organizations like the American Physical Therapy Association member resources. Some university physiotherapy departments also host free copies. I recommend downloading the version that includes the detailed administration video or written protocol rather than relying on memory. The differences between the published protocol and what people routinely do in practice are small but accumulate into scoring drift over time. If you are looking for a quick reference printable, the CDC's STEADI initiative offers a free implementation toolkit that includes a Tinetti scoring sheet adapted for electronic health record integration. It is not the original but it covers the same items and is freely available for clinical use.

Practical Tips For Consistent Administration
Standardize your setup. Always use the same chair, the same starting position, and the same verbal cues. "Stand up when you are ready" is better than "Go ahead and stand up now" because the former gives the patient control and the latter introduces social pressure that can alter performance. I use a scripted set of instructions for every patient to reduce variability. Record the score immediately after each item, not at the end of the assessment. Memory fades quickly, and patients often look at you expectantly after completing a task, which can influence your scoring if you wait. Write 0, 1, or 2 as you go and double-check only if you are uncertain about a borderline case. Pay attention to the patient's anxiety level. A nervous patient will move stiffly and score lower on items that actually measure confidence and smoothness of movement. I sometimes allow a brief rest period between the balance and gait sections for patients who appear visibly stressed. This does not invalidate the assessment and often improves the quality of the data.
Document assistive device use. If the patient uses a walker or cane during the gait section, note it. The standard protocol recommends performing the gait items with the patient's usual assistive device, but some clinicians administer without it to assess baseline ability. Either approach is valid as long as you document which method you used and communicate it clearly to whoever reads the score later. The Tinetti remains useful precisely because it is simple. It is not a perfect predictor of falls, and it has blind spots, but it provides a consistent, repeatable snapshot of mobility function that most clinicians can administer without specialized training. The value is in the consistency of administration and the comparison across visits, not in treating any single score as a definitive verdict. Use it as one data point among many, track changes over time, and do not ignore the qualitative observations you make while watching the patient move. Those observations usually tell you more than the final number ever will.