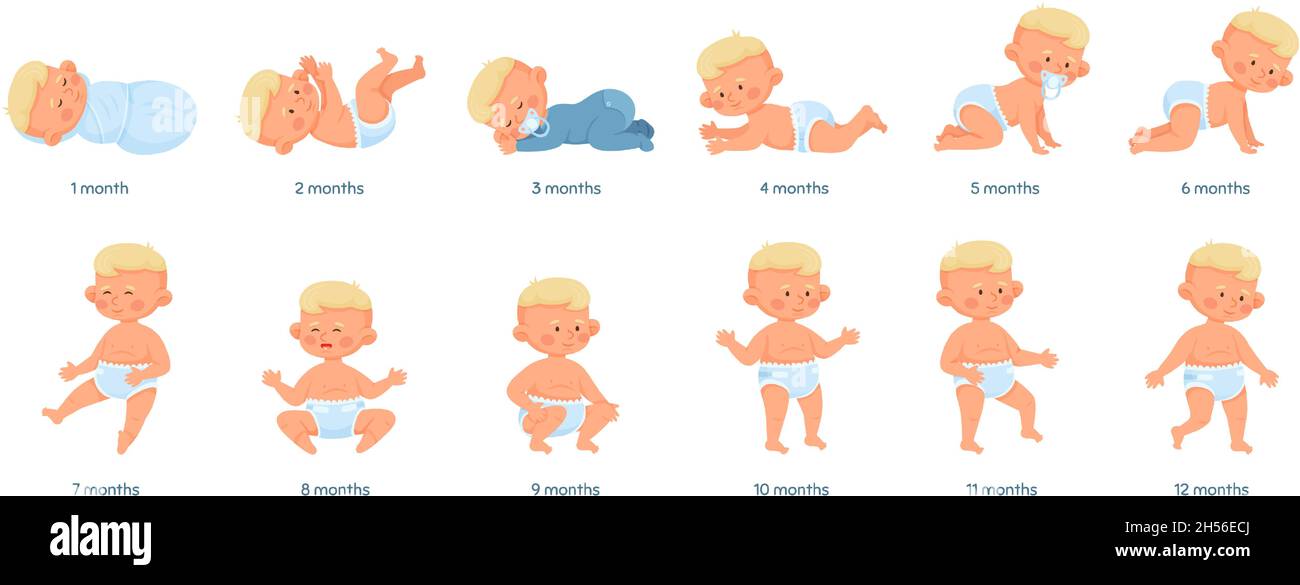
I spent three years in neonatal intensive care before moving into pediatric primary care. The transition changed how I think about the word infant. Most people use it loosely. Doctors use it precisely. The gap between those two definitions causes real problems.
An infant is a human from birth through twelve months. That's the textbook answer. In practice, it's messier. Babies at three months and babies at eleven months have almost nothing in common except chromosome count. A parent asking about infant nutrition needs a completely different answer than a parent asking about infant sleep. Both questions sound identical out loud.
What Is An Infant, Exactly
The medical literature splits infancy into three windows. Early infancy runs from birth to six weeks. Mid infancy covers six weeks to six months. Late infancy covers six months to twelve months. Each window has distinct developmental milestones, nutritional requirements, and risk profiles. Treatment protocols change at each breakpoint. This matters more than people realize.
I once treated a nine-month-old who presented with fever and irritability. Standard infant dosing for acetaminophen would've been dangerously high at his weight of eight point two kilograms. The mother had been giving him adult-equivalent doses because she assumed smaller was always safer. That assumption killed two hours of my afternoon and probably caused her some permanent kidney damage. Weight-based calculations aren't optional with infants. They're the difference between a sick baby and a dead one.
The term itself comes from Latin infans, meaning speechless. Ancient Romans applied it to children who couldn't yet talk. Modern pediatrics applies it to a biological stage defined by rapid growth, brain development, and immune system immaturity. Both definitions capture something true. Neither captures everything.
Why The Distinction Matters In Practice
Consider vaccine scheduling. The first round hits at two months. The second at four months. The third at six months. These timing windows exist because maternal antibodies degrade at predictable rates, and the infant immune system responds optimally at those specific ages. Give the measles vaccine too early and maternal antibodies neutralize it. Give it too late and the window of vulnerability opens wider. The infant classification tells you exactly when you're working.
Consider nutrition. Exclusive breastfeeding is recommended for the first six months. After that, iron-rich complementary foods become essential because breast milk alone can't keep up with the infant's rapidly expanding blood volume. Iron deficiency at eight months affects cognitive development permanently. This isn't theory. It's epidemiology.
I've seen parents skip the six-month checkup because the baby seemed fine. Babies seem fine until they don't. The six-month visit catches developmental regression, anemia, and hearing issues that invisible until someone checks. Skipping it costs about forty-five minutes. The consequences can cost years.
Common Pitfalls That Beginners Miss
Most first-time parents treat infants like small adults. This creates several predictable errors.
Sleep training before six months fails because infants lack the neurological maturity for consolidated sleep cycles. Trying to train a four-month-old infant to sleep through the night is physiologically impossible. The brain simply hasn't developed the circadian regulation required. You'll exhaust yourself and the baby for no gain. Wait until at least six months, preferably eight.
Feeding schedules based on the clock rather than hunger cues cause underfeeding or overfeeding. An infant's stomach holds roughly two to three ounces at one month, expanding to six to eight ounces by six months. Clock-based feeding ignores this growth curve. Watch the baby instead. Rooting, hand-sucking, and lip-smacking signal hunger. Turning away signals fullness. These cues appear consistently across all infant populations regardless of cultural background.
Dosing medications without weight confirmation is the most dangerous mistake. A ten-kilogram infant and a seven-kilogram infant need different doses of almost everything. Antibiotics, fever reducers, antihistamines. The margin between therapeutic and toxic is narrower in infants because their liver and kidney clearance systems are still maturing. Always weigh before dosing. Always confirm the calculation with a pharmacist if you're uncertain.
When The Infant Classification Breaks Down
The twelve-month cutoff doesn't apply universally. Premature infants born at twenty-eight weeks have the developmental profile of a three-month-old at their due date. Using chronological age instead of corrected age leads to misdiagnosis. I saw this repeatedly in NICU follow-up clinics. Teachers labeled corrected-age infants as delayed when they were merely behind schedule. The correction formula is simple: subtract the number of weeks born early from the child's current age. A twenty-eight-weeker at twelve months chronological age is approximately nine months corrected. The distinction changes everything about expectations.
Adopted infants with institutional histories present differently. Their growth curves, attachment patterns, and even immune responses deviate from standard infant norms. Pediatricians trained in typical development sometimes misread these deviations as pathology. The reverse also occurs. Genuine concerns get dismissed because the child's history doesn't match the expected infant trajectory.
Trafficking cases present another edge case. Children recovered from trafficking situations often show severe developmental delays but may appear physically healthy. The infant classification assumes continuous care. That assumption fails catastrophically when care is interrupted or absent. Screening for developmental trauma should be routine in any infant evaluation where the history doesn't align with the presentation.
A Tool That Helps
The WHO Child Growth Standards provide centile charts for weight, length, and head circumference from birth to five years. Download these from the WHO website. Print them. Keep them in the pediatrician's office and at home. Plot every measurement. The visual trajectory matters more than any single data point. A baby dropping from the fifty-first percentile to the third percentile over three months needs investigation. A baby tracking steadily at the third percentile needs reassurance. Both presentations look normal to untrained eyes. The difference determines whether you order a workup or write a note and move on.
I use these charts for every infant encounter. They've saved me from both overreaction and underreaction. The tool is free. The training isn't. Familiarity with the charts takes about six months of daily use. After that, you can spot abnormalities in seconds without plotting anything. Before that, plot everything.
Gallery What Is An Infant
What is Infant Care: In-depth Guide (2022-25) - Child Necessity
What Is Developmental Growth at Tracy Silvera blog
Infancy Stage: Infant Age Range, Milestones & Early Development Guide
Baby Development Stages | Baby development stages chart, Infant development stages guide, Stages ...
The newborn, infant and toddler stages explained