
The Practical Side of Changing Behavior
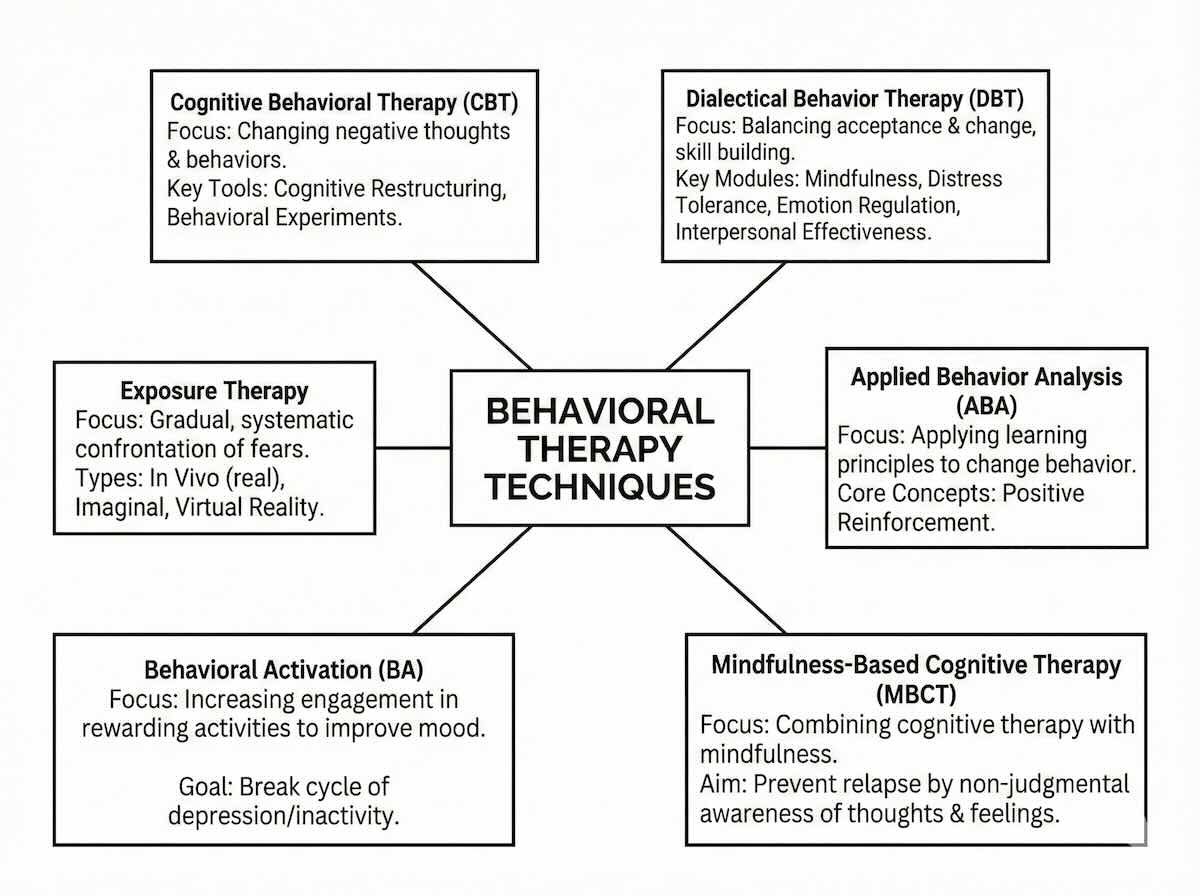
Behavioral therapy is one of those things that sounds straightforward until you're actually in a session and the patient isn't doing what the textbook says they should do. The techniques themselves are well mapped out, but the real work is in knowing which lever to pull and when it's not working, which happens more often than you'd think. At the core, behavioral therapy rests on the premise that behaviors are learned and can be unlearned or reshaped through systematic intervention. The techniques span a range from classical conditioning-based approaches to operant methods to cognitive-behavioral hybrids. Here's how they actually play out in practice. Exposure therapy is probably the most widely used technique for anxiety disorders and PTSD. You systematically expose the patient to the feared stimulus in a controlled way. The key detail most beginners miss is that the exposure has to be prolonged enough for habituation to occur. Sitting through a five-minute exposure and then leaving because the patient is distressed doesn't reduce the fear response. It reinforces avoidance. I had a patient with a specific phobia of heights who would literally panic before we even got in the elevator to the rooftop. We ended up using a graduated VR exposure protocol instead of the planned real-world approach. Started at a 3D simulation of standing on a balcony, worked up through progressively taller virtual environments over eight sessions before attempting the actual rooftop. She was back on that roof three weeks later. The lesson was that rigid adherence to a treatment manual doesn't matter if the patient can't tolerate the first step.
Systematic desensitization works differently. Instead of flooding the patient with the fear stimulus, you pair progressive relaxation with a hierarchy of feared situations. The patient learns to replace the anxiety response with a relaxation response. This is slower but tends to have fewer dropout issues than pure exposure. Joseph Wolfram developed this in the 1950s and it's still one of the most reliable techniques for specific phobias. The limitation is that it takes more sessions. Where exposure might resolve a phobia in six to ten sessions, systematic desensitization often needs twelve to twenty. You trade speed for compliance. Operant conditioning techniques cover a broad range. Reinforcement schedules, token economies, contingency management. These are the go-to tools for behavioral modification in clinical and institutional settings. If you're working with ADHD, autism spectrum disorders, or substance use, you'll rely heavily on these. Positive reinforcement strengthens a desired behavior. Negative reinforcement removes an aversive stimulus to strengthen a behavior. Punishment weakens a behavior but has well-documented side effects including aggression, avoidance, and emotional distress. Most therapists I know avoid punishment-based approaches unless there's an immediate safety concern. Here's something people don't talk about enough: the difference between positive and negative reinforcement is constantly confused even among practitioners who've been doing this for years. Positive reinforcement adds something desirable. Negative reinforcement removes something aversive. Both increase behavior. They're not opposites. The opposite of reinforcement is punishment. I've seen treatment plans that accidentally deployed punishment thinking it was negative reinforcement. The patient's behavior didn't change, but the therapeutic relationship deteriorated significantly.
Behavioral activation is the primary technique used for depression. It's deceptively simple. You schedule pleasurable or mastery activities and gradually increase engagement. The mechanism is breaking the cycle of withdrawal and inactivity that maintains depressive symptoms. The counter-intuitive part is that you don't wait for motivation to appear. You schedule the behavior first and the motivation follows. Most patients expect to feel better before they start acting better. That order is backwards. I had a patient who kept saying she couldn't do the behavioral activation exercises because she had no energy. We spent three sessions just walking around the block. Ten minutes, twice a day. Nothing more demanding than that. After four weeks she was doing thirty-minute walks and had started re-engaging with a hobby she'd abandoned two years prior. The energy didn't come first. The movement did. Modial modeling and behavioral rehearsal involve demonstrating a behavior and then having the patient practice it. Role-playing is the most common form. Used extensively for social anxiety, assertiveness training, and skill deficits. The technique works because it creates a low-stakes environment where mistakes are expected and correction is immediate. The bottleneck is generalization. A patient can perform perfectly in session and still freeze in real social situations. That's why homework is non-negotiable. Without real-world practice, the skill doesn't transfer. I once had a patient who nailed every role-play in therapy but couldn't make a phone call to schedule an appointment afterward. We spent two more weeks doing phone anxiety exercises where she had to make increasingly difficult calls. Voicemail greetings, reservation requests, complaint calls. The role-play was necessary but insufficient on its own. Aversion therapy pairs an undesirable behavior with an unpleasant stimulus. Historically used for addiction and compulsive behaviors. The evidence base is mixed and the ethical concerns are significant. It's fallen out of favor in most clinical settings but still appears in some institutional contexts. The main issue is that it treats the symptom rather than the underlying function of the behavior. An addict who stops drinking because the taste now triggers nausea hasn't developed coping skills for cravings. The behavior changes but the vulnerability remains.
Get the Full Details
Functional behavior assessment isn't a technique itself but it's the foundation that determines which techniques to use. You identify the antecedents, the behavior, and the consequences. What triggers it? What maintains it? Without this analysis you're guessing. I've seen therapists apply exposure protocols to what turned out to be attention-maintained behavior. The exposure made things worse because the patient was actually seeking the confrontation. FBA prevents that mismatch. The biggest mistake I see is treating behavioral therapy as a menu where you pick techniques based on diagnosis alone. It doesn't work that way. The same diagnosis can have completely different behavioral functions in different people. Two patients with obsessive-compulsive disorder might need entirely different exposure hierarchies because their contamination fears and checking compulsions serve different reinforcement functions. One might be avoiding distress. The other might be seeking certainty. The technique is the same. The implementation is different. Behavioral therapy also has real limitations. It's less effective for conditions where rumination and cognitive distortions are primary drivers rather than behavioral avoidance. Severe personality disorders often require longer-term approaches that go beyond standard behavioral protocols. And the therapist-patient relationship matters more than behavioral technique alone. You can have the perfect exposure hierarchy and still fail if the patient doesn't trust you enough to attempt the exercises.



.jpg "Cognitive Behavioral Therapy (CBT) for Mental Health - Techniques, Strategies & Benefits")
