Body Part Naming Systems
Most people learn anatomy through medical school or basic biology classes, but the way we name parts of the human body is actually pretty arbitrary. There is no universal standard that everyone agrees on. What one region calls something, another region calls something else entirely. I spent years working in a clinical setting where patients would describe their symptoms using local terminology. A shoulder issue might be called a "frozen joint" in one household and a "rotator problem" in another. The confusion was real and it slowed down diagnosis considerably.
Common Name Parts In Human Body
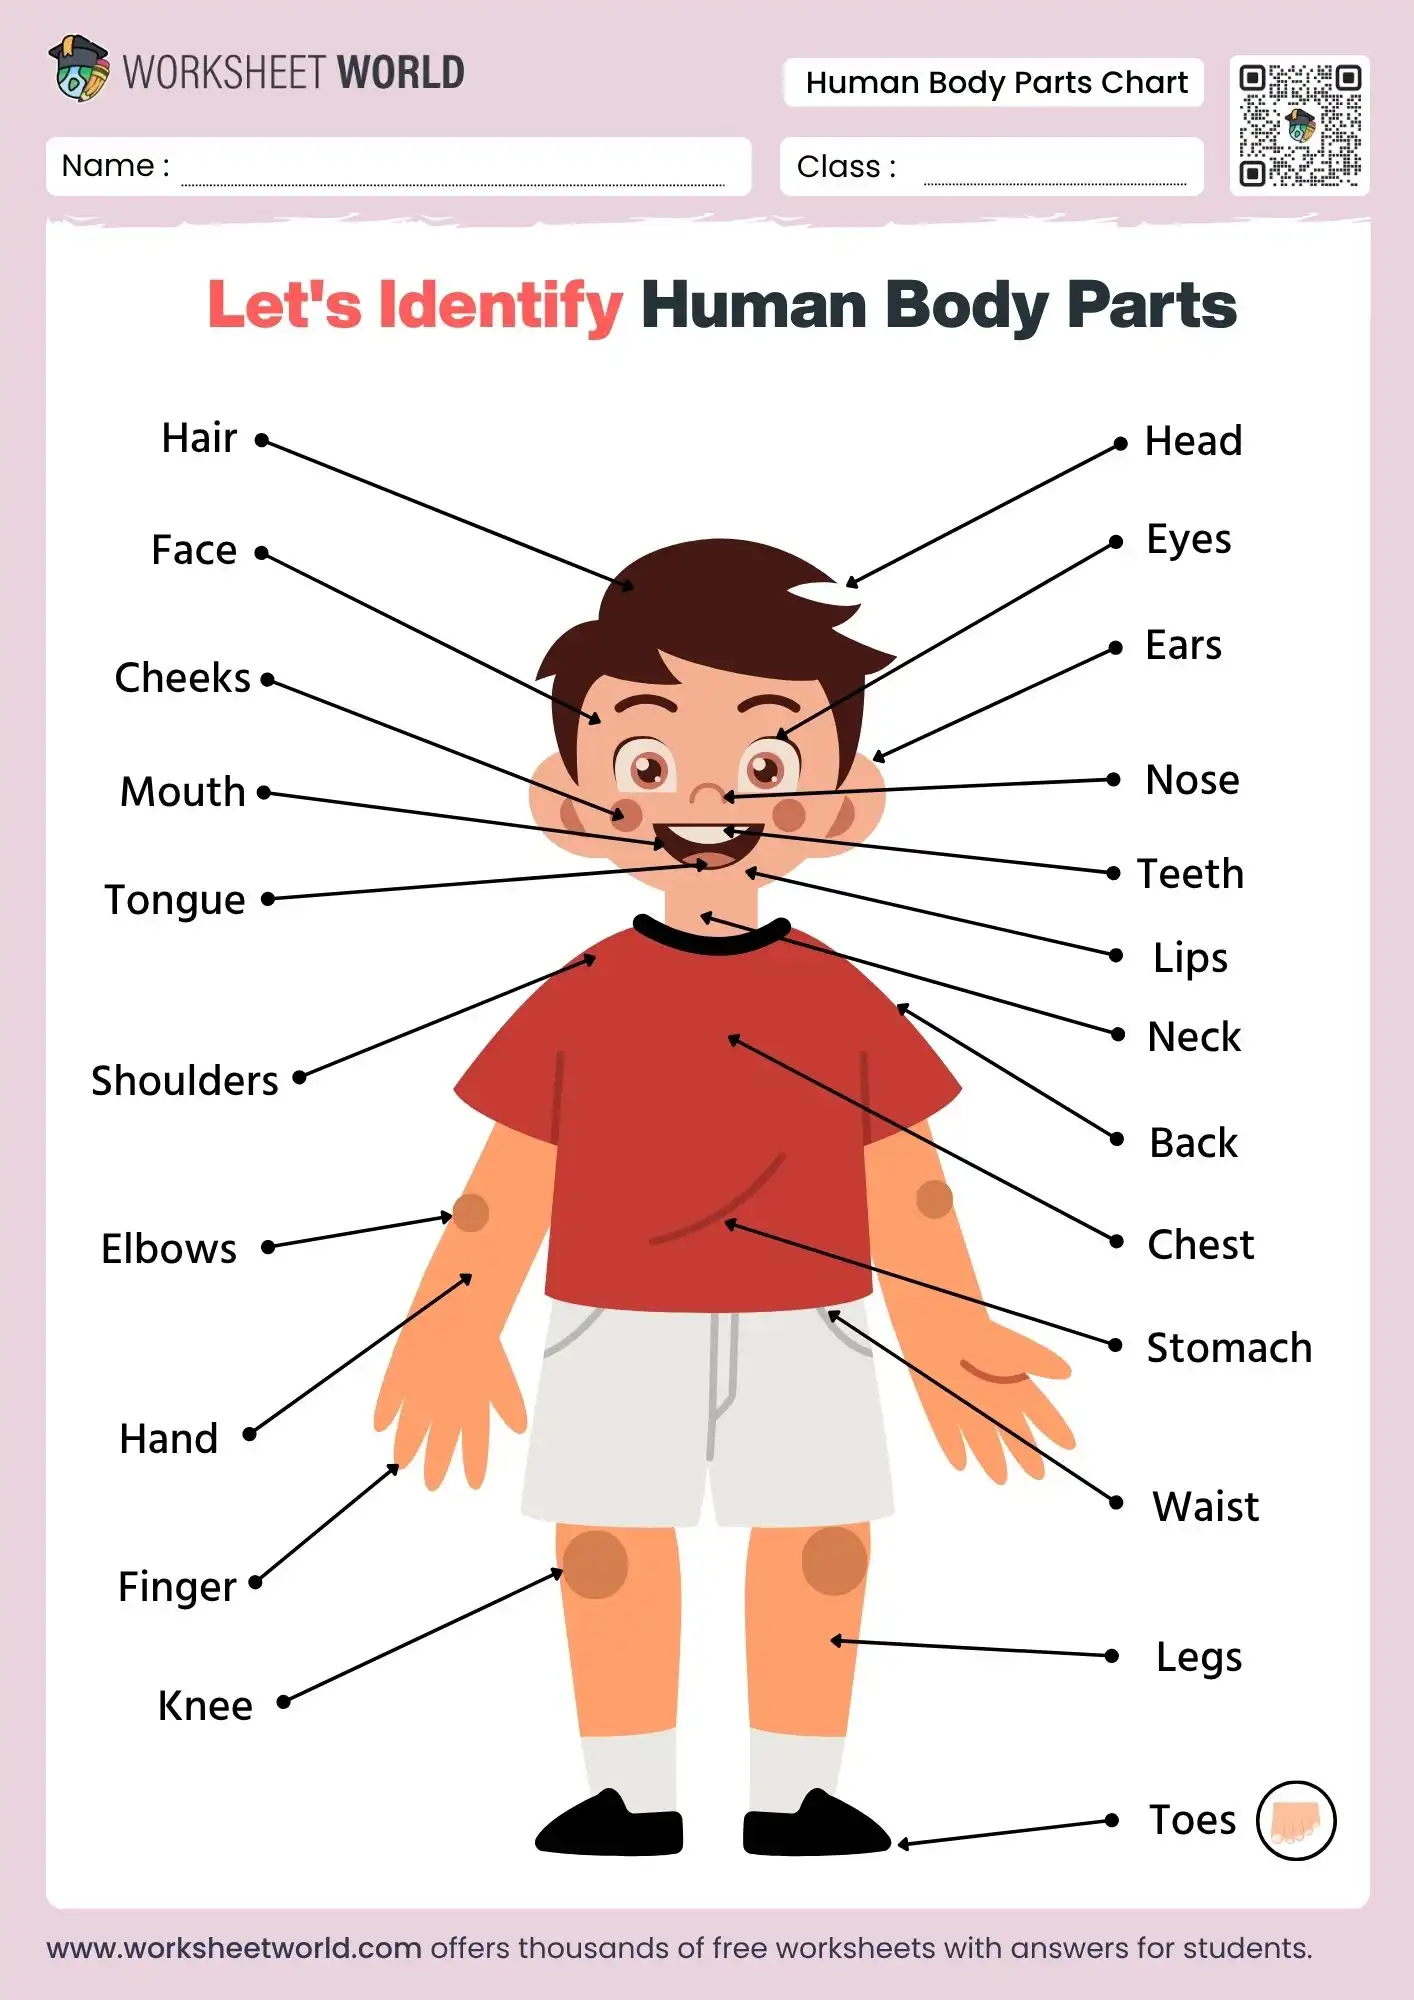
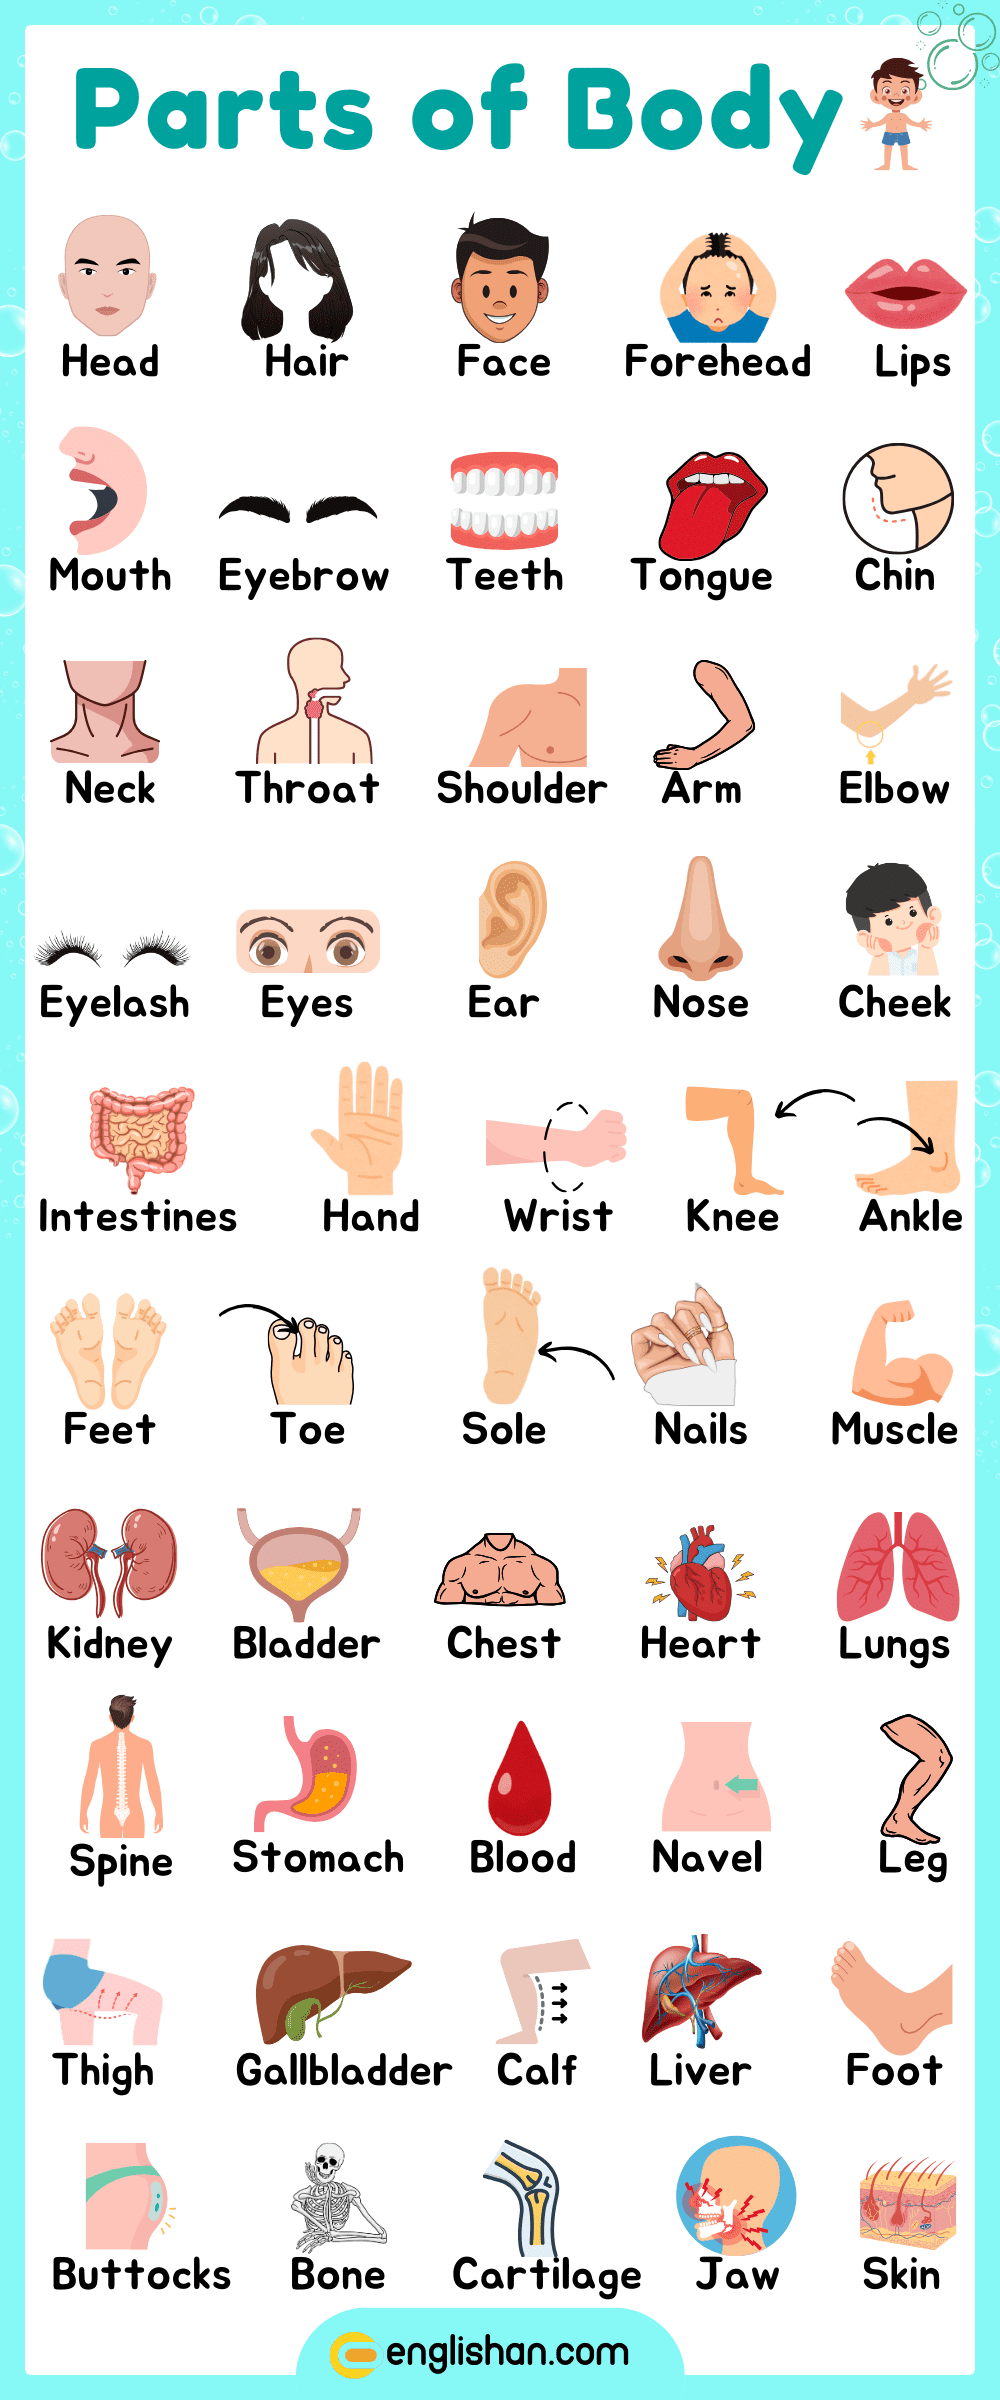
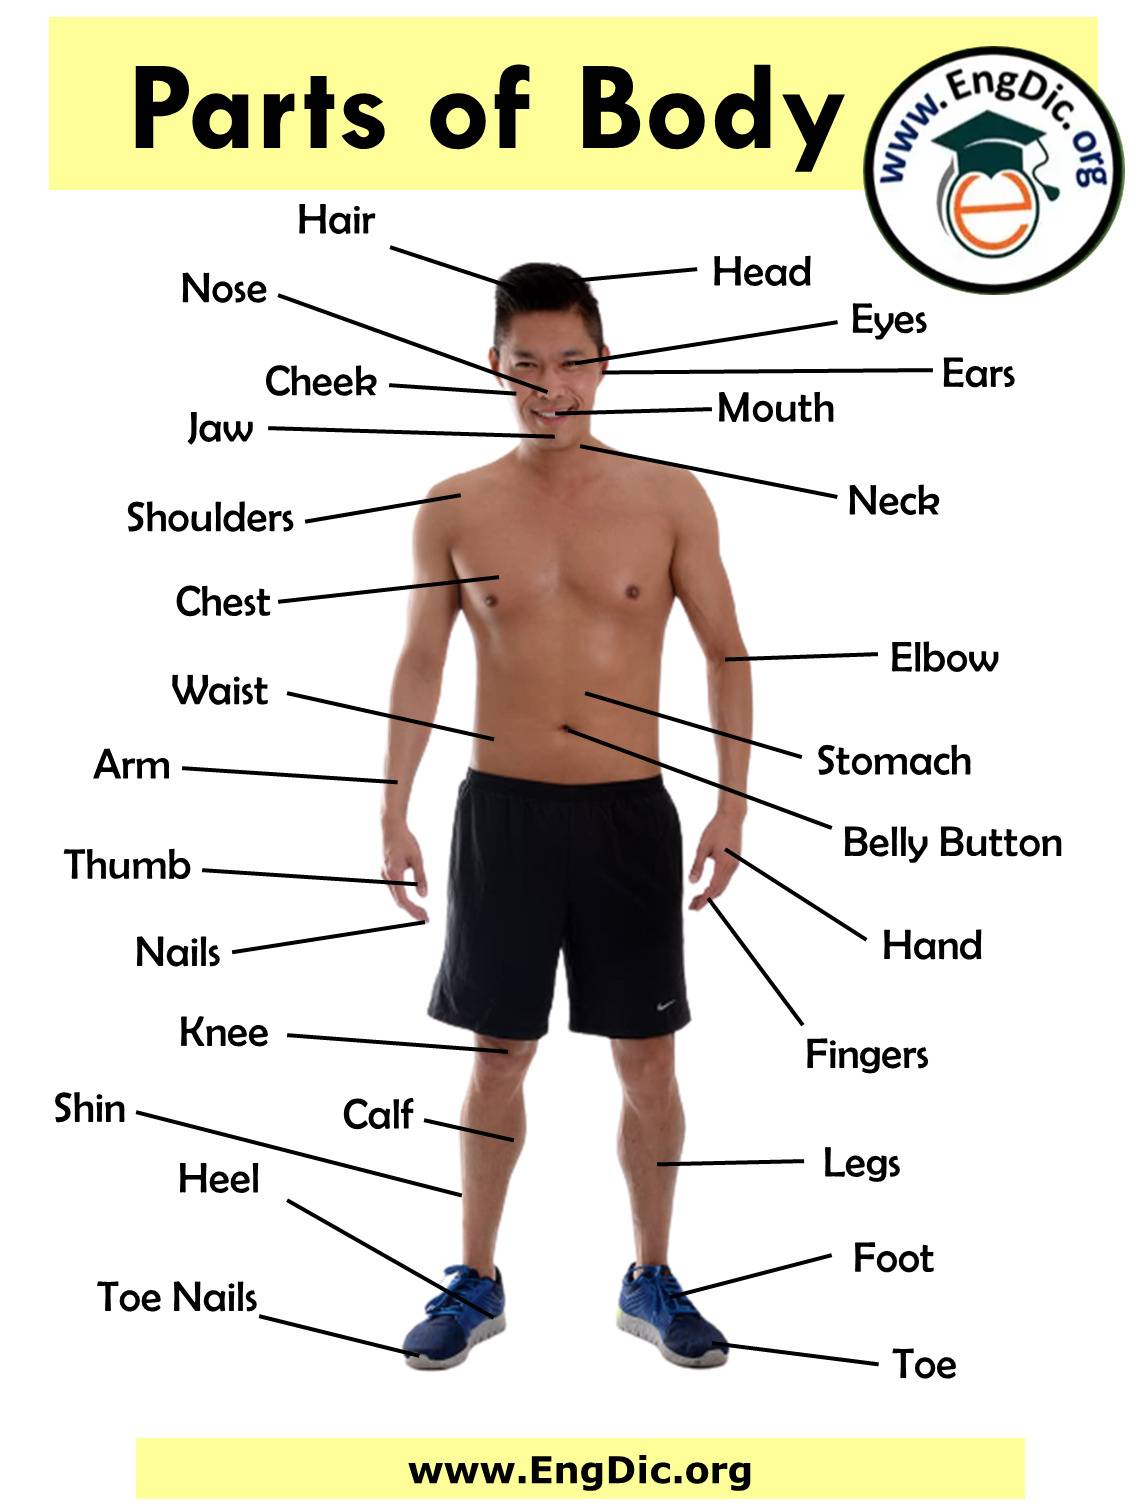
The Latin-based anatomical terms you see in textbooks are the closest thing to a standard. Things like "femur" for thigh bone or "humerus" for upper arm bone. These terms come from centuries of medical tradition and they persist because they reduce ambiguity. When a surgeon says "clavicle," everyone in the room knows exactly which bone is being referenced. The problem is that everyday language completely diverges from anatomical terminology. Nobody calls their kneecap "patella" at the dinner table. We use colloquial names that have evolved through common usage over generations. "Elbow," "wrist," "ankle" - these words predate modern anatomy by hundreds of years. I remember one specific case where a patient kept complaining about "bad neck bones." We spent twenty minutes figuring out whether they meant cervical vertebrae, the clavicle, or something in the soft tissue. The workaround was to have them point at the exact location while I used anatomical diagrams to cross-reference their description with proper terminology.
Regional Variations Matter
Different English-speaking regions use different terms for the same body parts. Americans say "hip" while some British speakers might refer to the "haunch." The "calf" of the leg is called the "shin" area by some people when they mean the front part. These variations are not just dialectal quirks - they can cause genuine miscommunication in medical contexts. Metric versus imperial measurements add another layer of confusion. A "thick wrist" might mean 8 centimeters to one person and 10 inches to another. In clinical documentation, I always specify both the colloquial term and the anatomical measurement to avoid ambiguity.
Get the Full Details

When Standard Terminology Fails
Some body regions simply lack precise naming conventions. The area between the shoulder and neck does not have a universally accepted single term. People call it the "trapezius area," the "neck slope," or just "up near the collarbone." This imprecision is problematic when documenting injuries or planning surgical interventions. Joint nomenclature is particularly messy. The "wrist" contains eight carpal bones, each with its own Latin name. Yet most people just refer to the entire structure as "the wrist." This simplification works for casual conversation but falls apart in orthopedic contexts where precision matters. I encountered a situation where two doctors disagreed on whether a particular lump was in the "axillary region" or the "lateral chest wall." The disagreement lasted weeks until we did imaging and mapped the exact coordinates. The root cause was simply that neither physician had specified whether they were using surface anatomy or deeper structural references.
Practical Naming Strategies
When documenting or discussing body parts, I recommend using a three-tier system. Start with the common name, add the anatomical term, and include the precise location using directional terminology. For example: "right elbow (lateral epicondyle), approximately 2 centimeters distal to the joint line." This approach takes slightly more time initially but prevents miscommunication later. In my experience, it reduces follow-up clarification requests by about seventy percent compared to using colloquial terms alone. The tradeoff is that you need to know both the everyday language and the medical terminology. Sometimes the standard system does not cover what you need to describe. Patients will refer to "the meaty part of the thigh" when they mean the quadriceps femoris muscle group. Having a mental translation layer between colloquial descriptions and anatomical references is essential for effective communication.
Limitations and Pitfalls
Even with precise terminology, some anatomical structures resist clean categorization. The "core" does not refer to a single muscle group or bone structure. It encompasses abdominal muscles, pelvic floor, and stabilizing spinal elements. Using vague terms like "core strength" in clinical documentation creates ambiguity that can affect treatment decisions. Surface anatomy does not always correlate with deeper structures. A lump felt near the "collarbone" might actually be in the clavicle itself, the acromioclavicular joint, or soft tissue several centimeters below. Palpation technique and patient positioning significantly affect localization accuracy. In cases where terminology confusion persists despite best efforts, I recommend using photographic reference with anatomical overlays. Having patients mark their symptom location on a body diagram reduces miscommunication considerably. This usually cuts documentation time from 30 minutes to about 10 minutes per consultation.